Govt Manipulating Data: Hospitals are Instructed to Count All Persons as Unvaxed if there is No Immediate Confirmation of Vax Status, thereby Inflating the No of Unvaxed Hospitalizations and Deaths

From [HIRSHORN] There has been recent attention to CDC hiding considerable data on COVID health impacts.  What has not been focused on, however, is an even greater fraud.  In its goal of coercing the whole population to get COVID shots, CDC has manipulated data to make it look like it is the unvaccinated who have suffered the worst impacts, like hospitalization and death.  They wanted the public to believe there has been a pandemic of the unvaccinated.

For months there have been frightening statements along the lines that unvaccinated Americans are XXX times more likely to be hospitalized or die.  All such statements, including one made by President Biden, are lies, intentionally created by over-counting the number of unvaccinated people.

On February 5 President Biden said: “Here’s the deal: Unvaccinated individuals are 97 times more likely to die compared to those who are boosted.  Protect yourself and those around you by getting vaccinated and boosted today.”

This is what the data fraud is all about.

How has CDC and the public health system created this fiction?

Simply put, it comes down to hospitals categorizing many people as unvaccinated when, in fact, they likely had received the jab.

The fraud by hospitals and CDC is really so simple.  When a COVID patient enters the hospital system there is an immediate check within that system to see if the person had gotten the jab.  Just one very big problem.

A large number of people who enter any hospital very likely got the jab at any one of countless places giving free vaccinations.  That group includes chain pharmacies and ones in supermarkets, community places run by various public health agencies, and physician offices.

What happens when a COVID patient enters a hospital and there is no immediate confirmation that the person got the jab?  That person is classified as UNVACCINATED.

This procedure guarantees an inflated number of unvaccinated COVID hospitalizations and deaths!

The goal is to instill fear among the population that COVID shots are critically needed for public health and safety.

So, data are created for the nation by CDC that there is a pandemic of the unvaccinated.  In truth, the continuing explosion of COVID infections, hospitalizations and deaths in recent months has been a pandemic of the vaccinated.  So many people who have been fully vaccinated, including many who got booster jabs, got infected, got hospitalized, and all too often died.

Another aspect of this fraud is that many vaccine related adverse events are not getting into the CDC VAERS data system because people who are not officially recognized as vaccinated but are suffering a multitude of health problems or death are not counted by CDC.  They are being counted as unvaccinated and, therefore, their conditions do not always fit into the CDC data system counting impacts of vaccines.

Another aspect of this fraud is the use of incorrect population data.

CDC easily uses outdated population numbers that leads to artificially inflated estimates of COVID-19 case, hospitalization and death rates among the ever-shrinking unvaccinated population.  They use population numbers that are lower than the most recent numbers from census studies.  Simply put, they use a denominator that is too low to make their calculation of pandemic impacts seem higher than they really are.

All of this fraud not only casts blame on the unvaccinated, it also is designed to make use of COVID vaccines more effective than they really are.  A pandemic of the vaccinated does not motivate people to get the jab or booster shots.

Withholding data, as recently reported, is terrible.  But how CDC has manipulated data is even worse; it is a big lie compared to a lie of omission.

As the COVID Tyrant Paradigm Unravels [assent to false memes such as ‘covid case,' ‘covid death,’ ‘positive test’ or ‘vax Stops the Spread’] CrimethInc Redirects Sheeples’ Minds to a War Paradigm

According to FUNKTIONARY:

tyrant-paradigm - the assertion or assent to certain concepts, idea, memes, words, patterns of thinking, attitudes, beliefs, and convictions that give rise to coercive political systems. It includes the notion that the tyrants (territorial gangsters) are so omniscient and omnipotent that they can prevent natural persons from living free. The words that constitute the tyrant paradigm are enemy outposts in your mind. Tyrants "own" the minds of their oppressed victims to the extent that victims hold contents of the tyrant-paradigm in the minds. The tyrant-paradigm consists of the "construction of systematic thought" and "the systematic pattems of thought" that give rise to coercive political systems. (See: The OCTOCON, Territorial Gangsters & Reactions)

Tyrants - there are none; only tyranny exists. How can one man or woman rule a multitude against their will except through mind-control and word-conditioning control? "Find out the exact amount of injustice any people accept, and you will find out the exact amount of injustice they receive." -Freddy D. "The evils of tyranny are rarely seen but by him who resists it." -John Jay, Castilian Days II, 1872. (See: Tyranny, Terms, "The Law," Dictatorship, Corporate State & Fascism)

From [HERE] “Of all the enemies to public liberty war is, perhaps, the most to be dreaded because it comprises and develops the germ of every other. War is the parent of armies; from these proceed debts and taxes… known instruments for bringing the many under the domination of the few.… No nation could preserve its freedom in the midst of continual warfare.” — James Madison

War is the enemy of freedom.

As long as America’s politicians continue to involve us in wars that bankrupt the nation, jeopardize our servicemen and women, increase the chances of terrorism and blowback domestically, and push the nation that much closer to eventual collapse, “we the people” will find ourselves in a perpetual state of tyranny.

It’s time for the U.S. government to stop policing the globe.

This latest crisis—America’s part in the showdown between Russia and the Ukraine—has conveniently followed on the heels of a long line of other crises, manufactured or otherwise, which have occurred like clockwork in order to keep Americans distracted, deluded, amused, and insulated from the government’s steady encroachments on our freedoms.

And so it continues in its Orwellian fashion.

Two years after COVID-19 shifted the world into a state of global authoritarianism, just as the people’s tolerance for heavy-handed mandates seems to have finally worn thin, we are being prepped for the next distraction and the next drain on our economy.

Yet policing the globe and waging endless wars abroad isn’t making America—or the rest of the world—any safer, it’s certainly not making America great again, and it’s undeniably digging the U.S. deeper into debt.

Indeed, even if we were to put an end to all of the government’s military meddling and bring all of the troops home today, it would take decades to pay down the price of these wars and get the government’s creditors off our backs.

War has become a huge money-making venture, and the U.S. government, with its vast military empire, is one of its best buyers and sellers.

What most Americans—brainwashed into believing that patriotism means supporting the war machine—fail to recognize is that these ongoing wars have little to do with keeping the country safe and everything to do with propping up a military industrial complex that continues to dominate, dictate and shape almost every aspect of our lives.

Consider: We are a military culture engaged in continuous warfare. We have been a nation at war for most of our existence. We are a nation that makes a living from killing through defense contracts, weapons manufacturing and endless wars.

We are also being fed a steady diet of violence through our entertainment, news and politics.

All of the military equipment featured in blockbuster movies is provided—at taxpayer expense—in exchange for carefully placed promotional spots.

Back when I was a boy growing up in the 1950s, almost every classic sci fi movie ended with the heroic American military saving the day, whether it was battle tanks in Invaders from Mars (1953) or military roadblocks in Invasion of the Body Snatchers (1956).

What I didn’t know then as a schoolboy was the extent to which the Pentagon was paying to be cast as America’s savior. By the time my own kids were growing up, it was Jerry Bruckheimer’s blockbuster film Top Gun—created with Pentagon assistance and equipment—that boosted civic pride in the military.

Now it’s my grandkids’ turn to be awed and overwhelmed by child-focused military propaganda. Don’t even get me started on the war propaganda churned out by the toymakers. Even reality TV shows have gotten in on the gig, with the Pentagon’s entertainment office helping to sell war to the American public.

It’s estimated that U.S. military intelligence agencies (including the NSA) have influenced over 1,800 movies and TV shows.

And then there are the growing number of video games, a number of which are engineered by or created for the military, which have accustomed players to interactive war play through military simulations and first-person shooter scenarios.

This is how you acclimate a population to war.

This is how you cultivate loyalty to a war machine.

This is how, to borrow from the subtitle to the 1964 film Dr. Strangelove, you teach a nation to “stop worrying and love the bomb.”

As journalist David Sirota writes for Salon, “[C]ollusion between the military and Hollywood – including allowing Pentagon officials to line edit scripts—is once again on the rise, with new television programs and movies slated to celebrate the Navy SEALs….major Hollywood directors remain more than happy to ideologically slant their films in precisely the pro-war, pro-militarist direction that the Pentagon demands in exchange for taxpayer-subsidized access to military hardware.”

Why is the Pentagon (and the CIA and the government at large) so focused on using Hollywood as a propaganda machine?

To those who profit from war, it is—as Sirota recognizes—“a ‘product’ to be sold via pop culture products that sanitize war and, in the process, boost recruitment numbers….At a time when more and more Americans are questioning the fundamental tenets of militarism (i.e., budget-busting defense expenditures, never-ending wars/occupations, etc.), military officials are desperate to turn the public opinion tide back in a pro-militarist direction — and they know pop culture is the most effective tool to achieve that goal.”

The media, eager to score higher ratings, has been equally complicit in making (real) war more palatable to the public by packaging it as TV friendly.

This is what professor Roger Stahl refers to as the representation of a “clean war”: a war “without victims, without bodies, and without suffering”:

“‘Dehumanize destruction’ by extracting all human imagery from target areas … The language used to describe the clean war is as antiseptic as the pictures. Bombings are ‘air strikes.’ A future bombsite is a ‘target of opportunity.’ Unarmed areas are ‘soft targets.’ Civilians are ‘collateral damage.’ Destruction is always ‘surgical.’ By and large, the clean war wiped the humanity of civilians from the screen … Create conditions by which war appears short, abstract, sanitized and even aesthetically beautiful. Minimize any sense of death: of soldiers or civilians.”

This is how you sell war to a populace that may have grown weary of endless wars: sanitize the war coverage of anything graphic or discomfiting (present a clean war), gloss over the actual numbers of soldiers and civilians killed (human cost), cast the business of killing humans in a more abstract, palatable fashion (such as a hunt), demonize one’s opponents, and make the weapons of war a source of wonder and delight.

“This obsession with weapons of war has a name: technofetishism,” explains Stahl. “Weapons appear to take on a magical aura. They become centerpieces in a cult of worship.”

“Apart from gazing at the majesty of these bombs, we were also invited to step inside these high-tech machines and take them for a spin,” said Stahl. “Or if we have the means, we can purchase one of the military vehicles on the consumer market. Not only are we invited to fantasize about being in the driver’s seat, we are routinely invited to peer through the crosshairs too. These repeated modes of imaging war cultivate new modes of perception, new relationships to the tools of state violence. In other words, we become accustomed to ‘seeing’ through the machines of war.”

In order to sell war, you have to feed the public’s appetite for entertainment.

Not satisfied with peddling its war propaganda through Hollywood, reality TV shows and embedded journalists whose reports came across as glorified promotional ads for the military, the Pentagon has also turned to sports to further advance its agenda, “tying the symbols of sports with the symbols of war.”

The military has been firmly entrenched in the nation’s sports spectacles ever since, having co-opted football, basketball, even NASCAR.

This is how you sustain the nation’s appetite for war.

No wonder entertainment violence is the hottest selling ticket at the box office. As professor Henry Giroux points out, “Popular culture not only trades in violence as entertainment, but also it delivers violence to a society addicted to a pleasure principle steeped in graphic and extreme images of human suffering, mayhem and torture.”

No wonder the government continues to whet the nation’s appetite for violence and war through paid propaganda programs (seeded throughout sports entertainment, Hollywood blockbusters and video games)—what Stahl refers to as “militainment“—that glorify the military and serve as recruiting tools for America’s expanding military empire.

No wonder Americans from a very young age are being groomed to enlist as foot soldiers—even virtual ones—in America’s Army (coincidentally, that’s also the name of a first person shooter video game produced by the military). Explorer Scouts, for example, are one of the most popular recruiting tools for the military and its civilian counterparts (law enforcement, Border Patrol, and the FBI).

No wonder the United States is the number one consumer, exporter and perpetrator of violence and violent weapons in the world. Seriously, America spends more money on war than the combined military budgets of China, Russia, the United Kingdom, Japan, France, Saudi Arabia, India, Germany, Italy and Brazil. America polices the globe, with 800 military bases and troops stationed in 160 countries. Moreover, the war hawks have turned the American homeland into a quasi-battlefield with military gear, weapons and tactics. In turn, domestic police forces have become roving extensions of the military—a standing army.

We are dealing with a sophisticated, far-reaching war machine that has woven itself into the very fabric of this nation.

Clearly, our national priorities are in desperate need of an overhaul.

Eventually, all military empires fall and fail by spreading themselves too thin and spending themselves to death.

It happened in Rome: at the height of its power, even the mighty Roman Empire could not stare down a collapsing economy and a burgeoning military. Prolonged periods of war and false economic prosperity largely led to its demise.

It’s happening again.

The American Empire—with its endless wars waged by U.S. military servicepeople who have been reduced to little more than guns for hire: outsourced, stretched too thin, and deployed to far-flung places to police the globe—is approaching a breaking point.

The government is destabilizing the economy, destroying the national infrastructure through neglect and a lack of resources, and turning taxpayer dollars into blood money with its endless wars, drone strikes and mounting death tolls.

This is exactly the scenario President Dwight D. Eisenhower warned against when he cautioned the citizenry not to let the profit-driven war machine endanger our liberties or democratic processes. Eisenhower, who served as Supreme Commander of the Allied forces in Europe during World War II, was alarmed by the rise of the profit-driven war machine that, in order to perpetuate itself, would have to keep waging war.

Yet as Eisenhower recognized, the consequences of allowing the military-industrial complex to wage war, exhaust our resources and dictate our national priorities are beyond grave:

Every gun that is made, every warship launched, every rocket fired signifies, in the final sense, a theft from those who hunger and are not fed, those who are cold and are not clothed. This world in arms is not spending money alone. It is spending the sweat of its laborers, the genius of its scientists, the hopes of its children. The cost of one modern heavy bomber is this: a modern brick school in more than 30 cities. It is two electric power plants, each serving a town of 60,000 population. It is two fine, fully equipped hospitals. It is some 50 miles of concrete highway. We pay for a single fighter with a half million bushels of wheat. We pay for a single destroyer with new homes that could have housed more than 8,000 people. This, I repeat, is the best way of life to be found on the road the world has been taking. This is not a way of life at all, in any true sense. Under the cloud of threatening war, it is humanity hanging from a cross of iron.

We failed to heed Eisenhower’s warning.

The illicit merger of the armaments industry and the government that Eisenhower warned against has come to represent perhaps the greatest threat to the nation today.

What we have is a confluence of factors and influences that go beyond mere comparisons to Rome. It is a union of Orwell’s 1984 with its shadowy, totalitarian government—i.e., fascism, the union of government and corporate powers—and a total surveillance state with a military empire extended throughout the world.

As I make clear in my book Battlefield America: The War on the American People and in its fictional counterpart The Erik Blair Diaries, this is how tyranny rises and freedom falls.

The growth of and reliance on militarism as the solution for our problems both domestically and abroad bodes ill for the constitutional principles which form the basis of the American experiment in freedom.

As author Aldous Huxley warned: “Liberty cannot flourish in a country that is permanently on a war footing, or even a near-war footing. Permanent crisis justifies permanent control of everybody and everything by the agencies of the central government.”


Dr David Martin: There was No COVID Emergency. Fauci/Others Weaponized a Man-Made Virus and Hyped the Public into a Science-Free Hysteria, in a Conspiracy to Create Human Dependency on Deadly Vaccines

The following is an excerpt from the Fauci/COVID-19 Dossier by Dr. David Martin

While not covered under 35 U.S.C. §101, Dr. Fauci’s abuse of the patent law is detailed below. Of note, however, is his willful and deceptive use of the term “vaccine” in patents and public pronouncements to pervert the meaning of the term for the manipulation of the public.

In the 1905 Jacobson v. Mass case, the court was clear that a PUBLIC BENEFIT was required for a vaccine to be mandated. Neither Pfizer nor Moderna have proved a disruption of transmission. In Jacobson v. Massachusetts, 197 U.S. 11 (1905), the court held that the context for their opinion rested on the following principle:

“This court has more than once recognized it as a fundamental principle that ‘persons and property are subjected to all kinds of restraints and burdens in order to secure the general comfort, health, and prosperity of the state…”

The Moderna and Pfizer “alleged vaccine” trials have explicitly acknowledged that their gene therapy technology has no impact on viral infection or transmission whatsoever and merely conveys to the recipient the capacity to produce an S1 spike protein endogenously by the introduction of a synthetic mRNA sequence. Therefore, the basis for the Massachusetts statute and the Supreme Court’s determination is moot in this case.

Further, the USPTO, in its REJECTION of Anthony Fauci’s HIV vaccine made the following statement supporting their rejection of his bogus “invention”

By no later than April 11, 2005, Dr. Anthony Fauci was publicly acknowledging the association of SARS with bioterror potential. Leveraging the fear of the anthrax bioterrorism of 2001, he publicly celebrated the economic boon that domestic terror had directed towards his budget. He specifically stated that NIAID was actively funding research on a “SARS Chip” DNA microarray to rapidly detect SARS (something that was not made available during the current “pandemic”) and two candidate vaccines focused on the SARS CoV spike protein.7 Led by three Chinese researchers under his employment – Zhi-yong Yang, Wing-pui Kong, and Yue Huang – Fauci had at least one DNA vaccine in animal trials by 2004.8 This team, part of the Vaccine Research Center at NIAID, was primarily focused on HIV vaccine development but was tasked to identify SARS vaccine candidates as well. Working in collaboration with Sanofi, Scripps Institute, Harvard, MIT and NIH, Dr. Fauci’s decision to unilaterally promote vaccines as a primary intervention for several designated “infectious diseases” precluded proven therapies from being applied to the sick and dying.9

The CDC and NIAID led by Anthony Fauci entered into trade among States (including, but not limited to working with EcoHealth Alliance Inc.) and with foreign nations (specifically, the Wuhan Institute of Virology and the Chinese Academy of Sciences) through the 2014 et seq National Institutes of Health Grant R01AI110964 to exploit their patent rights. This research was known to involve surface proteins in coronavirus that had the capacity to directly infect human respiratory systems. In flagrant violation of the NIH moratorium on gain of function research, NIAID and Ralph Baric persisted in working with chimeric coronavirus components specifically to amplify the pathogenicity of the biologic material.

By October 2013, the Wuhan Institute of Virology 1 coronavirus S1 spike protein was described in NIAID’s funded work in China. This work involved NIAID, USAID, and Peter Daszak, the head of EcoHealth Alliance. This work, funded under R01AI079231, was pivotal in isolating and manipulating viral fragments selected from sites across China which contained high risk for severe human response.10

By March 2015, both the virulence of the S1 spike protein and the ACE II receptor was known to present a considerable risk to human health. NIAID, EcoHealth Alliance and numerous researchers lamented the fact that the public was not sufficiently concerned about coronavirus to adequately fund their desired research.11

Dr. Peter Daszak of EcoHealth Alliance offered the following assessment:

“Daszak reiterated that, until an infectious disease crisis is very real, present, and at an emergency threshold, it is often largely ignored. To sustain the funding base beyond the crisis, he said, we need to increase public understanding of the need for MCMs such as a pan-influenza or pan-coronavirus vaccine. A key driver is the media, and the economics follow the hype. We need to use that hype to our advantage to get to the real issues. Investors will respond if they see profit at the end of process, Daszak stated.”12

Economics will follow the hype.

The CDC and NIAID entered into trade among States (including, but not limited to working with University of North Carolina, Chapel Hill) and with foreign nations (specifically, the Wuhan Institute of Virology and the Chinese Academy of Sciences represented by Zheng-Li Shi) through U19AI109761 (Ralph S. Baric), U19AI107810 (Ralph S. Baric), and National Natural Science Foundation of China Award 81290341 (Zheng-Li Shi) et al. 2015-2016. These projects took place during a time when the work being performed was prohibited by the United States National Institutes of Health.

The public was clearly advised of the dangers being presented by NIAID-funded research by 2015 and 2016 when the Wuhan Institute of Virology material was being manipulated at UNC in Ralph Baric’s lab.

“The only impact of this work is the creation, in a lab, of a new, non-natural risk,” agrees Richard Ebright, a molecular biologist and biodefence expert at Rutgers University in Piscataway, New Jersey. Both Ebright and Wain-Hobson are long-standing critics of gain-of-function research.

In their paper, the study authors also concede that funders may think twice about allowing such experiments in the future. "Scientific review panels may deem similar studies building chimeric viruses based on circulating strains too risky to pursue," they write, adding that discussion is needed as to "whether these types of chimeric virus studies warrant further investigation versus the inherent risks involved”.

But Baric and others say the research did have benefits. The study findings “move this virus from a candidate emerging pathogen to a clear and present danger”, says Peter Daszak, who co-authored the 2013 paper. Daszak is president of the EcoHealth Alliance, an international network of scientists, headquartered in New York City, that samples viruses from animals and people in emerging-diseases hotspots across the globe.

Studies testing hybrid viruses in human cell culture and animal models are limited in what they can say about the threat posed by a wild virus, Daszak agrees. But he argues that they can help indicate which pathogens should be prioritized for further research attention.”13

Knowing that the U.S. Department of Health and Human Services (through CDC, NIH, NIAID, and their funded laboratories and commercial partners) had patents on each proposed element of medical counter measures and their funding, Dr. Fauci, Dr. Gao (China CDC), and Dr. Elias (Bill and Melinda Gates Foundation) conspired to commit acts of terror on the global population – including the citizens of the United States – when, in September 2019, they published the following mandate:

“Countries, donors and multilateral institutions must be prepared for the worst. A rapidly spreading pandemic due to a lethal respiratory pathogen (whether naturally emergent or accidentally or deliberately released) poses additional preparedness requirements. Donors and multilateral institutions must ensure adequate investment in developing innovative vaccines and therapeutics, surge manufacturing capacity, broad-spectrum antivirals and appropriate non- pharmaceutical interventions. All countries must develop a system for immediately sharing genome sequences of any new pathogen for public health purposes along with the means to share limited medical countermeasures across countries.

Progress indicator(s) by September 2020

• Donors and countries commit and identify timelines for: financing and development of a universal influenza vaccine, broad spectrum antivirals, and targeted therapeutics. WHO and its Member States develop options for standard procedures and timelines for sharing of sequence data, specimens, and medical countermeasures for pathogens other than influenza.

• Donors, countries and multilateral institutions develop a multi-year plan and approach for strengthening R&D research capacity, in advance of and during an epidemic.

• WHO, the United Nations Children’s Fund, the International Federation of Red Cross and Red Crescent Societies, academic and other partners identify strategies for increasing capacity and integration of social science approaches and researchers across the entire preparedness/response continuum.”14

As if to confirm the utility of the September 2019 demand for “financing and development of” vaccine and the fortuitous SARS CoV-2 alleged outbreak in December of 2019, Dr. Fauci began gloating that his fortunes for additional funding were likely changing for the better. In a February 2020 interview in STAT, he was quoted as follows:

““The emergence of the new virus is going to change that figure, likely considerably, Fauci said. “I don’t know how much it’s going to be. But I think it’s going to generate more sustained interest in coronaviruses because it’s very clear that coronaviruses can do really interesting things.””15

18 U.S.C. § 2331 §§ 802 – Acts of Domestic Terrorism resulting in death of American Citizens

Section 802 of the USA PATRIOT Act (Pub. L. No. 107-52) expanded the definition of terrorism to cover "domestic," as opposed to international, terrorism. A person engages in domestic terrorism if they do an act "dangerous to human life" that is a violation of the criminal laws of a state or the United States, if the act appears to be intended to: (i) intimidate or coerce a civilian population; (ii) influence the policy of a government by intimidation or coercion;

Dr. Anthony Fauci has intimidated and coerced a civilian population and sought to influence the policy of a government by intimidation and coercion.

With no corroboration, Dr. Anthony Fauci promoted16 Professor Neil Ferguson’s computer simulation derived claims that,

“The world is facing the most serious public health crisis in generations. Here we provide concrete estimates of the scale of the threat countries now face.

“We use the latest estimates of severity to show that policy strategies which aim to mitigate the epidemic might halve deaths and reduce peak healthcare demand by two-thirds, but that this will not be enough to prevent health systems being overwhelmed. More intensive, and socially disruptive interventions will therefore be required to suppress transmission to low levels. It is likely such measures – most notably, large scale social distancing – will need to be in place for many months, perhaps until a vaccine becomes available.” 17

Reporting to the President that as many as 2.2 million deaths may result from a pathogen that had not yet been isolated and could not be measured with any accuracy, Dr. Fauci intimidated and coerced the population and the government into reckless, untested, and harmful acts creating irreparable harm to lives and livelihoods.18 Neither the Imperial College nor the “independent” Institute for Health Metrics and Evaluation (principally funded by the Bill and Melinda Gates Foundation)19 had any evidence of success in estimating previous burdens from coronavirus but, without consultation or peer-review, Dr. Fauci adopted their terrifying estimates as the basis for interventions that are explicitly against medical advice.

  •   The imposition of social distancing was based on computer simulation and environmental models with NO disease transmission evidence whatsoever.

  •   The imposition of face mask wearing was directly against controlled clinical trial evidence and against the written policy in the Journal of the American Medical Association.

    “Face masks should not be worn by healthy individuals to protect themselves from acquiring respiratory infection because there is no evidence to suggest that face masks worn by healthy individuals are effective in preventing people from becoming ill.”20

  •   In both the Imperial College and the IHME simulations, quarantines were modeled for the sick, not the healthy.

Insisting on vaccines while blockading the emergency use of proven pharmaceutical interventions may have contributed to the death of many patients and otherwise healthy individuals.21

Using the power of NIAID during the alleged pandemic, Dr. Anthony Fauci actively suppressed proven medical countermeasures used by, and validated in scientific proceedings, that offered alternatives to the products funded by his conspiring entities for which he had provided direct funding and for whom he would receive tangible and intangible benefit. [MORE]

New Study: All Persons Under 50 are at Greater Risk of Death after Getting a COVID Shot than an Unvaccinated Person is at Risk of a COVID Death. COVID Shot Found to Have No Benefit for Anyone Under 80

DOWNLOAD PAPER [PDF]

From {HIRSHORN] Below are excerpts from a new analysis by two great people; the title is “COVID-19 and All-Cause Mortality Data by Age Group Reveals Risk of COVID Vaccine-Induced Fatality is Equal to or Greater than the Risk of a COVID death for all Age Groups Under 80 Years Old as of 6 February 2022.”

From the abstract:

As of 6 February 2022, based on publicly available official UK and US data, all age groups under 50 years old are at greater risk of fatality after receiving a COVID-19 inoculation than an unvaccinated person is at risk of a COVID-19 death. All age groups under 80 years old have virtually no benefit from receiving a COVID-19 inoculation, and the younger ages incur significant risk.

From the conclusions:

The benefits of vaccination against COVID-19 have not lived up to expectations. There has been a rapid drop in vaccine-induced antibody levels over time and the rapid emergence of SARS-CoV-2 variants that are resistant to the vaccinal antibodies to the spike protein. When COVID-19 death data by vaccination status from early 2022 are analyzed to estimate the degree of protection from mortality afforded to the vaccinated population, the protection from COVID-19 death falls far short of the risk of dying from the vaccine, for anyone below 50 years old.

With Omicron now the dominant strain, the vaccinated population are still catching the disease in large numbers and spreading it. The mRNA vaccines were designed to target the original SARS-CoV-2 strain, and the arrival of variants like Delta and Omicron have changed the risk/benefit ratio. With such a large percentage of the population catching omicron and recovering, we now have a much larger base of 11 a naturally resistant population, whose immunity is much longer lasting and robust than that achieved with the vaccine. With Omicron being both less deadly and more resistant to vaccine antibodies, the benefits of vaccination are further weakened, while the risks of dying from the vaccine remain unaltered.

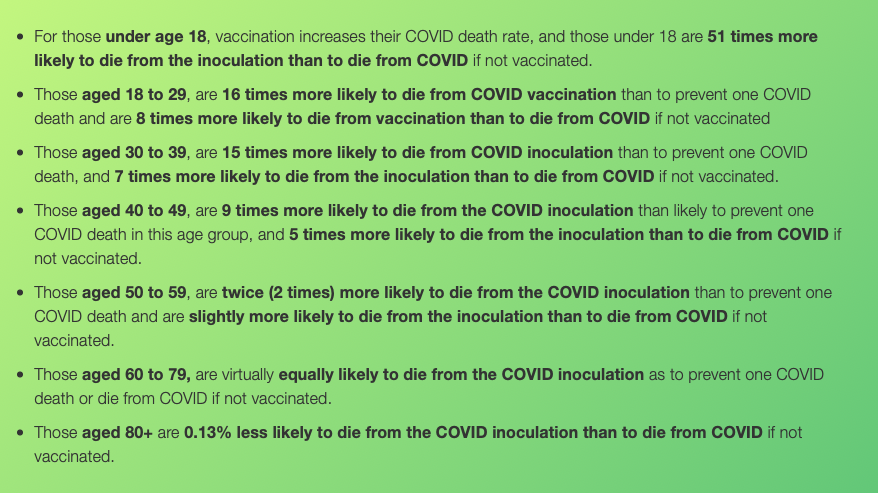
Even if we roll out new versions of the vaccines, the virus will continue to mutate in a futile cat-and-mouse game. According to the data analysis presented in this paper, all age cohorts under 50 years old are at greater risk (from 5 to 51 times higher) of vaccine-induced fatality within the same or subsequent month of receiving a COVID-19 inoculation than they are at risk of a COVID-19 death within 60 days of a positive test if unvaccinated. All age cohorts have less than ¼ of 1% benefit of absolute risk reduction of a COVID-19 death from receiving a COVID-19 inoculation. Children under age 18 years have 51 times higher chance of fatality after a COVID inoculation than risk of dying from COVID if unvaccinated.

Vaccinations in the under 18 age group are more likely to increase the number of COVID deaths in this age group rather than prevent any. Young adults age 18 to 29 have an 8 times higher risk of fatality from the inoculation than from COVID if not inoculated. This analysis is conservative because it ignores the inoculation-induced risk increases of later fatalities and shortened life spans from thrombosis, myocarditis, Bell’s palsy, and other known vaccine-induced injuries and ignores the 90% or more decreases in risk of COVID-19 death if early, effective treatments were provided to all symptomatic high-risk persons. Mandates of COVID inoculations are ill-advised because the alleged vaccines result in higher death rates than COVID itself.

Dr. Josef Thoma Discusses the Inflammation of the Heart Caused by COVID Injections. Even if Myocarditis Heals, there is a Lifelong Risk of Sudden Cardiac Death, Diminished Stamina and Quality of Life

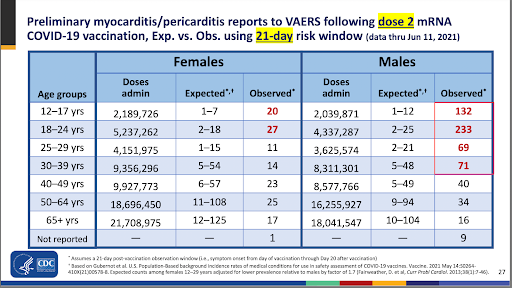
From [HERE] By now, everyone has heard that the COVID vaccines cause myocarditis, particularly in the young; however, the significance is downplayed in the media and even in officious medical publications. In the 11-minute video posted below, Josef Thoma MD/PhD, a general practitioner from Berlin, explains what a diagnosis of myocarditis really means: even if it has apparently healed, the patient is left with a lifelong risk of sudden cardiac death, and often also with diminished stamina and quality of life. Thoma presents some recent observations on autopsy materials from vaccine victims, made by professors of pathology Burkhardt and Lange, which drive home he serious nature of vaccine-induced myocarditis. He ends with an appeal to us to protect our children. Please take a look at this important video and share it.

CDC Refuses to publish data it has collected on booster effectiveness for 33 Million Americans aged 18-49 over fears it might show the Injections as ineffective

From [HERE] Two weeks ago the Centers for Disease Control and Prevention (CDC) published data about the effectiveness of boosters against COVID-19

The CDC failed to publish a tranche of their data, however – omitting the impact on those aged 18-49, who are least likely to benefit from boosters

The CDC are also being criticized for failing to publish their information about child hospitalization rates and comorbidities

A spokeswoman for the CDC said they were concerned that the data would be misinterpreted, pointing out that it was incomplete and not verified

Critics said that it was always better to publish the information rather than withhold, and allow scientists to analyze and explain what they could 

Oklahoma AG declares medical boards cannot punish doctors for prescribing ivermectin

From [NN] Even though federal bureaucrats have arbitrarily decided that Americans should not have access to it, Oklahoma Attorney General John O’Connor says that doctors in his state, at least, are well within their professional rights to prescribe ivermectin to Wuhan coronavirus (Covid-19) patients.

The same goes for hydroxychloroquine (HCQ), another blacklisted drug that the federal overlords have decreed should never go into an American’s body because it might actually help to prevent a serious infection.

“The Attorney General’s office finds no legal basis for a state medical licensure board to discipline a licensed physician for exercising sound judgment and safely prescribing an FDA-approved drug – like ivermectin or hydroxychloroquine – for the off-label purpose of treating a patient with COVID-19,” O’Connor’s office said in a February 8 statement.

“Healthcare professionals should have every tool available to combat COVID-19,” the statement goes on to read. “The Attorney General’s office neither condones nor condemns a specific course of treatment for COVID-19. Our office maintains that proper healthcare decisions are to be made between a patient and his or her physician, and the government should not interfere with their relationship.”

Both ivermectin and HCQ have been approved by the U.S. Food and Drug Administration (FDA) for many decades, by the way. Only recently have they been maligned by the government as “horse dewormer” and “aquarium cleaner,” respectively.

Boston Puppetician Mayor Ends Deadly Indoor COVID Injection Mandate but Has Uncontrollable Authority to Reinstate It Whenever She Wants

From [HERE] Boston Mayor Michelle Wu just lifted the city’s proof-of-COVID-19 vaccine mandate for indoor businesses, effective immediately. The city’s February 18 announcement was based on public health data, citing a recent drop in COVID-19 cases and hospitalization rates and improved hospital capacity.The mandate’s end means Boston businesses are no longer required to verify the vaccination status of people — patrons, employees, contractors, and all other individuals — before they enter indoor spaces.

Early End to Vaccine Mandate

The mandate, which took effect January 15, required proof of COVID-19 vaccination for entry into indoor dining, entertainment, recreation, and fitness establishments (we discussed the phases and requirements of the mandate in this December insight). It was intended to be a long-term strategy, rolled out in phases through May, to combat high rates of COVID-19 cases while preserving indoor gatherings. But fast-moving developments over the past month have altered those plans and relieved businesses of their compliance obligations when it comes to vaccination status.

Notably, the repeal follows news that the Massachusetts Appeals Court temporarily blocked Boston’s vaccine requirement for city employees on February 15. Several unions, including the Boston Police Superior Officers Federation, the Boston Police Detectives Benevolent Society, and the Boston Firefighters Union Local 718, challenged the policy in December as violating the city’s contract obligations and state collective bargaining law. In light of this decision, Boston cannot enforce the municipal employee vaccine mandate until the final resolution of the dispute. Mayor Wu’s administration expressed disappointment in the decision and stated it intends to review it carefully.

Mask Mandate Remains in Place…For Now

Boston’s indoor mask rule remains in place. However, Mayor Wu has indicated the Boston Public Health Commission will review this in the upcoming days.

Pandemic of the Unvaccinated or Plandemic of People Coerced and Tricked into Getting Injected w/Poisons? Canadian Data Shows Nearly 70% of Recent COVID Deaths, Hospitalizations were among VAXED people

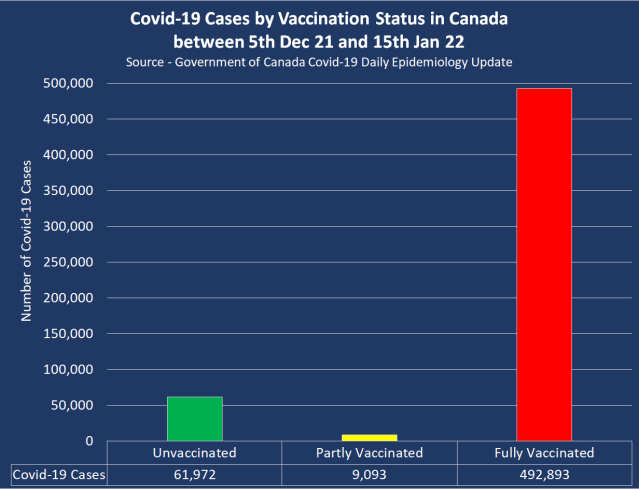
From [NN] and [GR] Data from the Canadian government revealed that deaths caused by the Wuhan coronavirus (COVID-19) mostly occurred among fully vaccinated people. With seven out of 10 fatalities happening among the fully vaccinated, Canada appears to be experiencing a “pandemic of the fully vaccinated.”

A report by LifeSiteNews looked at the numbers published in the government’s COVID-19 Daily Epidemiology Update. It scrutinized data between Jan. 16 and Jan. 22, where the surprising findings emerged.

During that time frame, 4,231 individuals were hospitalized across Canada. Hospitalized individuals who received two COVID-19 vaccine doses comprised 63 percent of the cases (2,656 people), while those injected with only one dose comprised nearly five percent (208 people).

Unvaccinated individuals who were hospitalized only numbered at 1,367, which was 32 percent of all hospitalizations. Those injected with the COVID-19 vaccine constituted a bigger portion of hospitalizations at 68 percent in all.

Canada also recorded 692 deaths due to COVID-19 during the same period. Just like hospitalizations, majority of COVID-19 fatalities between Jan. 16 and Jan. 22 were from those injected with at least one vaccine dose.

Of these 692 fatalities, 66 percent or 458 people were fully vaccinated, while three percent or 20 people received one vaccine dose. All in all, the vaccinated accounted for 69 percent of COVID-19 deaths. Unvaccinated Canadians only made up 31 percent of fatalities with 214.

The LifeSiteNews article pointed out that based on these numbers, the claim that COVID-19 injections can prevent 95 percent of hospitalizations and deaths appears to be false. “This does not make sense if the COVID-19 vaccines allegedly reduce the risk of death by 95 percent. But as seven in every 10 hospitalizations and deaths are among the vaccinated population in Canada, it’s becoming quite clear that the injections do not reduce the risk of death as alleged.”

Same pattern seen in Australia’s New South Wales

A similar observation was made in the eastern state of New South Wales (NSW) in Australia. Based on a report from its state government, about four of five COVID-19 cases, hospitalizations and deaths occurred mostly among those who were vaccinated. (Related: Report: 4 of every 5 COVID deaths in Australia are among VACCINATED people.)

An article by the Daily Expose shed light on this observation, using data from the Feb. 8 edition of the NSW Weekly COVID-19 Surveillance Report. The outlet looked at cases, hospitalizations and deaths in the state between Nov. 26, 2021 and Jan. 22.

In that span, NSW recorded a total of 540,330 COVID-19 cases. Vaccinated people amounted to 467,558 cases while the unvaccinated only comprised 72,772 cases. This equated to almost 87 percent of fully vaccinated residents contracting COVID-19, a stark contrast to only 13 percent of unvaccinated people who got infected.

Hospitalizations due to COVID-19 in NSW amounted to 6,475 – with 5,653 of those individuals sent to hospital being fully vaccinated. They comprised 87 percent of all hospitalizations, compared to only 13 percent or 822 unvaccinated individuals being hospitalized. Of the 421 deaths due to COVID-19 in the eastern Australian state, 323 people or 77 percent were vaccinated. Only 98 people or 23 percent of COVID deaths were unvaccinated.

Incidentally, both Canada and Australia are experiencing a surge in COVID-19 deaths – which appear to be driven by the vaccines themselves. COVID-19 deaths in Canada are at the same levels as the pandemic’s early days, when the vaccines had not been developed yet. Meanwhile, Australia’s COVID-19 fatalities peaked around the end of January and only started to drop recently.

UK Data Demonstrates that Adults who have Had 3 COVID Injections are 3 Times More Likely to be Infected with COVID than Adults who are not Vaccinated

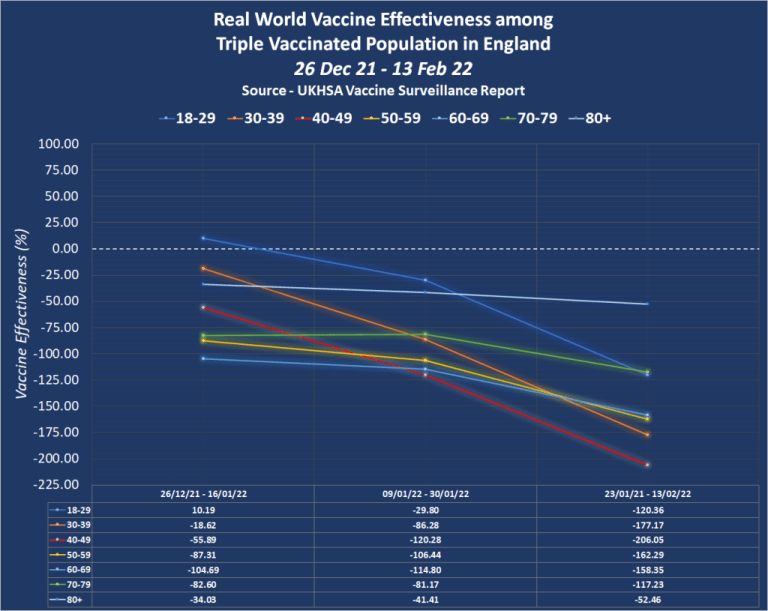
From [HERE] Adults in England who have succumbed to three doses of the Covid-19 injections are now up to three times more likely to be infected with Covid-19 than adults who are not vaccinated, with the latest UK Health Security Agency showing the Covid-19 injections have a negative effectiveness among the triple vaccinated as low as minus-206%.

Pfizer claim that there Covid-19 mRNA injection has a vaccine effectiveness of 95%. They were able to claim this because of the following –

During the ongoing clinical trial, 43,661 subjects were split evenly between the placebo and vaccine groups (about 21,830 subjects per group).

In the placebo group — the group that didn’t have the Pfizer Covid-19 vaccine — 162 became infected with the coronavirus and showed symptoms.

Whilst in the vaccine group — the group that got the real vaccine — that number was only 8.

Therefore the percentage of placebo group who became infected equated to 0.74% (162 / 21830 x 100 = 0.74).

Whilst 0.04% of the vaccinate group became infected (8 / 21830 x 100 = 0.04)

In order to calculate the efficacy of their Covid-19 mRNA injection, Pfizer then performed the following calculation –

They first subtracted the percentage of infections in the vaccinated group from the percentage of infections in the placebo group.

0.74% – 0.04% = 0.7%

Then they divided that total by the percentage of infections in the placebo group, which equated to 95%.

0.7 / 0.74 = 95%.

Therefore, Pfizer were able to claim that their Covid-19 mRNA injection is 95% effective.

We don’t need to go into the fact that this calculation was extremely misleading and only measured relative effectiveness rather than absolute effectiveness. Neither do we need to go into the fact that Pfizer chose to ignore thousands of other suspected infections during the ongoing trial and not perform a PCR test to confirm the infection because it would have thrown efficacy below the required minimum of 50% to gain regulatory approval.

The reason we don’t need to go into it is because the general public are being told that the Pfizer Covid-19 vaccine is 95% effective due to the calculation performed above. The same calculation was also used based on individual results to claim a vaccine efficacy of around 70% for AstraZeneca, and around 98% for Moderna.

Now, thanks to a wealth of data published by the new UK Health Security Agency we are able to use the same calculation that was used to calculate 95% effectiveness of the Pfizer vaccine, to calculate the real world effectiveness of the Covid-19 vaccines.

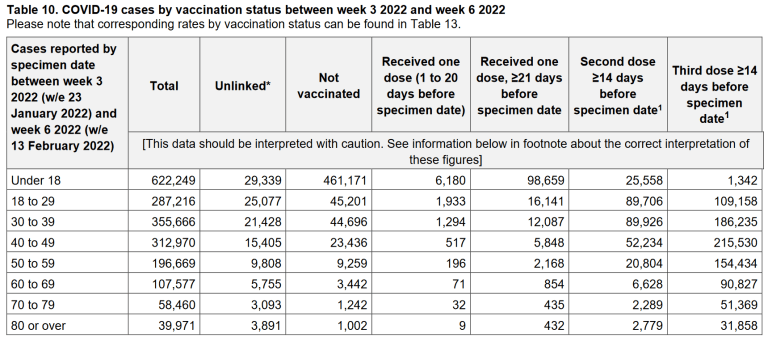
Table 10 of the UK Health Security Agency Vaccine Surveillance report, published 17th February 2022, shows the number of recorded infections by vaccination status between week 3 and week 6 of 2022.

The vast majority of infections have been seen among the triple vaccinated and double vaccinated population, with 215,530 confirmed infections among the triple vaccinated 40-49-year-olds alone. 

Covid-19 cultists would argue this is to be expected when so many people have chosen to get the Covid-19 injection, but unfortunately the UKHSA data confirms the Covid-19 cultists are wrong. 

Table 13 of the UKHSA Vaccine Surveillance Report shows the confirmed case rate among persons triple vaccinated, and rates among persons not vaccinated per 100,000 people. [MORE]

'You Are Injecting Toxins that Cause the Disease. This Isn't a Vaccine.' Pathologist Dr. Ryan Cole explains How COVID Injections Can Cause Catastrophic Damage to Organs and the Brain

From [NN] Pathologist Dr. Ryan Cole shared the dangers of the Wuhan coronavirus (COVID-19) vaccines at the White Coat Summit in July 2021. During the conference organized by America’s Frontline Doctors in Texas, he revealed that the vaccines cause catastrophic damage to human organs.

Cole elaborated on the SARS-CoV-2 spike protein used as the main component in the COVID-19 vaccines.

“We’re giving a gene sequence into the bodies of human beings, and that sequence goes into our deltoid where we’re informed that it has a little anchoring protein. Once that is translated and makes a little protein, it’s on the surface of your cell [and] it stays there,” he said. “Well, guess what – it doesn’t. This spike protein doesn’t just stay in the deltoid. [It] circulates in your blood [and] lands in multiple organs in the body.”

He cited studies performed on lab animals that involved the SARS-CoV-2 spike protein alone being injected into their bodies. The animals injected developed the same diseases present in the respiratory, cardiovascular and nervous systems of those with COVID-19.

The pathologist shared three examples of organs being damaged by the spike protein. Lung cells affected by the spike protein turned purple and blue due to the excess inflammation – which was caused by the spike protein binding to the ACE-2 receptors in the lungs. “[That’s the] inflammatory response, [your] immune system attacking your own body,” Cole said. (Related: Dr. Ryan Cole explains how the COVID vaccines compromise the immune system.)

He added that aside from the lungs, the spike protein also crosses the blood-brain barrier to disrupt and inflame blood vessels in the brain. “The brain fog you hear about from COVID-19 patients? Guess what, you [also] hear about it in the post-vaccinated, damaged individuals as well.”

Furthermore, Cole pointed out how the spike protein negatively impacts the heart – which has led to an increase in cardiac inflammation in younger Americans injected with the shot. “The pericardium [is] the sac that surrounds your heart. That’s inflammation that doesn’t belong there. Once you have heart damage, the heart does not heal itself. Once a heart cell is damaged, it’s damaged forever. It doesn’t replace itself with another heart cell, it replaces itself with a scar.”

“You want to give [children] a [COVID-19 vaccine] shot and we see about 200 times increase in myocarditis in our society right now? Let’s give a kid a toxin and ruin [their] heart for life? Insanity. We need to stop the insanity immediately,” he said.

Vaccines compromise the immune system

The CEO and medical director of Cole Diagnostics in Idaho later echoed his criticism of the spike protein used in the COVID-19 vaccines. He told Veronika Kyrylenko of the New American during a January interview that the SARS-CoV-2 spike protein used in the shots is responsible for compromising the immune system.

“It’s a spike protein that’s toxic to the human body, causes the same disease as the virus and is predisposing people to auto-immune attacks and potentially short-term cancer risks,” Cole said.

According to the pathologist, human cells possess toll-like receptors (TLRs) that classify whether a foreign object in the body is harmful or not. Vaccines turn off some of these TLRs, compromising the immune system’s alert mechanism as a result. Some of the receptors that get deactivated by vaccines include TLR7 and TLR8 in charge of viruses, and TLR3 and TLR4 which keep cancer in check.

“When the shots go into the body, they turn some of these TLRs off. Normally they have to be on,” said Cole.

Cole also mentioned how the vaccines inhibit tumor-suppressing genes. According to the pathologist, the spike protein binds to the P53 gene that suppresses tumors. The spike protein’s S1 subunit also binds to the TMPRSS-2 gene linked to prostate cancer in men and the BRCA genes linked to breast cancer.

“We’re giving a shot that makes a spike protein. That’s a toxin that [latches] to cancer genes in bad ways and turns off other pattern receptors. We don’t know how long the immune system is suppressed after these shots and how long these receptors are shut off.”

Video Graphs the Spikes in COVID Injection Deaths in Different Countries

Overwhelming Substantial Increase in Strokes as FDA and NIH Secretly Study Reports of Neurological Injuries After COVID Injections

From [HIN] The Epoch Times published an explosive report today stating that they have received emails that allegedly show that the U.S. Food and Drug Administration (FDA) and National Institutes of Health (NIH) have been quietly studying neurological problems that have appeared in people after they took a COVID-19 vaccine.

Two U.S. agencies have been quietly studying neurological problems that have appeared in people who have had COVID-19 vaccines, The Epoch Times has found.

The Food and Drug Administration (FDA) and National Institutes of Health (NIH) have been conducting separate research projects into post-vaccination neurological issues, which have manifested with symptoms like facial paralysis and brain fog and have been linked in some cases with the vaccines, according to emails reviewed by The Epoch Times.

One attempt to gain understanding of a problem that experts around the world are struggling to understand is being carried out by Dr. Janet Woodcock, who was acting commissioner of the FDA until Feb. 17.

Woodcock, now the FDA’s principal deputy director, has been personally evaluating neurologic side effects from the COVID-19 vaccines since at least Sept. 13, 2021, according to the emails, many of which have not been reported on previously. FDA epidemiologists are also gathering data to look into the issues, according to messages from Dr. Peter Marks, another top FDA official.

A team at the NIH’s National Institute of Neurological Disorders and Stroke (NINDS), meanwhile, started seeing patients reporting vaccine injuries for a study in early 2021 after receiving complaints shortly after the vaccines were made available. A portion of the patients was examined in person at the Bethesda, Maryland, facility.

None of the reviews or studies appear to have been announced, and health officials have said little about them publicly, despite a growing recognition among experts that at least some issues are likely linked to the vaccines. (Full article here. Copy here with no paywall.)

An examination of the FDA and CDC’s Vaccine Adverse Events Reporting System (VAERS) confirms that deaths and injuries due to neurological issues following COVID-19 injections have skyrocketed, when compared to the same adverse events reported following all FDA-approved vaccines for the previous 30 years.

And while none of the U.S. Health Agencies have published or made public their research on these post-vaccine neurological injuries, many medical journals have.

The COVID-19 experimental vaccines, which were given emergency use authorization illegally, should have been immediately pulled from the market at least a year ago.

Will these criminals in the pharmaceutical industry who pay billions of dollars to get their products approved by the FDA ever face justice for the mass murder they have caused?

Almost 3000% Increase in Neurological Injuries Following COVID-19 Vaccines

According to the Cleveland Clinic, “neuropathy” is:

damage or dysfunction of one or more nerves that typically results in numbness, tingling, muscle weakness and pain in the affected area. Neuropathies frequently start in your hands and feet, but other parts of your body can be affected too.

Neuropathy, often called peripheral neuropathy, indicates a problem within the peripheral nervous system. Your peripheral nervous system is the network of nerves outside your brain and spinal cord. Your brain and spinal cord make up your central nervous system. Think of the two systems working together this way: Your central nervous system is the central station. It is the control center, the hub from which all trains come and go. Your peripheral nervous system are the tracks that connect to the central station. The tracks (the network of nerves) allow the trains (information signals) to travel to and from the central station (your brain and spinal cord).

Neuropathy results when nerve cells, called neurons, are damaged or destroyed. This disrupts the way the neurons communicate with each other and with the brain. Neuropathy can affect one nerve (mononeuropathy) or nerve type, a combination of nerves in a limited area (multifocal neuropathy) or many peripheral nerves throughout the body (polyneuropathy). (Source.)

To determine the number of neurological injuries and deaths occurring after COVID-19 vaccines, and then compare them to the previous 30 years’ historical data following all other FDA approved vaccines, we need to perform several searches in VAERS.

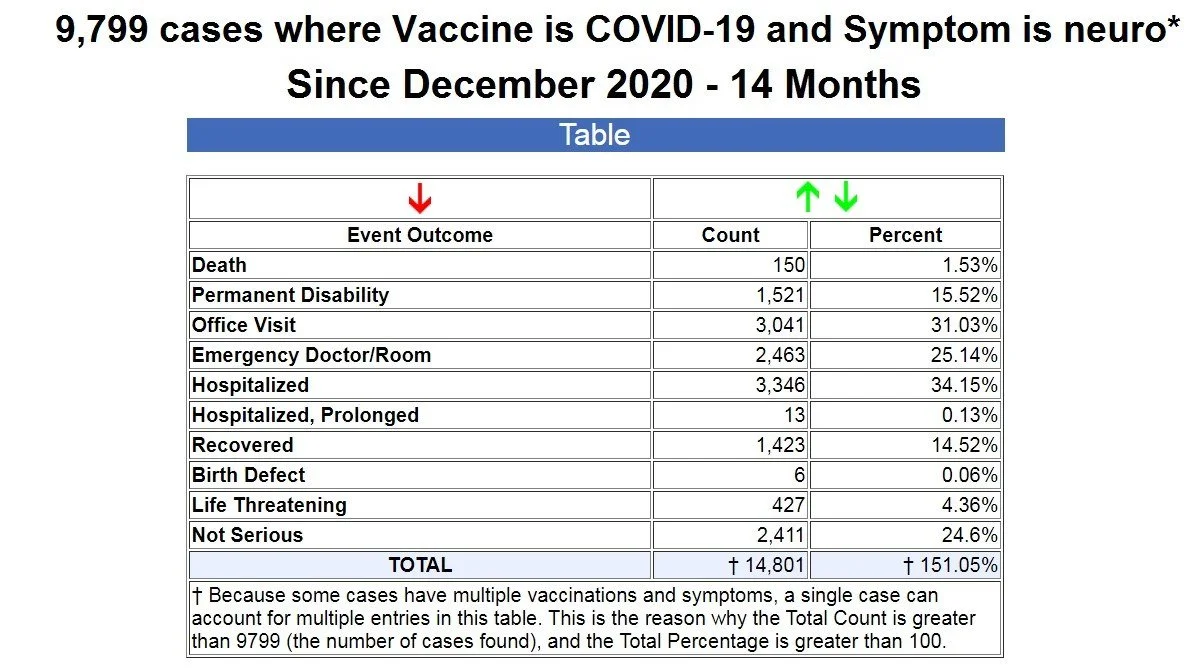
So I began by searching for all symptoms in VAERS that contained “neuro” following COVID-19 shots, and it returned 9,799 cases as of the latest data dump into VAERS this past Friday, which goes through February 11, 2022.

As you can see from the table above, in 14 months since the emergency use authorization of the COVID-19 vaccines, out of the 9,799 reported cases, there have been 150 deaths, 1,521 permanent disabilities, 2,463 ER visits, and 3,359 hospitalizations. (Source.)

By way of comparison, for the previous 30+ years starting in 1990 when VAERS was established, using the exact same search for every symptom containing “neuro,” we get a result of 8,492 cases for ALL FDA-approved vaccines for the past 30+ years combined. (Source.)

The yearly averages then look like this:

  • 8399 cases of neurological injuries per year following COVID-19 vaccines

  • 283 cases of neurological injuries per year following all FDA-approved vaccines combined

That’s a 2,867% increase of neurological injuries following COVID-19 vaccines as compared to all other vaccines approved by the FDA.

Over 3000% Increase in Cases of Palsy Following COVID-19 Vaccines

There are, of course, other symptoms that are considered neurological conditions that do not contain the word “neuro” in the name of the disease.

Bell’s Palsy, facial paralysis, is one that has been reported frequently following COVID-19 vaccines and is considered a “neurological” injury.

So I searched VAERS for all cases of any kind of “palsy” following COVID-19 vaccines, and it returned a result of 6,717 cases. [MORE]

Bombshell Journal Study Examines the Links between 5G Wireless Exposure and COVID

From [NN] New research published in the Journal of Clinical and Translational Research highlights the link between Wuhan coronavirus (Covid-19) symptoms and 5G wireless radiation.

While much of the focus has centered around the virus itself, the paper looks at the environmental impacts that exacerbate the disease, including radiofrequencies from mobile phone towers.

“In considering the epidemiological triad (agent-host-environment) applicable to all disease, we investigated a possible environmental factor in the COVID-19 pandemic: ambient radiofrequency radiation from wireless communication systems including microwaves and millimeter waves,” the paper explains.

“SARS-CoV-2, the virus that caused the COVID-19 pandemic, surfaced in Wuhan, China shortly after the implementation of city-wide (fifth generation [5G] of wireless communications radiation [WCR]), and rapidly spread globally, initially demonstrating a statistical correlation to international communities with recently established 5G networks.”

Beverly Rubik and Robert R. Brown, the two study authors, looked at peer-reviewed scientific literature on the detrimental bioeffects of WCR. They identified several mechanisms by which WCR may have contributed to the Fauci Flu plandemic as a toxic environmental cofactor. (Related: Evidence shows that 5G is also destroying wildlife.)

By cross boundaries between the disciplines of biophysics and pathophysiology, the duo put forth the following evidence showing that 5G exposure:

• Causes morphologic changes in erythrocytes including echinocyte and rouleaux formation that can contribute to hypercoagulation

• Impairs microcirculation and reduces erythrocyte and hemoglobin levels exacerbating hypoxia

• Amplifies immune system dysfunction, including immunosuppression, autoimmunity and hyperinflammation

• Increases cellular oxidative stress and the production of free radicals leading to vascular injury and organ damage

• Increases intracellular Ca2+ (calcium ions) essential for viral entry, replication and release, as well as promotes pro-inflammatory pathways

• Worsens heart arrhythmias and cardiac disorders

Does 5G exposure cause really severe covid?

Not only 5G but also low-level WCR from various devices, including local networking systems, Wi-Fi (officially IEEE 802.11b Direct Sequence protocol; IEEE, Institute of Electrical and Electronic Engineers), and even mobile phones themselves are creating internal toxicity and cellular damage.

Non-thermal bioeffects, meaning the power density that causes tissue heating, from very low-level WCR exposure has also been reported in the scientific literature at power densities below the International Commission on Non-Ionizing Radiation Protection (ICNIRP) exposure guidelines.

“Low-level WCR has been found to impact the organism at all levels of organization, from the molecular to the cellular, physiological, behavioral, and psychological levels,” the study explains.

“Moreover, it has been shown to cause systemic detrimental health effects including increased cancer risk, endocrine changes, increased free radical production, deoxyribonucleic acid (DNA) damage, changes to the reproductive system, learning and memory defects, and neurological disorders.”

While the earth itself has always emitted low-level natural radiofrequencies in the background, they are so low that our bodies do not respond negatively to them. This is not the case for artificial RFs emitted by an increasingly more pervasive WCR presence in everyday life.

Interestingly, the progression of covid in terms of severe disease closely parallels the adverse effects caused by 5G exposure. These include blood changes, oxidative stress, immune system disruption and activation, increased intracellular calcium and cardiac effects.

“For example, blood clotting and inflammation have overlapping mechanisms, and oxidative stress is implicated in erythrocyte morphological changes as well as in hypercoagulation, inflammation, and organ damage,” the study explains.

“There is a substantial overlap in pathobiology between COVID-19 and WCR exposure. The evidence presented here indicates that mechanisms involved in the clinical progression of COVID-19 could also be generated, according to experimental data, by WCR exposure. Therefore, we propose a link between adverse bioeffects of WCR exposure from wireless devices and COVID-19.”

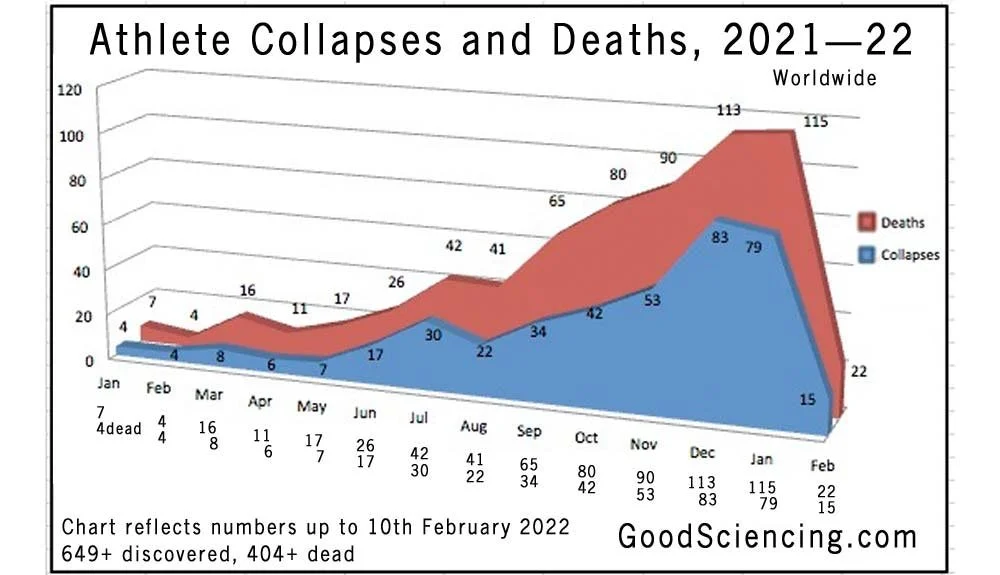
There Have Been at Least 707 Athlete Cardiac Arrests, Serious Issues, 446 Dead, After COVID Shot

From [REALSCIENCE] It is definitely not normal for so many mainly young athletes to suffer from cardiac arrests or to die while playing their sport, but this year it is happening. Many of these heart issues and deaths come shortly after they got a COVID vaccine. While it is possible this can happen to people who did not get a COVID vaccine, the sheer numbers clearly point to the only obvious cause.

The so-called health professionals running the COVID vaccine programs around the world keep repeating that “the COVID vaccine is a normal vaccine and it is safe and effective.”

Gary Dempsey, professional soccer player played 500 games over 20 years, with no cardiac arrests.

So in response to their pronouncement, here is a non-exhaustive and continuously growing list of mainly young athletes who had major medical issues in 2021/2022 after receiving one or more COVID vaccines. Initially, many of these were not reported. We know that many people were told not to tell anyone about their adverse reactions and the media was not reporting them. They started happening and ramping up after the first COVID vaccinations. The mainstream media still are not reporting most, but sports news cannot ignore the fact that soccer players and other stars collapse in the middle of a game due to a sudden cardiac arrest. Many of those die – more than 50%.

We also note that many posts in Facebook, Instagram, twitter, forums and news stories are being removed. So now we are receiving some messages saying there is no proof of the event or of vaccination status. That is partly because this information is being hidden.

More people are writing to tell us that in many cases, we didn’t mention a person’s vaccination status. There is a good reason for that. None of the clubs want to reveal this information. None of their sponsors want to reveal it. The players have been told not to reveal it. Most of their relatives will not mention it. None of the media are asking this question. So what should we do? Stop this now? No, we will collect as much information as we can, while it is still available, because eventually, more information will come out, and we will be here to put it together. Will it mean anything? We don’t know. What we do know is that there is a concerted world-wide effort to make this information go away, so that fact alone tells us it must be collected, investigated and saved so other researchers can look at it to see if there are any useful patterns.

We really appreciate the athletes named in this list who have confirmed what happened to them so the truth can be known. They care about their fellow athletes, even if the clubs, their sponsors, media and politicians care more about money.

Prior Year Data

Also, a few people are suggesting that if we don’t document prior years, our data has no value. That doesn’t make any sense – a data collection study doesn’t have to go back to prior years. It can trigger off other data. Go look at Wikipedia – they have old lists – just filter out the old age and cancer deaths, because we’re not including those. We’re not going to do that research, at least not right now because we have our hands full documenting the rapidly escalating number of current cases. The chart in this post clearly shows the growth of adverse events on sports people. We leave it to others to document the previous years – at least for now – or send us a link or the data that others have collected and we will use it.

Also, one person says we are hiding things because we’re only showing “the barest” of 2022. Sorry about that, but we don’t have a crystal ball to see into the future. The only things we expect are that a) some people will continue to be “surprised” about the number of athlete deaths over the coming months, and b) although it is February, injuries and deaths that happened in prior months will be continue to be discovered in the future..

Dates of First Vaccinations

The dates of first “available” vaccinations vary all over the world, in different states and different cities. We have a small collection of data in a separate story and we know there were trials in the months before official rollouts, so just because a country started its rollout on a particular date, that doesn’t mean some people didn’t receive their vaccinations in the weeks and months earlier. If we get definitive proof that someone was not vaccinated, we amend the record. Officials and the media are now doing a great job of hiding all the useful information. They are also calling vaccinated people unvaxed if it hasn’t been more than two weeks after their vaccination, and if they are due for their booster and they don’t get it, they are labeled unvaxed. (i.e. the government and media are telling lies – it is a clever scheme, but it is still a lie.)

For example, Australia’s first human trials of a candidate COVID-19 vaccine was the Novavax NVX-CoV2373 in Melbourne by 26 May 2020. There is no documentation showing who took part in the trials The Therapeutic Goods Administration approved the Pfizer–BioNTech vaccine on 25 January, the Oxford–AstraZeneca vaccine on 16 February, and Janssen vaccine on 25 June. Phase-1a started on 21 February 2021 and phase-1b of the roll-out began on 22 March.

The Philippines began phase 3 COVID-19 vaccine trials in early November 2020. Phase 3 is the point at which thousands of people are vaccinated, prior to consideration for approval for rollout, and people were being vaccinated in the previous months.

Clubs Hide Vaccination Information Now

Here is a demonstration of how sports clubs do not want the injuries of deaths of their players to be associated with the COVID vaccines. It tells the story of why they will not report which of their players has been vaccinated and when. Sunderland FC manager Lee Johnson suggested that the COVID vaccines may have caused the heart issues for his goalkeeper, Lee Burge. The club then sacked the manager.

Form your own conclusions as to why the club would sack the manager who cares about his players.

Definite Proof of Vaccination

The so-called fact-checkers are trying to say that because we don’t always have definitive proof of vaccination, then 100% of the data we’re collecting is worthless. Well, good news, fact-checkers, you are not only wrong, you are idiots.

While historically there have been a relatively small number of athlete deaths each year that weren’t from old age or cancer, there has never been anything like what is happening since the COVID vaccination trials started. And they know it, but they don’t care. We will continue to gather as much information as possible about every person who dies. These are real people, not just numbers.

As we said elsewhere, we’re collecting data. Other people can use this data and add to it, if they can, to research whatever they want. We won’t de distracted from that, even if families, clubs, governments and the media hide information from us. We don’t want to hurt families, but families can’t hide real data because that could harm other people.

According to governments, 90-95% of populations all over the world are now vaccinated, so the fact-checkers have a problem. If that is true, then just about everyone is vaccinated. If it isn’t true, then governments are lying, possibly for the purpose of coercing those who don’t want their vaccinations, for various reasons. We will publish as much data as we can find, and from time to time, we and readers will discover information that wasn’t found earlier, and it will be added. [MORE]

Funeral Home Stocks Surge, Death and Disability Payouts Soar

STORY AT-A-GLANCE

  • Business is booming at funeral homes across the U.S. as death rates creep up, particularly among young, working-age individuals

  • Ex-Blackrock fund manager Ed Dowd has been analyzing data about mortality rates before and after COVID-19 shots became widespread, and found that death rates worsened in 2021 — after the shots became prevalent — compared to 2020

  • Insurance companies are seeing increases in payouts for death and disability; Lincoln National stated death claims have increased 13.7% year over year and 54% in quarter 4 compared to 2019

  • Scott Davison, the CEO of insurance company OneAmerica, reported the death rate for 18- to 64-year-olds has risen 40% compared to before the pandemic

  • A study by Dr. Peter McCullough and colleagues suggests people who’ve received COVID-19 shots may have damage to their innate immune system that’s leading to a form of acquired immunodeficiency syndrome

From [MERCOLA PDF] Business is booming at funeral homes across the U.S., as death rates creep up, particularly among young, working-age individuals.1 Ex-Blackrock fund manager Ed Dowd has been analyzing data about mortality rates before and after COVID-19 shots became widespread, and found that death rates worsened in 2021 — after the shots became prevalent — compared to 2020.

As reported by Zero Hedge, Dowd pointed out “a spike in mortality among younger, working-age individuals coincided with vaccine mandates. The spike in younger deaths peaked in Q3 2021 when COVID deaths were extremely low (but rising into the end of September).”2

Dowd also reported data from public funeral home company Carriage Services, which announced a 28% increase in September 2021 compared to September 2020, while August had a 13% increase. He tweeted:3,4

“Business has been quite good since the introduction of the vaccines & the stock was up 106% in 2021. Curious no? Guys this is shocking as 89% of Funeral homes are private in US. We are seeing the tip of the iceberg.”

Life Insurance Payouts on the Rise

Insurance companies are also seeing increases in payouts for death and disability. Dowd tweeted February 1, 2022, that financial insurance company Unum reported a 9% increase in their benefit ratio (payouts versus premiums) in their life segment.5 Dowd tweeted:6

“In 2021 they saw a 17.4% increase vs 2020. This is higher than the 13.3% increase vs 2019. So the higher payouts in 21 are occurring with a miracle vaccine & less virulent strains … In 2019 the unit had $266 million profit, last year a profit of $82 million & this year a loss of -$192 million. A swing of $458 million lower over 2 years. Important to remember these are employed working age folks.”

Scott Davison, the CEO of Indiana-based insurance company OneAmerica, also reported disturbing statistics — the death rate for 18- to 64-year-olds has risen 40% compared to before the pandemic.7

"We are seeing, right now, the highest death rates we have seen in the history of this business – not just at OneAmerica," Davison said, adding, “Just to give you an idea of how bad that is, a three-sigma or a one-in-200-year catastrophe would be 10% increase over pre-pandemic. So 40% is just unheard of.” Further, most of the deaths are not due to COVID-19. He said:8

"What the data is showing to us is that the deaths that are being reported as COVID deaths greatly understate the actual death losses among working-age people from the pandemic. It may not all be COVID on their death certificate, but deaths are up just huge, huge numbers."

Disability Claims and Hospital Death Rates Rise

Disability claims, initially short-term claims and now long-term claims, have also seen an “uptick.” At a news conference where Davison spoke, Brian Tabor, president of the Indiana Hospital Association, confirmed that hospitals are also seeing widespread ill health and rising death rates. Zero Hedge reported:9

“Brian Tabor, the president of the Indiana Hospital Association, said that hospitals across the state are being flooded with patients ‘with many different conditions,’ saying ‘unfortunately, the average Hoosiers’ health has declined during the pandemic.’

In a follow-up call, he said he did not have a breakdown showing why so many people in the state are being hospitalized — for what conditions or ailments. But he said the extraordinarily high death rate quoted by Davison matched what hospitals in the state are seeing. ‘What it confirmed for me is it bore out what we're seeing on the front end ...’ he said.”

Other insurance companies citing higher mortality rates include Hartford Insurance Group, which announced mortality increased 32% from 2019 and 20% from 2020 prior to the shots. Lincoln National also stated death claims have increased 13.7% year over year and 54% in quarter 4 compared to 2019.10 Dowd tweeted:11

“Randy Frietag CFO just explained that in 2021 the share of young people dying from covid doubled in the back half of the year & that's driven the result for Lincoln & its peers. He cited 40% in 3Q and 35% in 4Q were below the age of 65 … Mandates are killing folks … This shouldn’t be happening with miracle vaccines in a working age population period and a mild Omicron.”

As ZeroHedge noted, what we need to know from the insurance companies is what the leading causes of death were for 2020 and 2021, as well as how many received COVID-19 shots among those who died.

It continued, “Reinsurance Group of America, for example, reported a profit in Q4 2020 when the most of the population was unvaccinated and amid a deadlier strain of Covid-19, yet they registered a loss in Q4 2021 with more than 60% of the country fully vaccinated (and around 75% who have received at least one dose).”12

In other words, they paid out more in death and disability benefits in late 2021, after the shots became widespread, then they did at the peak of the pandemic, when no shots (or only a small number) had been issued.

Deaths Keep Rising Despite Mass Injection Campaign

Around the globe, it’s become clear that excess deaths continue to explode, despite the mass injection campaign that was supposed to save us. In the week ending November 12, 2021, the U.K. reported 2,047 more deaths than occurred during the same period between 2015 and 2019.

However, COVID-19 cannot be entirely to blame, as it was listed on the death certificates for only 1,197 people.13 Further, since July, non-COVID deaths in the U.K. have been higher than the weekly average in the five years prior to the pandemic.

Heart disease and strokes appear to be behind many of the excess deaths, with Financial Times reporting, “The new phase of excess deaths raises the possibility that since the summer more people have been losing their lives as a result of strains on the NHS or lack of early diagnosis of serious illness …”14

On Twitter, Silicon Valley software engineer Ben M. (@USMortality) similarly revealed that in a 13-week period alone, about 107,700 seniors died above the normal rate, despite a 98.7% vaccination rate.15 In another example, he used data from the U.S. Centers for Disease Control and Prevention, census.gov and his own calculations to show excess deaths rising in Vermont even as the majority of adults have been injected.

“Vermont had 71% of their entire population vaccinated by June 1, 2021,” he tweeted. “That’s 83% of their adult population, yet they are seeing the most excess deaths now since the pandemic!”16

An investigation by The Exposé, using official data from NHS and the U.K.’s Office for National Statistics (ONS), also found that deaths among teenagers increased 47% since they started getting COVID-19 shots.17 Not only that, but deaths from COVID-19 also went up among 15- to 19-year-olds after the shots were rolled out for this age group.

COVID-19 Shots Causing Acquired Immunodeficiency Syndrome

A study by board-certified internist and cardiologist, and editor of two medical journals, Dr. Peter McCullough and colleagues suggests people who’ve received COVID-19 shots may have damage to their innate immune system that’s leading to a form of acquired immunodeficiency syndrome.18

The mRNA COVID-19 shots use genetically modified mRNA encoding spike proteins. This results in mRNA being hidden from cellular defenses, “promote[s] a longer biological half-life for the proteins, and provoke[s] higher overall spike protein production,” the study suggests.19

The researchers state that experimental and observational evidence show that the human immune response to COVID-19 shots is very different than the response induced by exposure to SARS-CoV-2:20

“[T]he genetic modifications introduced by the vaccine are likely the source of these differential responses. In this paper, we present the evidence that vaccination, unlike natural infection, induces a profound impairment in type I interferon signaling, which has diverse adverse consequences to human health. 

We explain the mechanism by which immune cells release into the circulation large quantities of exosomes containing spike protein along with critical microRNAs that induce a signaling response in recipient cells at distant sites. 

We also identify potential profound disturbances in regulatory control of protein synthesis and cancer surveillance. These disturbances are shown to have a potentially direct causal link to neurodegenerative disease, myocarditis, immune thrombocytopenia, Bell’s palsy, liver disease, impaired adaptive immunity, increased tumorigenesis, and DNA damage.” 

The study includes evidence from the Vaccine Adverse Event Reporting System (VAERS) to support its hypothesis. While health officials refuse to acknowledge that COVID-19 shots have caused deaths, clinically trained reviewers analyzed a sample of COVID-19 vaccine deaths reported in VAERS and found that only 14% of them were certainly not due to the vaccine.21

This means that the remaining 86% may have been related to the shots. Further, while it’s often stated that VAERS reports are made by laypeople, and therefore suggested to be unreliable, the review found that at least 67% of the COVID-19 vaccine death reports they analyzed were made by health service employees.22

Overall, McCullough and colleagues warn that COVID-19 shots subvert innate immunity, which could reduce the ability to combat future infections. Further, once damaged by the shots, the immune system may be less able to detect and prevent malignant transformation within cells.

They also suggest that exposure to spike protein-containing exosomes and mRNAs may induce an inflammatory cascade that further leads to disease. In concluding that COVID-19 shots are not positive contributors to public health, the study notes:23

“In the end, we are not exaggerating to say that billions of lives are at stake. We call on the public health institutions to demonstrate, with evidence, why the issues discussed in this paper are not relevant to public health, or to acknowledge that they are and to act accordingly. 

Until our public health institutions do what is right in this regard, we encourage all individuals to make their own health care decisions with this information as a contributing factor in those decisions.”

Can You Lessen the Potential Damage?

Those considering COVID-19 shots must carefully weigh the evidence of risks before making a decision. But if you’ve already been injected and want to reduce your risk of any potential complications, there are a few basic strategies I recommend:

  • Measure your vitamin D level and take enough vitamin D orally (typically about 8,000 units/day for most adults) and/or get sensible sun exposure to make sure your level is 60 to 80 ng/ml (150 to 2000 nmol/l).

  • Eliminate all vegetable (seed) oils in your diet, which involves eliminating nearly all processed foods and most meals in restaurants unless you can be sure the chef is cooking only with butter. Avoid any sauces or salad dressings in restaurants, as they are loaded with seed oils. Also avoid chicken and pork, as they are rich in linoleic acid, the omega-6 fat that nearly everyone consumes far too much of and contributes to oxidative stress.

  • Consider taking around 500 milligrams a day of NAC, as it helps prevent blood clots and is a precursor for your body to produce the important antioxidant glutathione.

  • Consider taking fibrinolytic enzymes, which digest the fibrin that leads to blood clots, strokes and pulmonary embolisms. The dose is typically two, twice a day, but must be taken on an empty stomach, either an hour before or two hours after a meal. Otherwise, the enzymes will digest your food and not the fibrin in the blood clot.

Autopsies of Two Teenage Boys who Died Days after Getting Pfizer’s COVID Injection Prove the Shots Caused their Deaths

From [CHD] and [HIRSHORN] Pathologists who examined the autopsies of two teenage boys who died days after receiving Pfizer’s COVID-19 vaccine concluded the vaccine caused the teens’ deaths.

The three pathologists, two of whom are medical examiners, published their findings Feb. 14 in an early online release article, “Autopsy Histopathologic Cardiac Findings in Two Adolescents Following the Second COVID-19 Vaccine Dose,” in the Archives of Pathology and Laboratory Medicine.

The authors’ findings were conclusive. Two teenage boys were pronounced dead in their homes three and four days after receiving the second Pfizer-BioNTech COVID-19 dose.

There was no evidence of active or previous COVID-19 infection. The teens had negative toxicology screens (i.e. no drugs or poisons were present in their bodies).

These boys died from the vaccine.

Histopathological examination of their cardiac tissue revealed an important new finding: Neither heart demonstrated evidence of typical myocarditis.

Instead, the authors found evidence of microscopic changes consistent with a different form of heart injury called toxic cardiomyopathy. They wrote:

“The myocardial injury seen in these post-vaccine hearts is different from typical myocarditis and has an appearance most closely resembling a catecholamine-mediated stress (toxic) cardiomyopathy.”

The authors further explained what they observed under the microscope:

“Their histopathology does not demonstrate a typical myocarditis … In these two post-vaccination instances, there are areas of contraction bands and hypereosinophilic myocytes distinct from the inflammation.

“This injury pattern is instead similar to what is seen in the myocardium of patients who are clinically diagnosed with Takotsubo, toxic or ‘stress’ cardiomyopathy, which is a temporary myocardial injury that can develop in patients with extreme physical, chemical, or sometimes emotional stressors.

“Stress cardiomyopathy is a catecholamine-mediated ischemic process seen in high catecholamine states in the absence of coronary artery disease or spasm. It has also been called ‘neurogenic myocardial injury’ and ‘broken heart syndrome.’”

The pathologists determined there was a different mechanism of heart injury at play in these two boys, distinct from a purely infectious process that would result directly from a viral infection like COVID-19.

This is an important finding. There may be a way to distinguish cardiac injury resulting from a SARS-COV-2 infection from cardiac injury where the vaccine predisposes the patient to stress cardiomyopathy before contracting COVID-19.

However, the authors are careful not to assume that cardiac injuries from COVID-19 and COVID-19 vaccines can always be sorted out under the microscope.

They explain that stress cardiomyopathy, or “broken heart syndrome,” may also occur in a rare hyperinflammatory state that is known to occur in COVID-19 infection as well:

“This post-vaccine reaction may represent an overly exuberant immune response and the myocardial injury is mediated by similar immune mechanisms as described with SARS-COV-2 and multisystem inflammatory syndrome (MIS-C) cytokine storms.”

The authors admit this pathological finding may also occur as a result of MIS-C, a known complication of SARS-COV2 infection.

Learning more about this condition requires a biopsy of heart tissue, or in this case an autopsy. We know very little about the nature of myocarditis in people who are clinically stable because heart biopsies are not conducted on them and autopsies are rarely done on patients who die from COVID-19.

There still is no practical way of screening for cardiac injury beyond assessing symptoms.

Unfortunately, the two boys did not have symptoms of myocarditis (fever, chest pain, palpitations, or dyspnea) prior to their cardiac arrest and death. One complained of a headache and gastric upset which resolved. The other had no complaints.

This is extremely concerning. These boys had smoldering, catastrophic heart injuries with no symptoms.

How many others have insidious cardiac involvement from vaccination that won’t manifest until they get a serious case of COVID-19 or the flu? Or perhaps when they subject themselves to the physical stress of competitive sports?

These findings suggest a significant subset of COVID-19 deaths in the vaccinated could be due to the vaccines themselves.

Furthermore, it raises this question: How often does this condition exist in a latent form in vaccinated individuals?

The CDC believes the risk of vaccine-induced myocarditis not significant

The Centers for Disease Control and Prevention (CDC) says the risk of myocarditis and pericarditis in adolescents who get the COVID-19 vaccine is “extremely rare” and “most cases are mild.”

But those assurances conflict with the agency’s own data.

The CDC’s Advisory Committee on Immunization Practices (ACIP) presented this disquieting information (see chart below) during its June 23, 2021 meeting convened specifically to address the risks of myo/pericarditis in 12- to 15-year-olds who received Pfizer’s COVID vaccine:

This slide is important for two reasons.

First, the incidence of this potentially lethal condition is significantly higher in the vaccinated (“Observed” column) compared to the background rate (“Expected” column), especially in males in the 18- to 24-year-old age range.

In the 12- to 17-year-old male cohort, the risk of myo/pericarditis is at least 11 times higher than the background rate.

With more than 2 million doses administered at the time when these cases of myo/pericarditis were identified, we can be confident these data represent an undeniable safety signal.

The second reason this slide is important is this: The CDC is drawing directly from the Vaccine Adverse Event Reporting System (VAERS), a system specifically designed to monitor for safety signals when vaccines are administered to the public.

As of Feb. 15, the CDC continues to assure the public that “Reports of adverse events to VAERS following vaccination, including deaths, do not necessarily mean that a vaccine caused a health problem.”

In essence, the CDC is acknowledging that reports of deaths and other adverse events following vaccination exist in VAERS but do not comprise any risk because causality has not been verified.

Then why did the ACIP choose to accept VAERS as a legitimate source of information on myo/pericarditis in their calculations?

The CDC released its conclusions immediately following the ACIP meeting:

“The facts are clear: this is an extremely rare side effect, and only an exceedingly small number of people will experience it after vaccination. Importantly, for the young people who do, most cases are mild, and individuals recover often on their own or with minimal treatment.”

But how do they know this?

One month after this comforting statement from the CDC, the U.S. Food and Drug Administration (FDA) admitted in this letter to Pfizer that the agency was not able to adequately assess the risk of myocarditis from Pfizer’s product:

“We have determined that an analysis of spontaneous postmarketing adverse events reported under section 505(k)(1) of the FDCA [Federal Food, Drug and Cosmetic Act] will not be sufficient to assess known serious risks of myocarditis and pericarditis and identify an unexpected serious risk of subclinical myocarditis.

“Furthermore, the pharmacovigilance system that FDA is required to maintain under section 505(k)(3) of the FDCA is not sufficient to assess these serious risks.”

Commenting on the FDA’s letter, Dr. Meryl Nass said, “The FDA is saying that neither an analysis of the data in VAERS or of any of the other taxpayer-funded databases will provide sufficient assessment of the risk of this product.”

“This is a joke,” said Nass, adding:

“All this data, plus software, plus a team of analysts, and the FDA says it can’t assess the risk of myocarditis, despite identifying thousands of cases?

“Furthermore, unsaid, but implied by the FDA, is that if the FDA is incapable of assessing the risk of myocarditis despite thousands of reported cases, it cannot or will not be capable of assessing the other serious adverse events that have been reported in conjunction with COVID vaccines.”

If the FDA is not able to perform adequate surveillance of safety signals around vaccine-induced myocarditis, who will?

The FDA assigns this unenviable but essential task to Pfizer itself (again, from the FDA’S letter to Pfizer):

“Therefore, based on appropriate scientific data, we have determined that you are required to conduct the following studies…”

Is myocarditis ‘extremely rare’ after COVID-19 vaccination? 

As of Feb. 4, VAERS reported 495 cases of myo/pericarditis in 12- to 17-year-olds. VAERS data show that as of Feb. 10, there were 2,239 reported cases of myocarditis in people under the age of 30.

However, a widely cited CDC-sponsored study (Lazarus et al) concluded the incidence of adverse events is 10 to 100 times higher than are reported to VAERS.

More recent calculations estimate that adverse events are underreported by a factor of approximately 41.

From these estimates, we can conclude there may have been approximately 20,000 cases of myocarditis in 12- to 17-year-olds since Pfizer’s COVID-19 vaccine received Emergency Use Authorization and was rolled out to this age group..

The VAERS data from June 11, 2021 from the table above show 132 cases of myo/pericarditis were observed in 2,039,000 doses given to 12- to 17-year-old males. This is approximately 6.5 cases in 100,000 doses.

This study from Hong Kong found the incidence of myo/pericarditis after two doses with Pfizer’s Comirnaty vaccine was 37 in 100,000. This incidence matches nearly exactly with findings from this study that used the Vaccine Safety DataLink (VSD) system (37.7 12-17 year olds per 100,000 suffered myo/pericarditis after their second dose). This is more evidence that significant underreporting is in play in the VAERS system.

Will most of these teens “recover on their own”? How many other vaccinated people have varying degrees of “broken heart” syndrome that remain asymptomatic, undiagnosed and unreported?

These new findings indicate that no one can answer these questions right now — especially not the CDC and the FDA.

If the FDA has admitted it cannot assess the risk of myocarditis using the surveillance systems in place, how then is the CDC able to assure us that the risk is low enough to continue to proceed with a vaccination campaign that now includes 5- to 11-year-old children?

The FDA has abdicated its responsibility for monitoring the safety of these vaccines to the vaccine manufacturers.

The CDC is using VAERS data in its own analyses while urging the public to discount all adverse events, including deaths, that appear in the very same database.

There isn’t any regulation happening here. Our regulatory agencies have become mouthpieces for the very industry they are tasked to oversee.

Dr. Joseph Mercola Asks and Answers: Why Are Professional Athletes Collapsing on the Field, all Over the World?

From [HERE] U.K. football legend and sports commentator, Matt Le Tissier, has been speaking out about the large number of athletes who have collapsed or died on the field, and has lost his job as a result

Le Tissier says he has never seen anything like it in the 17 years he played football; he is calling for an investigation into the events and says ignoring it is a “massive dereliction of duty” by the officials

Fact-checkers and government officials are trying to negate or discredit information that supports the theory that mRNA injections are behind the sudden onslaught of injury and death, and they are studiously ignoring investigating the allegations

The Vaccine Adverse Events Reporting System (VAERS) reflects injuries to athletes in the general population, but it’s possible that the reports are nowhere near currentWith every passing day, the list of people suffering tragic consequences from the COVID mRNA shots grows longer. Data1 show 23,149 people have died after a COVID jab as of January 28, 2022. There also are 13,575 reports of people with Bell’s palsy, 41,163 who are permanently disabled, 31,185 with myocarditis, 11,765 who have had heart attacks and 3,903 women who have lost their babies after getting the shots.

Many of these people and their stories have remained hidden from public view. YouTube, Instagram, Facebook and other social media platforms have censored the personal stories and videos of individuals documenting their injuries and permanent disabilities, so those who only read mainstream media are unaware of the overwhelming damage being done in the name of science.

However, there is a population of people whose injuries and death have been made public. In the past six months, a slew of professional and amateur athletes have collapsed and died on the field. Yet, mainstream media appear to take this in stride, acting as if what is happening is completely normal.

But, as described by Matt Le Tissier in the first seconds of the video above, this is far from normal. Le Tissier was a soccer legend2 (a sport called football in the U.K.). His prowess on the field earned him the nickname “Le God”3 before leaving the sport to become a sports commentator, most recently with Sky Sports.

As he describes in the interview, he lost that job for speaking out and bringing attention to the large number of unexplained sudden cardiac deaths happening to professional and amateur athletes around the world.

Athletes Are Dying on the Field in Large Numbers

Red Voice Media asks in a headline, “400 Athletes Collapsing & Dying Just in the Last 6 Months?”4then mentions “small stories coming out about perfectly healthy athletes mysteriously dying.” During the interview, Le Tissier is asked about his thoughts on the surge of cardiac events in the sporting world, to which he responds:5

“I’ve never seen anything like it. I played for 17 years. I don’t think I saw one person in 17 years have to come off the football pitch with breathing difficulties, clutching their heart, heart problems …

The last year, it’s just been unbelievable how many people, not just footballers but sports people in general, tennis players, cricketers, basketball players, just how many are just keeling over. And at some point, surely you have to say this isn’t right, this needs to be investigated.”

Le Tissier acknowledges there may be other factors that have caused this massive rise in cardiac events in athletes. He mentions that the athletes may have had COVID, and this could be a consequence of the illness, or it could be the vaccine. But the point he makes is that it should be investigated and it’s not.

This may cause you to wonder why health experts are not placing blame on the infection, but are in fact ignoring the issue completely. It begs the question: Do they already know the answer?

Le Tissier goes on to talk about player safety and how the sport protects the players from playing too long or too many games, yet they are watching players collapse on the field and apparently are content acting as if this is normal. He calls it a “massive dereliction of duty” that no one in a position of power is calling for an investigation.6

“It’s absolutely disgusting that they can sit there and do nothing about the increase in the amount of sports people who are collapsing on the field of play. And it’s not just what I’ve noticed this season as well. Again, in my career, I don’t remember a single game being halted because of an emergency in the crowd, a medical emergency in the crowd …

I would like somebody to look into that and go well, hang on a minute, can we go back for the last 15 or 20 years and … have a look and see how many times it happened 10 years ago and then how many times it happened in the last year. I’ve been watching a lot of sports and a lot of reports on football, and I’ve never seen anything like it, the amount of games that have been interrupted because of emergencies in the crowd.”

The interviewer pointed out that correlation does not necessarily mean causation, to which Le Tissier agreed, but stressed that an investigation is required to find out if it does. “To my naked eye, this is happening a lot more than it has in the past. I can’t be the only one who is seeing this.”7

Who Are These Athletes?

While an overwhelming number of professional and amateur athletes have collapsed on the field, they are not just numbers. They all have a high probability of having one thing in common — they took the COVID shot. This four-minute video features a compilation of athletes who “suddenly” collapsed within a six-month period.

Kyle Warner is one of those athletes.8 He’s 29 years old and at the peak of his career as a professional mountain bike racer. After getting a second dose of Pfizer’s mRNA jab in June 2021, he suffered a reaction so severe that by October he was still spending many of his days in bed.

In an effort to get the word out that COVID-19 shots are not always as safe as you have been led to believe, Warner shared his experience with retired nurse educator John Campbell in November 2021. Warner, in his 20s and in peak physical condition, was still severely harmed by the shot.

“I believe where there is risk, there needs to be choice,” he says.9 But right now, people are being misled. “People are being coerced into making a decision based on lack of information versus being convinced of a decision based on total information transparency.”10

Warner’s story is not unlike many others’: As Campbell learned in this interview, many doctors are unwilling to acknowledge that the COVID-19 shots might be related to patients’ injury complaints. While health officials have begun to acknowledge that myocarditis may be related to the injections, they continue to ignore other adverse events.

Vaccine Injured Unlikely to Get Help

Fact-checkers are quick to negate the possibility that an overwhelming number of deaths and injuries in professional and amateur athletes is not related to the COVID shots,11 but embalmers are telling12 a different story.

Funeral director Richard Hirschman has been a professional, board-certified embalmer since 2004 and currently travels to several funeral homes to embalm bodies. He appeared on the “Dr. Jane Ruby” show to share some shocking findings he’s been seeing in his work the past few months.13

In mid-2021, he began noticing some individuals who died of heart attacks and strokes had strange clots in their veins and arteries. He showed images of fibrous-looking clots he’d pulled out of the patients’ bodies, some of which are the length of a person’s leg, and explained that normal clots usually fall apart when handled. These fibrous clots — which he said he’s seeing more and more of — maintain their integrity and can be manipulated without disintegrating.

Massive Fraud in Reporting Vaccine Injuries; Withheld Data, Pretense of “Safe and Effective”

Unfortunately, whether they die or not, when it comes to getting help for someone who believes they’re injured by the COVID shots, it’s unlikely that they get it without intensive efforts. One reason is because, while people are increasingly calling for support for the vaccine-injured, the only way to get recompense is through the obscure Countermeasures Injury Compensation Program (CICP).14

To give a little background, injury claims for regular vaccines go through the National Vaccine Injury Compensation Program (NVICP).

Initially set up as a “no-fault” system to resolve injury claims, this U.S. law ultimately protects drug companies with a complete liability shield, and if you win through this vaccine “court,” payouts come from a special fund set up just for that purpose, sparing vaccine makers, their insurance companies and vaccine providers from costly payouts for vaccine injuries and deaths.15

However, if you believe you’ve been injured by a COVID shot, and you want compensation for it, you have to go through a different vaccine “court” run by what Fortune describes as an “obscure office within the U.S. Health and Human Services Department.” And, this system not only protects manufacturers and health care providers from liability, but has hoops to jump through and limits to it that make compensation much more difficult than going through the NVICP.

The bottom line is, even if you can prove you were injured by a COVID shot, you can’t sue the drug company and the compensation you receive from the program is capped at $50,000 for lost wages and $370,376 for wrongful death.16

Officials Try to Discredit VAERS

The law that protects Big Pharma from regular vaccine injury claims is the 1986 National Childhood Vaccine Injury Act.17 The CICP claim process for COVID shots is conducted under the Public Readiness and Emergency Preparedness (PREP) Act, passed in 2005,18 which authorizes the government to take countermeasures against a public health emergency. The latest declaration under this Act was issued March 17, 2020, that provided:19

“… liability immunity to certain individuals and entities (Covered Persons) against any claim of loss caused by, arising out of, relating to, or resulting from the manufacture, distribution, administration, or use of medical countermeasures (Covered Countermeasures), except for claims involving “willful misconduct” as defined in the PREP Act.”

In other words, unless willful misconduct can be proven, any person covered by the act also has indemnity against claims from citizens. This is not limited to manufacturers and Big Pharma, but can also include government officials. The thing is, both claims systems are actually at the tail end of the process and don’t reflect all the possible injuries that might be occurring.

So how can you tell how many actual injuries may be occurring with a certain vaccine? That’s where another system kicks in: the National Vaccine Adverse Event Reporting System (VAERS).20 As I’ll explain later, anyone can make a report to VAERS, and it’s this key component that critics use to claim that VAERS can contain errors and even false claims.

While the system has a mechanism to help weed out false reports, top government officials, such as NIAID director Dr. Anthony Fauci and CDC director Dr. Rochelle Walensky, have attempted to discredit it. Most notably, this occurred during a Senate hearing when both individuals implied that if a person had been vaccinated and was then killed in a car accident, it’s possible it could be recorded in VAERS as a vaccine injury.21

It is important to note that the VAERS system is coadministered by the CDC and the FDA.22However, as David Martin, whose self-described work involves ethical engagement and stewardship of community and commons-based value interests,23 points out in an interview excerpt posted on Twitter:24,25

“The fact is, that as much as the CDC and the FDA try to hide behind what they reportedly say is an error in the VAERS database, the Vaccine Adverse Event Reporting System, what they don’t seem to realize is that by saying that there are errors they are violating the 1986 Act …

If you go back and read that [the ACT] what you’ll find is that manufacturers of vaccines are required to keep VAERS accurate. That’s actually a statutory requirement. So, if they are telling you that it is not accurate, they are admitting to violating the law.”
By law, VAERS26 is a mandatory reporting system for health care professionals. The system is not set up to analyze causation, but may be used as raw data for detecting unexpected adverse events that may indicate a safety signal.

In total, the system must be maintained by health care professionals and drug manufacturers as a statutory requirement for maintaining indemnity against vaccine injury. Martin points out:27

“And that’s the quid pro quo in getting the immunity. If VAERS is wrong, then the immunity is pierced because it’s the manufacturer’s legal responsibility to make sure VAERS is accurate.”

VAERS Is Overwhelmed With Reports

Anyone can make a report to VAERS — both patients and health professionals can use this system to report health concerns they suspect may be connected to any vaccine, including the COVID shots. But since the system is passive, whether the reports get filed depends entirely on each individual living up to that responsibility.

The reports must contain all hospital records and any other relevant medical information. Unfortunately, as Brittany Galvin, a young woman who says she was injured by a COVID shot, succinctly notes in a video,28 the system is not efficient, and the data may be woefully out of date. This has a significant impact on monitoring the effects of the COVID inoculation program since it’s possible what you see on any given day in the VAERS database isn’t anywhere near current.

Galvin has created several videos talking about the journey she’s been on trying to report her adverse events to VAERS. In a video posted in January 2022,29 she recorded her phone conversation with an investigator from VAERS to discuss why her report filed in late May 2021 had not yet been counted in the system.

In one conversation she learned that the process takes many steps through different departments. The first stop for the VAERS reports is in a department with only 50 employees.30 Once the package of information is completed by this department, it is sent to a team of nurses who read and review every page.

If the staff have any concerns or if they feel they need more information, the package will be sent back to the first department for further information gathering.31 Galvin expressed her concern that there were hundreds of thousands of people like her and just 50 VAERS employees trying to process these reports.32

“Meanwhile the whole government is trying to force everyone to get this thing. Lying to the people telling them that “no one has gotten GBS from it” but here I sit barely able to walk and my case isn’t going to be ‘technically’ reported because the CDC hasn’t investigated yet because the hospitals are dragging their feet … it’s like a revolving crazy door and all of us humans on this planet and in this country are being lied to, and it’s unfair.”

At the end of the conversation with the investigator, Galvin learned that while her report was filed in May 2021, it wasn’t assigned to someone at VAERS until September or November 2021.33 It could be many months before the CDC receives the report of her vaccine injuries that can be published.34

*

Note to readers: Please click the share buttons above or below. Follow us on Instagram, @globalresearch_crg. Forward this article to your email lists. Crosspost on your blog site, internet forums. etc.

Notes

1 Open VAERS, COVID-19 Data

2 YouTube, July 17, 2019

3 The Desert Review, February 7, 2022

4 Red Voice Media, January 14, 2022

5 Rumble, February 1, 2022, Minute 23:30 – 24:35

6 Rumble, February 1, 2022, Minute 25:25 & 26:38

7 Rumble, February 1, 2022, Minute 27:25

8 YouTube, Dr. John Campbell, Kyle’s Vaccine Complication October 21, 2021

9 YouTube, Dr. John Campbell, Kyle’s Vaccine Complication October 21, 2021, 1:01

10 YouTube, Dr. John Campbell, Kyle’s Vaccine Complication October 21, 2021, 41:51

11 Reuters, November 29, 2021

12 Rumble, January 26, 2022

13 Rumble, January 26, 2022, 00:48

14 Fortune, May 3, 2021

15 Health Resources & Services Administration January 2020

16 Congressional Research Service, October 20, 2021

17 Public Law 99-660

18 Health and Human Services, Public Readiness and Emergency Preparedness Act

19 Federal Register, March 17, 2020

20 Vaccine Adverse Event Reporting System

21 YouTube, January 11, 2022, Min 2:49:30

22, 26 VAERS, About

23 About David Martin

24 Twitter, January 5, 2022, Min 00:27

25 Public Law 99-660  Title XXI. Subtitle 1, Sec. 2102(a)(3)

27 Twitter, January 5, 2022, Min 1:40

28 BitChute, December 18, 2021

29 Odysee, January 20, 2022

30 Odysee, January 20, 2022, Min 6:40 & 7:50

31 Odysee, January 20, 2022, Min 12:50

32, 34 Odysee, January 20, 2022, Minute 19:30

33 Odysee, January 20, 2022, Minute 20:45