COVID Injections Causing Miscarriages, Cancer and Neurological Disorders Among Military, DOD Data Show. Attorney Presented Info to Senate Committee. Govt Has Suppressed Data Since at Least 9/21

From [CHD] Attorney Thomas Renz on Monday told a panel of experts that data provided to him by three whistleblowers show COVID-19 vaccines are causing catastrophic harm to members of the U.S. military while not preventing them from getting the virus.

Following Monday’s panel discussion on COVID vaccines and treatment protocols, led by Sen. Ron Johnson (R-Wis.), Renz summarized data obtained from the Defense Medical Epidemiology Database (DMED), the military’s longstanding epidemiological database of service members.

The data show:

  • Miscarriages increased 300% in 2021 over the previous five-year average.

  • Cancer increased 300% in 2021 over the previous five-year average.

  • Neurological disorders increased 1000% in 2021 over the past five-year average, increasing from 82,000 to 863,000 in one year.

The whistleblowers provided the data knowing they would face perjury charges if they submitted false statements to the court in legal cases pending against the U.S. Department of Defense (DOD).

Renz told the panel a “trifecta of data” from the DMED, the DOD’s military-civilian integrated health database, Project SALUS, along with human intelligence in the form of doctor-whistleblowers suggest the DOD and the Centers for Disease Control (CDC) and Prevention have withheld COVID vaccine surveillance data since September 2021.

“Our soldiers are being experimented on, injured and sometimes possibly killed,” Renz said.

Following Renz’s presentation, attorney Leigh Dundas reported evidence of the DOD doctoring data in DMED to conceal cases of myocarditis in service members vaccinated for COVID.

The military whistleblowers reported a DMED search of “acute myocarditis” resulted in 1,239 cases in August 2021, but the same search in January 2022 resulted in only 307 cases.

Cardiologist Dr. Peter McCollough, commenting on Renz’s presentation, told the panel myocarditis is being falsely described as mild and transient when in reality it causes permanent heart damage and is life-limiting in most cases.

The military did not take any safeguards for the most at-risk age group for vaccine-induced myocarditis — 18- to 24-year-olds.

Renz also highlighted a broader data set from Project SALUS, run by the DOD in cooperation with the Joint Artificial Intelligence Center (JAIC), which sends weekly reports to the CDC.

Project SALUS analyzed data on 5.6 million Medicare beneficiaries aged 65 or older. Data were aggregated from Humetrix, a real-time data and analytics platform that tracks healthcare outcomes.

According to Renz, the Project SALUS data as of late last year show:

“71% of new cases are in the fully vaccinated, and 60% of hospitalizations are in the fully vaccinated. This is corruption at the highest level. We need investigations. The Secretary of Defense needs investigated. The CDC needs investigated.”

The Humetrix presentation summarizing the data in Project SALUS, “Effectiveness of mRNA COVID-19 vaccines against the Delta variant among 5.6M Medicare beneficiaries 65 years and older” (Sep. 28, 2021) has not been made public.

The Project SALUS report also included data on natural immunity, stating the vaccines have waning protection. The data also showed an upward trend of breakthrough cases suggesting booster shots could contribute to prolonging the pandemic.

“Breakthrough infection rates 5 to 6 months post-vaccination are twice as high as 3-4 months post-vaccination,” the report said.

According to the Humetrix overview of the Project SALUS data, Congress must investigate vaccine failure, along with increased risk reported for breakthrough cases (or vaccine failure) in North American Natives, Hispanics, Blacks, and males.

People with kidney disease, liver disease, heart disease and cancer treatment, along with people over age 75 are the most likely to experience breakthrough cases, while medical authorities advocate vaccines to these same populations to allegedly “protect the vulnerable.”

Project Salus reported the vaccines were only 41% effective. This low level of infection prevention needs to be analyzed against the counterweight of a threefold to tenfold increase in chronic disease signaled in DMED.

The U.S. Food and Drug Administration (FDA) requires only two adequate and controlled studies to approve a biologic, even if those studies are industry-sponsored.

The FDA now has data from the entirety of 3 million people employed by the DOD and 5 million people in Medicare. This data serves as independent substantiation that scientific fraud has occurred.

Based on this data, the FDA must revoke the Emergency Use Authorization for the Moderna, Pfizer and Johnson & Johnson COVID vaccines, and the Biologics License Application for Pfizer’s Comirnaty vaccine.

It would be wrong for the FDA to extrapolate the industry’s clinical trial data to pediatrics without halting the use of the vaccines and conducting an investigation based on this real-world data.

Ivermectin Reduces COVID Deaths 62% to 91%, Why Did Uncle Brother Demonize It? The Scientific Misconduct Story

STORY AT-A-GLANCE 

  • In mid-February 2021, Dr. Andrew Hill at Liverpool University published a scientific meta-analysis of six randomized controlled trials involving the use of ivermectin. The review, funded by the World Health Organization and UNITAID, found the drug increased viral clearance and reduced COVID-19 deaths by 75%, yet the conclusion of the paper was dismissive

  • In early April 2021, Hill was accused of scientific misconduct by the French civic group, Association BonSens. BonSens claims Hill manipulated data to downplay the usefulness of ivermectin. Hill admitted that the study sponsor had crafted the conclusion

  • In early August 2021, Hill published a public notice stating one of the six studies included in his analysis had been withdrawn due to fraudulent data. A revised analysis excluding that study was published in November 2021

  • In the November revision, Hill included 23 randomized clinical trials, concluding ivermectin had no statistically significant effect on survival or hospitalizations

  • Other meta-analyses of 13 to 24 studies have found reductions in death ranging from 62% to 91%. Recent research has also found a five-day course of ivermectin at a dose of 12 mg per day sped up viral clearance, reducing the duration of symptomatic illness by three days compared to placebo (9.7 days versus 12.7 days)

From [MERCOLA PDF]In mid-February 2021, Dr. Andrew Hill at Liverpool University published a scientific meta-analysis of six randomized controlled trials involving the use of ivermectin in 1,255 COVID-19 patients. (The paper was initially posted on a preprint server.)

The review, which was funded by the World Health Organization and UNITAID, found that ivermectin increased viral clearance and reduced COVID-19 deaths by 75%. This is a rather massive benefit, yet the conclusion of the paper was dismissive, saying additional large clinical trials were needed to make a determination about whether or not to recommend its use.

Hill Accused of Scientific Misconduct

In early April 2021, Hill and his coauthors were accused of scientific misconduct by a French civic group called the Association BonSens. The TrialSite News video report from April 5 above reviews the details of this story. BonSens — labeled by some a “controversial group” based on its anti-mask mandate stance — accused Hill of data manipulation to downplay the usefulness of ivermectin.

According to BonSens, Hill’s analysis was then used by the WHO to recommend against ivermectin, even though it appears to have significant benefit. BonSens called on Hill to retract the paper, but Hill remained “resolute and stands behind the study,” TrialSite News said.

At the time, TrialSite News claimed to have been in conversation with “relevant and associated parties,” some of whom have asked to remain anonymous, who say Hill’s study was in fact modified, but that this was done “separate and apart from the investigator,” and that Hill had no say in the matter.

However, since then, one of the six studies Hill included in his analysis has been withdrawn “due to fraudulent data.” In a public notice1 dated August 9, 2021, Hill and his coauthors addressed the matter, saying they would submit “a revised version excluding this study, and the currently posted paper will be retracted.” A revised and updated meta-analysis was published in November 2021.2

The updated review includes data from 23 randomized clinical trials with a total of 3,349 patients. Studies with “high risk of bias” were excluded. In this analysis, Hill found that “Ivermectin did not show a statistically significant effect on survival or hospitalizations,” and had only “borderline significant effect on duration of hospitalization in comparison with standard of care.”

No significant effect on clinical recovery time was detected. In conclusion, the paper states that the WHO “recommends the use of ivermectin only inside clinical trials.” Curiously, it also states that “a network of large clinical trials is in progress to validate the results seen to date.” What results might those be? Surely, they must be referring to positive results, or else a network of clinical trials would hardly be justified.

Positive Ivermectin Studies Largely Barred From Publication

December 3, 2021, TrialSite News interviewed Dr. Tess Lawrie (above) about her own ivermectin analyses and that of Hill. She points out that she was concerned when she saw the initial meta-analysis Hill published, as the conclusion didn’t match the data. The reduction in death was significant, yet the conclusion was dismissive.

Lawrie contacted Hill, asking him to explain his conclusion to her. He then told her that the conclusion of the paper was not his own. It had been written by his sponsor — the WHO. Lawrie was shocked, she said, as this struck her as a clear conflict of interest.

In the interview, Lawrie also discusses the general difficulty researchers have had, since the beginning, in getting papers published that support ivermectin. She admits her own team has downplayed the benefits by using extremely conservative analyses in an effort to get published.

“It seems, if you tell it like it is, you are not going to get published because you might be accused of overstating your case. And if you understate it, you’re told there’s not enough evidence,” Lawrie says.

Strong Evidence for Ivermectin

According to Lawrie, the evidence for ivermectin in the treatment of COVID-19 is strong. In a previous interview, she reviewed a 13-study meta-analysis that found a 68% reduction in deaths. A follow-up review that included 15 studies found a 62% to 72% reduction in deaths.3

A five-day course of ivermectin at a dose of 12 mg per day sped up viral clearance, reducing the duration of symptomatic illness by three days compared to placebo (9.7 days versus 12.7 days).

A meta-analysis4 by Lawrie and her team published in the July-August 2021 issue of the American Journal of Therapeutics, which included 24 randomized controlled trials with a total of 3,406 participants, reported reductions in death ranging between 79% and 91%.

A study published February 2021 also reported that a five-day course of ivermectin at a dose of 12 mg per day sped up viral clearance, reducing the duration of symptomatic illness by three days compared to placebo (9.7 days versus 12.7 days).5

According to Lawrie, what makes ivermectin particularly useful in COVID-19 is that it works both in the initial viral phase of the illness, when antivirals are required, and in the later inflammatory stage, when the viral load drops off and anti-inflammatories become necessary.

Dr. Surya Kant, a medical doctor in India who has written a white paper6 on ivermectin, claims the drug reduces replication of the SARS-CoV-2 virus by several thousand times.7 Kant’s paper led several Indian provinces to start using ivermectin, both as a prophylactic and as treatment for COVID-19 in the summer of 2020.8

Africa and Japan Defy the Odds With Ivermectin

Japan and Africa have also defied the odds with ivermectin. As reported by NewsRescue at the end of August 2021, “Melinda Gates, co-chair of the Bill and Melinda Gates foundation predicted disaster in the developing world, but so far she has been dead wrong, at least as far as Africa is concerned.”9

Indeed, despite having nearly 1.4 billion people, Africa has maintained one of the lowest COVID caseloads and death rates in the world, accounting for just 4% of the global reported death rate as of mid-May 2021.10 While media feign confusion, ivermectin may well be the explanation for this phenomenon.

A study11 published at the end of December 2020 found that African countries that participated in the African Program for Onchocerciasis Control (APOC), where intensive ivermectin mass campaigns were carried out between 1995 and 2015, had 28% lower COVID-19 mortality and 8% lower infection rates than non-APOC countries that did not participate in the ivermectin campaign.

“That a mass public health preventive campaign against COVID-19 may have taken place, inadvertently, in some African countries with massive community ivermectin use is an attractive hypothesis,” the authors said.12

Similarly, Japan has seen a massive decline in cases after adopting ivermectin as standard treatment against COVID. November 3, 2021, Free West Media reported:13

“The head of the Tokyo Medical Association appeared on national television in September urging doctors to use Ivermectin and they listened. A little over a month later, COVID-19 is under control in Japan ...

Japan had slavishly adhered to all the Big Pharma prescriptions, including quarantine, contact tracing, masking, social distance, but finally the pandemic had hit them hard after they started aggressive vaccination in May 2021.

The results looked good initially, but in mid-July they started rising again and on August 6 cases hit a new all-time high and continued to rise.

Ivermectin was allowed as a treatment on August 13 and after 2 weeks the cases started to come down. In fact, they are now down 99% from the peak ... In Japan, doctors can now prescribe it without restrictions, and people can buy it legally from India.”

Doctors Urge Acceptance of Ivermectin to Save Lives

In the U.S., the Frontline COVID-19 Critical Care Alliance (FLCCC) has been calling for widespread adoption of ivermectin, both as a prophylactic and for the treatment of all phases of COVID-19.14,15

FLCCC president Dr. Pierre Kory, former professor of medicine at St. Luke’s Aurora Medical Center in Milwaukee, Wisconsin, has testified to the benefits of ivermectin before a number of COVID-19 panels, including the Senate Committee on Homeland Security and Governmental Affairs in December 2020,16 and the National Institutes of Health COVID-19 Treatment Guidelines Panel January 6, 2021.17 As noted by the FLCCC:18

“The data shows the ability of the drug Ivermectin to prevent COVID-19, to keep those with early symptoms from progressing to the hyper-inflammatory phase of the disease, and even to help critically ill patients recover.

Dr. Kory testified that Ivermectin is effectively a ‘miracle drug’ against COVID-19 and called upon the government’s medical authorities … to urgently review the latest data and then issue guidelines for physicians, nurse-practitioners, and physician assistants to prescribe Ivermectin for COVID-1919 …

… numerous clinical studies — including peer-reviewed randomized controlled trials — showed large magnitude benefits of Ivermectin in prophylaxis, early treatment and also in late-stage disease. Taken together … dozens of clinical trials that have now emerged from around the world are substantial enough to reliably assess clinical efficacy.”20

A one-page summary21 of the clinical trial evidence for Ivermectin can be downloaded from the FLCCC website. A more comprehensive, 31-page review22 of trials data has been published in the journal Frontiers of Pharmacology.

At the time of this writing, the number of trials involving ivermectin has risen to 71, including 31 randomized controlled trials. A listing of all the ivermectin trials done to date, with links to the published studies, can be found on c19Ivermectin.com.23

The FLCCC’s COVID-19 protocol was initially dubbed MATH+ (an acronym based on the key components of the treatment), but after several tweaks and updates, the prophylaxis and early outpatient treatment protocol is now known as I-MASK+24 while the hospital treatment has been renamed I-MATH+,25 due to the addition of ivermectin.

The two protocols26,27 are available for download on the FLCCC Alliance website in multiple languages.

Take Control of Your Health Care

If COVID-19 were an actual medical crisis and not an excuse for a tyrannical power grab, doctors would have been allowed, indeed encouraged, to work together to find solutions. Their successes would then have been announced everywhere. Without doubt, ivermectin would have featured heavily in such reports, as doctors around the world have attested to its benefits.

That’s not what happened, though, which tells us we’re not dealing with a medical crisis that governments actually want to solve. As reported by the FLCCC, its members have “been blocked in attempts to disseminate scientific information about ivermectin on Facebook and other social media with the FLCCC’s pages repeatedly being shut down.”28

Seasoned researchers like Lawrie can’t get their research published, and the main thing they have in common is that they’re reporting positive results using ivermectin (and other common remedies). For nearly two years now, doctors and scientist have repeatedly shown we can control the COVID endemic, even with new variants. We can save the vast majority from severe illness and death.

Yet “authorities” within government, regulatory agencies and health agencies have refused to listen and insist there’s only one way forward — we need novel gene transfer injections that direct our cells to churn out the very toxin that makes COVID-19 so problematic. And when those shots are proven failures, the answer, these same “leaders” say, is more boosters!

Insanity is doing the same thing over and over, expecting different results. The good news is you can choose who you listen to. You can listen to frontline medical experts, like the FLCCC, and follow their advice.

1 Open Forum Infectious Diseases August 9, 2021; 8(8): ofab394

More Than Half of COVID Patients in Hospitals in England are Being Treated For Something Else

SLIDE IS FROM STEVE KIRSCH, '“VACCINE ESSENTIALS”

From [HERE] New figures show that over half of ‘COVID patients’ in hospitals in England are primarily being treated for something else.

Official statistics count 13,023 patients with COVID on Tuesday, but 6,767 were not being treated principally for the virus.

That means 52 per cent of hospital patients being considered to be ‘COVID patients’ aren’t actually COVID patients at all.

In London, the number is even higer, with 64 per cent of ‘COVID’ patients in hospital for a different reason.

Back in September, the number of patients who were being counted as COVID patients despite being treated for something else stood at around 23 per cent, meaning the figure has risen by 29 per cent in four months.

“The growing proportion of patients who are in hospital “with” COVID rather than “for” it is another sign that the current wave of the virus has not led to the same sort of pressure on critical care as in previous waves,” reports Sky News.

As we previously highlighted, a significant number of these COVID patients also only caught COVID after entering hospital for a different ailment.

Figures from December showed that 65% of people described as ‘COVID patients’ only tested positive for COVID after being admitted to hospital for something else.

The issue of whether official hospital patient numbers and death tolls should differentiate between ‘with COVID’ and ‘by COVID’ has been hotly debated for many months.

By artificially inflating numbers by counting people who are in hospital for something else, technocrats and lockdown lobbyists in the media have more ammunition to demand more restrictive lockdown policies.

Transparency? The Government is Destroying Informed Consent to Take Experimental Injections: FDA Requests Court to Delay First 55,000 Page Production and Pfizer Moves to Intervene in the Suit

Attorney Aaron Siri states, As explained in prior posts, in a lawsuit seeking all of the documents the FDA relied upon to license Pfizer’s COVID-19 vaccine, a federal judge shot down the FDA’s requested rate of 500 pages per month and instead ordered the FDA to produce at the rate of 55,000 pages per month starting on March 1. 

Since the government has trillions of dollars of our money, it is putting it to good use by fighting to assure that the public has the least amount of transparency possible.  To that end, it has now asked the Court to make the public wait until May for it to start producing 55,000 pages per month and, even then, claims it may not be able to meet this rate. 

The FDA’s excuse?  As explained in the brief opposing the FDA’s request, the FDA’s defense effectively amounts to claiming that the 11 document reviewers it has already assigned and the 17 additional reviewers being onboarded are only capable of reading at the speed of preschoolers. 

Meanwhile…

As the FDA tries to obtain months of delay, guess who just showed upon in the lawsuit?  Yep, Pfizer.  And it is represented by a global chair and team from a law firm with thousands of lawyers.  Pfizer’s legal bill will likely be multiple times what it would cost the FDA to simply hire a private document review company to review, redact, and produce the documents at issue.  Within weeks, if not days.

Pfizer is coming in as a third party.  But Pfizer assures the Court it is here to help expedite production of the documents.  Sure it is!  Where was Pfizer before the Court ordered the 55,000 pages per month?  Right, doing what it normally does: letting the government work on its behalf – like the way the government mandates, promotes, and defends Pfizer’s product.  

But the government did not please Pfizer this time and so here it comes, likely looking for a second bite at the apple.  Of course the FDA consented to Pfizer appearing.  You can read the response my firm filed to Pfizer’s motion , as well as all of the other relevant recent filings in the link provided below.  

Let me end by noting that all of this insanity is simply in response to an attempt to obtain some basic transparency.  This should again bring into sharp focus why the government should never coerce or mandate anyone to get an unwanted medical product or procedure.  Just look at this circus – the government mandates Pfizer’s product, gives it immunity for any safety or efficacy issues, promotes its product using taxpayer money, gives Pfizer over $17 billion and then uses taxpayers’ money to fight to avoid providing even the most basic level of transparency to the public.

The introduction from the brief opposing the FDA’s request is below and you can find copies of all the relevant court filings (FDA Motion to Modify Scheduling Order, January 18, 2022 / Plaintiff Opposition to Motion to Modify, January 24, 2022 / Pfizer Motion to Intervene, January 21, 2022 / FDA Response to Pfizer Motion, January 25, 2022 / Plaintiff Response to Pfizer Motion, January 25, 2022) here:

Israel Leads the World in “COVID Cases" per capita. Highly Vaccinated Adult Population is More Susceptible to Infection Due to Mandatory, Harmful Injections in Fascist Nation Disguised as a Democracy

From [NN] Despite the fact that Israel has implemented some of the most draconian COVID-19 pandemic measures in the world, the country is now number one in the world in new cases, according to local reports.

According to the Times of Israel, a leading health expert in the country said that 0.6 percent of the population was testing positive daily for the virus — most likely the latest variant, omicron, which is highly contagious but also very mild.

Prof. Eran Segal of The Weizmann Institute said at that rate, Israel currently leads the world in per capita infection rates, even though the population is required to get the latest version of vaccines available and despite heavy quarantine and lockdown regimes.

However, Segal tried to excuse the high infection rate:

But Segal noted it was likely that Israel was not truly the country with the highest infection rate. Rather, he attributed the figures to Israel being a leading country in the number of tests performed each day, relative to its population size.

Israel is followed in the highest daily cases worldwide ranking by Mongolia, Peru, Canada and Georgia.

The fact is, either you’re the number one country, per capita, in daily infections — or you’re not. And right now, Israel is No. 1, period, no matter how you look at the data.

But instead of realizing that this novel coronavirus is not the world-ender that the world has been propagandized to believe, Israeli Prime Minister Naftali Bennett is quadrupling down on idiot policies that have not worked yet and are never going to work (because viruses virus — that’s what they do and nothing humans do will stop them from spreading).

The PM “announced Thursday that mandatory quarantine for schoolchildren who were exposed to coronavirus carriers would be scrapped entirely,” the Times of Israel reported. “According to the plan, starting next Thursday, children up to the age of 18 will no longer need to isolate after being exposed.

“Instead, all students — both vaccinated and unvaccinated — will need to conduct two antigen tests a week — on Sundays and Wednesdays — and present negative results when entering educational institutions,” the outlet continued. “Children who test positive for COVID-19 will still need to isolate until testing negative.”

Bennett said that the government will begin distributing “millions” of test kits so that testing can be done at home, an endeavor that is costing tens of millions of dollars to carry out.

Bennett’s order comes as 146,000 school-aged children were already in quarantine due to testing positive for the virus, while another 142,000 were forced into quarantine because they had been ‘exposed’ to the virus (which means nothing considering the virus is literally everywhere).

“Wherever we can make it easier for the public, we will. We are taking Omicron seriously, but also looking at the bigger picture,” Health Minister Nitzan Horowitz said.

Education Minister Yifat Shasha-Biton called Bennett’s order “a brave decision,” while noting further that “it would have been easier to close the education system, but our duty is to save every boy and girl” from the damage of repeated quarantines — even while ordering them into repeated quarantines.

After NY Ct Stays Order Striking Down Mask Mandate Black Probot Parrots Doggy's Dogma: "Masks Save Lives" and “Stop the spread of COVID.” No Study Proves Masks Stop COVID. They Create Fear/Harm Health

The Scientific evidence suggests face masks as worn by the general public do not work. Government health authorities around the world said in 2020 face masks as worn by the general public do not work.  They are telling you to wear them because it creates fear and it keeps the threat of a virus in everyone's mind.  To the contrary, the data support the opposite. That is, masks suppress the immune system, render the mist vulnerable to infection, and amplify more viruses in the compromised who become victims and further spread the disease among family and close contacts” - Dr. Judy Mikovits. [MORE]

'Asymptomatic People Don't Spread COVID. You're Being Lied to. Healthy Persons Spreading COVID is Epidemiologically Irrelevant. So There's No Need for Mandates, Testing, Masks or Shut-Downs.'- Yeadon

From [HERE] New York Attorney General Letitia James Tuesday pushed back against opposition to the New York Department of Health’s (DOH) mask mandate. Robert J. Miller, New York Supreme Court Appellate Judge, stayed a January 24, 2022, ruling by fellow appellate judge Thomas Rademarker which voided 10 NYCRR § §2.60; 2.60(a).

Commissioner of Health for the State of New York, Mary T. Basset, M.D. enacted 10 NYCRR § §2.60; 2.60(a) on December 10, 2021. The rule requires all residents of New York to wear a mask if they are over two years of age and are able to “medically tolerate” masks.

Administrative agencies have powers to promulgate regulations, but only the legislature retains the power to pass laws. Administrative regulations are intended to implement statutes (laws) created by the legislature. For any statute that an agency has been authorized to implement, carry out or otherwise enforce, complementary regulations may be issued by the agency to do so. That is, the statute is like a parent and a regulation is the child. Any regulation that conflicts with a statute is void. Agencies have discretion to create regulations but they must be tied to some statute. An administrative agency, an unelected body of public officials, is a creature of statute and may not act in excess of its statutory authority. Therefore, regulations they enact pursuant to that statutorily provided authority cannot expand that authority." In contrast, laws are made by elected government representatives in the legislative branch of state or federal government. Governments often circumvent the legislative process, which must involve the public (through the use of elected legislative representatives who hold public hearings, debates and make legislative findings subject to public review and participation) by having an agency create a regulation (subject to much less public input and participation and no direct accountability (unelected)). Furthermore, this abbreviated administrative process with less public scrutiny may be all-together eliminated if the agency determines there is an “emergency” imminently harming the public. Under such circumstance, as here, an agency may declare an emergency and immediately issue regulations which expire at a fixed date.

As explained by law professor Babette E.L. Boliek

Every dictatorship, it seems, begins with some sort of claim of crisis or emergency.” There is a balance that must be struck, even in time of emergency, between regulatory efficiency and the procedural safeguards created to protect representative government, curb agency overreach, and promote agency transparency.

In the present case, Judge Rademarker ruled that the regulation is actually a law and was “enacted unlawfully by an Executive branch state agency, and [is] therefore void and unenforceable as a matter of law.”

NEVER TRUST A BLACK PROBOT, EVER. HER BUSINESS IS PROCESS. ACCORDING TO FUNKTIONARY, A PROBOT IS A PROPAGANDIZING PROGRAMMED ROBOT. A PROBOT IS A PROXYMORON WHO CONVEYS PROGRAMMED DISINFORMATION IN COMPUTERIZED LANGUAGE AND BUREAUCRATESE JARGON. A PROBOT IS ONE WHO DISSEMINATES LIES, DISTORTIONS AND CONVENIENT MASS TRUTHS COMPOSED BY A SUPERIOR OVERRULING ELITE. [MORE] THEY FUNCTION WITH AN EXTREMELY LOW LEVEL OF CONSCIOUSNESS AS THEY VIEW OBEDIENCE TO AUTHORITY AS A MORAL VIRTUE AND PLACE FORM OVER SUBSTANCE, RULES OVER REASON AND LAW OVER HUMANITY. A BLACK PROBOT IS CAPABLE OF ADVOCATING FOR WIDESPREAD AGGRESSION AND DESTRUCTION IF THE RULES SAY SO. ELITES PUT THEM ON THE FRONT LINES.

James released a statement after Miller’s ruling, saying:

Nearly three years into the COVID-19 pandemic, we know that wearing a mask saves lives. This mandate and today’s decision are critical in helping to stop the spread of this virus and protect individuals young and old. We will continue to do everything in our power to prioritize the health and wellbeing of all New Yorkers.

According to the probot, the mask mandate will now remain effective until further action by the appellate court.

The Blight House has Withdrawn its Mandate Forcing Workers at Companies to Get Deadly, Experimental COVID Injections which Don't Stop the Spread or Prevent COVID but are Immune from All Liability

From [HERE] and [CHD] The Biden administration has officially withdrawn a rule that would have required workers at big companies to get vaccinated or face regular COVID testing requirements.

The Occupational Safety and Health Administration confirmed the withdrawal Tuesday. But the agency said it still strongly encourages workers to get vaccinated.

In early November, OSHA announced a vaccine-or-test mandate for companies with at least 100 employees. The rule — which would have impacted more than 80 million U.S. workers — was originally set to go into effect on Jan. 4.

Mission accomplished though because the goal of Authorities was to get as many people to comply as possible before the mandate could be struck down by a court or withdrawn. Through intense coercion people complied with the mandate and every day the number of people injected increased. And still is increasing through other forms of coercion and purposeful media confusion about whether this mandate was withdrawn (it has been, thanks master). Importantly, many states and local governments have their own mandates which were enacted by Governors or Mayors on an emergency basis in order to circumvent the legislative process (which usually requires public involvement, debate, hearings and findings conducted by elected representatives).

In pulling the rule, the department said it recognized the Emergency Temporary Standard (ETS) could not be revived after the U.S. Supreme Court blocked it earlier this month.

Instead, the Biden administration is working to set a permanent standard for the vaccine mandate based on the Supreme Court’s ruling, according to a notice provided to the court by the Occupational Safety and Health Administration (OSHA).

OSHA said in a press release:

“Although OSHA is withdrawing the vaccination and testing ETS as an enforceable emergency temporary standard, the agency is not withdrawing the ETS as a proposed rule. The agency is prioritizing its resources to focus on finalizing a permanent COVID-19 Healthcare Standard.”

OSHA could move a version of the vaccine-or-test rule through its rule-making process, but would still likely face legal challenges, according to David Michaels, a former OSHA administrator and professor at George Washington University.

The Labor Department’s decision to withdraw the rule means pending legal proceedings will be dropped. The case was on its way back to the 6th Circuit Court of Appeals to be heard on the merits, although the lower court most likely would have followed the Supreme Court’s lead, The New York Times reported.

Without OSHA’s vaccine mandate in effect, employers must follow state and local laws on COVID workplace safety. Some states have banned vaccine mandates for private employees, while other states, like New York, require them.

“OSHA continues to strongly encourage the vaccination of workers against the continuing dangers posed by Covid-19 in the workplace,” the Labor Department wrote in the notice of its withdrawal.

The Supreme Court on Jan. 13, rejected the Biden administration’s employer mandate.

The court’s conservative majority said the administration overstepped its authority by imposing OSHA’s vaccine-or-test rule.

The Supreme Court’s decision reversed the lower court ruling, imposing a stay on the OSHA mandate.

The conservative majority expressed concerns over the implications of allowing OSHA to implement a widespread mandate without congressional authorization.

“Permitting OSHA to regulate the hazards of daily life — simply because most Americans have jobs and face those same risks while on the clock — would significantly expand OSHA’s regulatory authority without clear congressional authorization,” the opinion stated.

Furthermore, the court said, Congress has “indisputably given OSHA the power to regulate occupational dangers,” but it “has not given that agency the power to regulate public health more broadly.”

“Requiring the vaccination of 84 million Americans, selected simply because they work for employers with more than 100 employees, certainly falls in the latter category,” the opinion read.

The minority justices said OSHA’s mandate is comparable to a fire or sanitation regulation imposed by the agency, while the majority said a vaccine mandate is strikingly unlike the workplace regulations that OSHA has typically imposed as a vaccination “cannot be undone at the end of the workday.”

A majority of the Supreme Court’s justices concluded the applicants challenging OSHA’s mandate were likely to succeed in the merits of their claim and the secretary of labor lacked authority to impose the mandate, resulting in a stay while the case works its way through the 6th Circuit Court.

After the ruling, many companies were left scrambling to decide whether they should abandon the mandate or force their employees to be vaccinated while the lawsuit played out in the lower courts.

Starbucks was one of the first major retailers to backtrack on its plans to require workers to be vaccinated against COVID. Starbucks last week told its 228,000 employees at more than 9,000 U.S. coffee shops it would no longer require workers be fully vaccinated or submit to weekly COVID testing.

In a Jan. 18 memo to employees, Starbuck CEO John Culver said the company respects the court’s ruling and will comply even though it doesn’t align with the company’s beliefs.

A coalition of attorneys general from 27 states called on OSHA to rescind its ETS saying the agency lacked authority to issue a broad mandate.

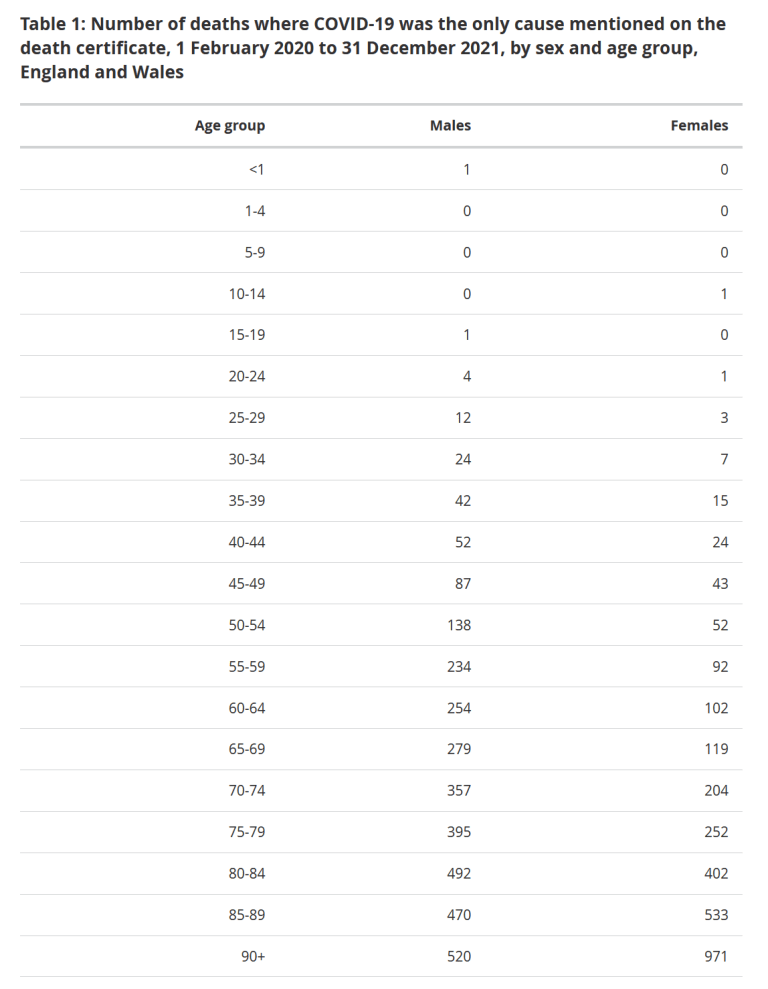
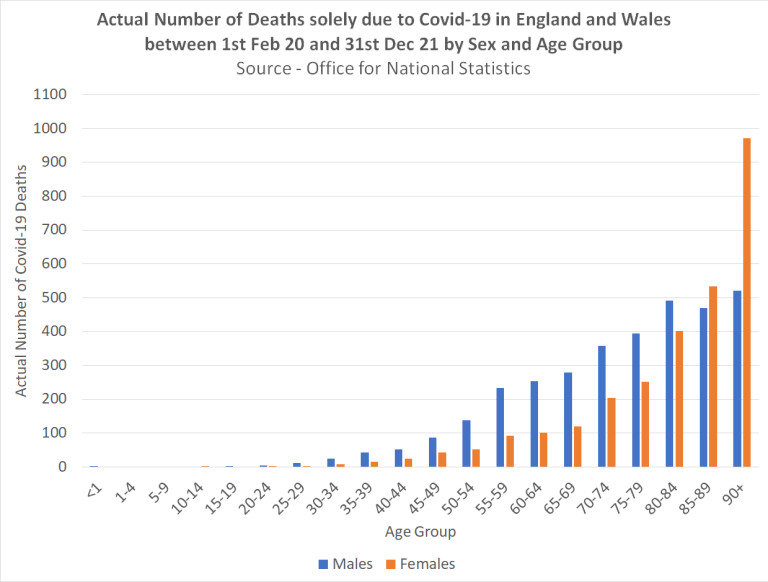
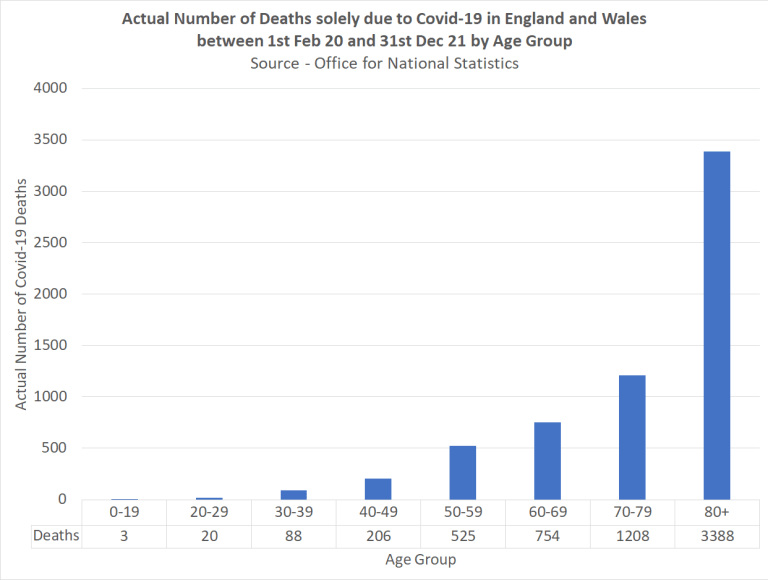
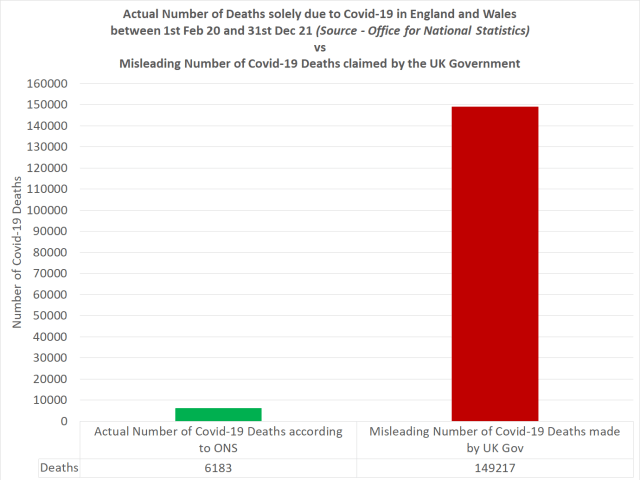
Where COVID is the Only Attributable Cause of Death, We See the Rate of Death is Remarkably Low. Freedom of Information Response Reveals that Governments and Media are Lying, Inflating COVID Deaths

Dr. John Campbell seems surprised at the Office for National Statistics Freedom of Information request about deaths from COVID-19 with no other underlying causes. [MORE]

13 March 2020 to 7 January 2022, England and Wales https://www.ons.gov.uk/peoplepopulati… 127,704 excess deaths above the five-year average Official data https://coronavirus.data.gov.uk/detai… Deaths from COVID-19 with no other underlying causes FOI Ref: FOI/2021/3240 https://www.ons.gov.uk/aboutus/transp… Death registrations for 2020 and 2021 for deaths where COVID-19 was listed as the underlying cause, but had no other pre-existing conditions recorded on the death certificate, England and Wales This publication will be updated quarterly 2020 Total deaths, 9,400 0-64, 1,549 65 and over, 7,851 2021 Q1 Total deaths, 6,483 0-64, 1,560 65 and over, 4,923 2021 Q2 Total deaths, 346 0-64, 153 65 and over, 193 2021 Q3, Total deaths, 1,142 0-64, 512 65 and over, 630 Therefore, 2020 and first 3 quarters of 2021 Total deaths from covid alone, 17,371 Of this number 13,597 were 65 or over Of this number, 3,774 were under 65 Average age of death in UK from covid in 2021 82.5 years Average life expectancy in the UK, 2018 to 2020 https://www.ons.gov.uk/peoplepopulati… 79.0 years for males 82.9 years for females This represents a fall of 7.0 weeks for males and a slight increase of 0.5 weeks for females (from the latest non-overlapping period of 2015 to 2017) This is the first time we have seen a decline when comparing non-overlapping time periods since the series began in the early 1980s As of end of September https://coronavirus.data.gov.uk/detai… Within 28 days of a positive test, 137,133 (7.9 times more deaths) Excess deaths from cancer https://www.youtube.com/watch?v=U90eD… Professor Karol Sikora, University of Buckingham Former head of cancer programme at WHO Probably an extra 50,000 deaths from cancer, over the past 18 months, you otherwise would not have had Failure to report early Difficulty getting to see GP Fear of hospital admissions Missed chemotherapy Missed radiotherapy 6 million waiting for NHS treatment



"The biggest scandal of this epidemic is that we have been made to believe these are vaccines. They are not vaccines at all." - Dr. Christian Perronne, Professor of Infectious and Tropical Diseases

From [HERE] On January 12, 2022, Prof. Christian Perronne participated in the public debates at the Parliamentary Hearing in Luxemburg. He called to suspend these experiment products that are not vaccines.

We have disregarded the science and infringed our rights. The biggest scandal of this epidemic is that we have been made to believe these are vaccines. They are not vaccines at all. Those in the parliament who voted for an experiment product mandate can be personally prosecuted in an international court.


Prof. Perronne’s main arguments:

  • All decisions lack scientific support. Policymakers who stipulated the vaccine policies have relied on “experts” with significant conflicts of interest and misled the public through the mainstream media (also with major conflicts of interest). While the pharmaceutical industry provides zero scientific references, the world’s “most prestigious” scientific journal, namely The Lancet, has published a fraudulent study to discredit chloroquine.

  • Alternative, effective treatment is available; therefore, it is illegal for the experiment product to be authorized for emergency use and, worse, imposed as a mandate.

  • The medical agencies did not evaluate these experimental products properly. There have been defined evaluations for years. It takes about ten years to authorize a standard vaccine and another ten years for the authorized use on pregnant women.

  • More children die from the experiment product than from COVID.

Christian Perronne, MD, PhD, is Professor of Infectious and Tropical Diseases at the University of Versailles-St Quentin, Paris-Saclay, France.

UK Data Shows Doctors are Among the Health Workers Least Likely to Get COVID Injection, while fitness instructors, artists and waiters have some of the highest unjabbed rates overall

From [HERE] Doctors are among the health workers least likely to be vaccinated against Covid-19, while fitness instructors, artists and waiters have some of the highest unjabbed rates overall.

New figures from the Office for National Statistics (ONS) show vaccination rates by profession at the end of last year. The data provides an early indication of which parts of the NHS and social care workforce could be hardest hit by the compulsory vaccination rule that comes into force in April.

Any health and care workers coming into direct contact with patients must have had a first dose by February 3 in order to meet the deadline. NHS employers have been told to begin dismissal proceedings against unvaccinated staff, including those who refuse to disclose their status, from February 4. [MORE]

Dr. Robert Malone: COVID Injections are permanently damaging children

From [NN] The inventor of the modern mRNA vaccine technology, Dr. Robert Malone, recently issued a stark warning to parents in the U.S. and all over the world about the dangers of getting their children vaccinated against the Wuhan coronavirus during a powerful speech at the Defeat the Mandates Rally in Washington D.C.

Malone said that those who are considering vaccinating their children against COVID can cause permanent harm, urging them to stay informed about the risks before making decisions.

He noted that as a parent, it is one’s responsibility to protect children. “If they’re harmed by these genetic vaccines, you are the one who will have to take care of them. And you will carry the burden for the rest of your life and theirs,” he said.

Further, he noted that on average, between one in 2,000 and 1 in 3,000 children that receive vaccines will be hospitalized in the short term with vaccine-caused damage. Only time can tell what long-term damage may happen to the children. (Related: Dr. Robert Malone tells Stew Peters about the life-threatening effects of COVID-19 vaccines – Brighteon.TV.)

He also went on to say that the vaccine does not protect children from the omicron variant, and they do not prevent infected children from infecting others. In contrast, big pharma companies and the government are almost fully protected from any damages that these products may cause them.

Malone said that genetic vaccines can damage children. “They may damage their brains, their heart, their immune system, and their ability to have children in the future. Many of these damages cannot be repaired,” he went on.

Malone speaks about the dangers of mRNA vaccines

Over 16,000 physicians and medical scientists around the world have already signed a declaration that said healthy children should not be vaccinated for COVID. In December 2021, Malone talked about this issue in a prepared speech, where he said he is standing by his statement with a career dedicated to vaccine research and development. “I’m vaccinated for COVID and I’m generally pro-vaccination. I have devoted my entire career to developing safe and effective ways to prevent and treat infectious diseases,” he said. (Related: Before your child is injected, watch Dr. Robert Malone’s statement on child COVID vaccinations.)

However, he put forward a warning about injecting children, which he said is an irreversible decision. Among the issues he pointed out included the following:

A viral gene will be injected into children’s cells. Malone noted that the gene will force children’s bodies to make toxic spike proteins that can cause permanent damage in their critical organs, including their brain and nervous system, their heart and blood vessels that make them prone to blood clots, their reproductive systems and trigger fundamental changes in their immune system.

What’s even more alarming is that once these damages have occurred, they become irreparable. The lesions in the brain cannot be fixed, and heart tissue scarring cannot ve repaired. The vaccine can also cause reproductive damage that could affect generations of the family.

The novel mRNA technology has not been adequately tested. Malone said that researchers and scientists need at least five years of testing and research before they can fully understand the risks, as harms from new medicines tend to be revealed many years later. Parents should rethink whether or not they want their own children to be part of the most radical medical experiment in humans today.

Children represent no danger to their parents or grandparents. The immunity of children after getting COVID is critical to saving families from the disease, so there is no benefit for children to get vaccinated against the small risk of the virus, considering the known health risks of the vaccine that parents and children have to live with for the rest of their lives.

British Data Shows COVID Injections are an Abysmal Failure, as COVID infection Rates in the U.K. are higher among the “fully vaccinated" in All Adult Cohorts

British data show the COVID shots are an abysmal failure, as COVID infection rates in the U.K. are higher among the “fully vaccinated” in all adult cohorts

  • Infection rates are also rising faster among the fully vaxxed than in unvaccinated cohorts of all ages. All in all, these data prove that vaccine passports and mandates are completely pointless

  • Data from Scotland show more of the same. Double-jabbed Scots are more likely to be admitted to the hospital for COVID than unvaccinated. Since Omicron became dominant, COVID case rates are also lower among the unvaccinated than among the single-, double- and even triple-jabbed

  • Internationally, journalists are now starting to try to switch the narrative away from cases, hospitalizations and deaths by pointing out how unreliable these data are. What they don’t admit is that “dangerous misinformants” have highlighted these problems for two years already

  • Omicron is blowing huge holes in the pandemic narrative, as it predominantly affects the vaxxed, thus proving mandates and vaccine passports are irrational and useless

From [MERCOLA] At this point, there is simply no question. The COVID shots are an abysmal failure in every way possible. Again and again, data analyses from around the world show a negative correlation between “vaccination” rates and worsening infection rates and other health trends.

There’s No Rationale for Passports and Mandates

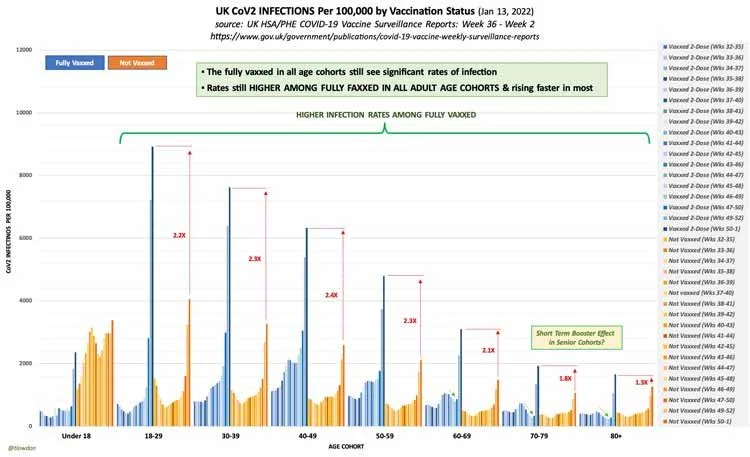
Among the latest data sets to show this are official statistics from the U.K. government. Its “National Flu and COVID-19 Surveillance Report: 13 January 2022 (Week 2)”1 shows COVID infection rates in the U.K. are higher among the “fully vaccinated” in all adult cohorts.

Infection growth rates are also rising faster among the fully vaxxed than in unvaccinated cohorts of all ages. All in all, these data prove that vaccine passports and mandates are completely pointless and nothing more than a coercion tool. In no way do they reduce infection rates, hospitalizations or deaths from COVID.

Regardless of how many shots a person has received, they’re still getting infected and transmitting it. Plus, we know the jabbed are veritable incubators for mutating strains. Everything about this mass vaccination campaign is detrimental to public health.

Far Higher Infection Rates Among the Fully Jabbed

Using U.K. government data, a Twitter user named Don Wolt created a series of helpful graphs that he posted January 16, 2022.2 The graph below shows the differences in infection rates by age and vaccination status, and it is really telling.

Across the board, with the exception perhaps of the 80+ age group, the fully jabbed have significantly higher rates of COVID infection, completely decimating the myth that we’re in a “pandemic of the unvaccinated.” Clearly, that is not the case.

... case rates have been lower in unvaccinated individuals than the single, double, or even triple-jabbed since Omicron became the dominant variant in Scotland. ~ The Herald

(Wolt clarifies that each bar in this graph represents four weeks of data, obtained from successive weekly U.K. HSA reports, and the chart illustrates the rates of infection — i.e., the number of infections per 100,000 people — not absolute numbers. “Vaxxed 2-doses” also includes those who have received a third booster.)

Infection Rates Rising Faster Among Fully Jabbed

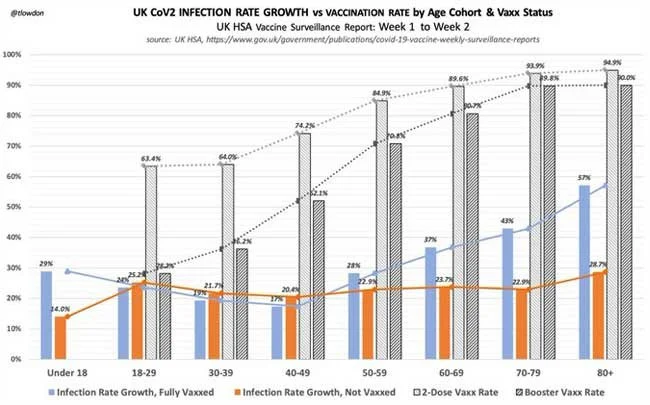
In another graph, you can clearly see how infection rates are also rising faster in fully jabbed cohorts than in the unvaccinated — and this is not a result of higher vaccination rates.

Here, Wolt determined the growth of the infection rate for each age cohort by comparing the data of Week 1 against Week 2 in the surveillance report. As you can see by the orange graph bars, the growth rate of infection among the unvaccinated is relatively flat across age groups, whereas the infection growth rate among the fully jabbed keeps trending upward with age.

As noted by Wolt, this infection growth rate increase is not due to a tandem increase in the number of people getting a second or third jab. The data show that the greater an age cohort’s vaccination rate is, the higher its infection growth rate (i.e., the rate of increase from one week to the next).

Risk of Death Is Extremely Low in Under-50 Age Groups

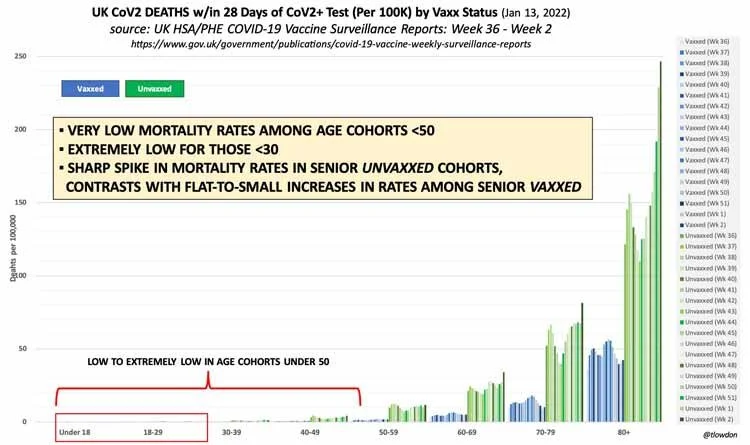
The January 13, 2022, U.K. COVID surveillance report3 does show that, among those aged 50 and over, the COVID shots appear to lower hospitalization rates and death.

However, anyone under the age of 50 who tests positive for SARS-CoV-2 infection still has an exceptionally low risk of hospitalization or death, regardless of vaccination status. In those under the age of 30, the risk of being hospitalized or dying from COVID is “effectively zero,” Wolt notes, which, again, “makes mandated vaccination utterly unwarranted.”

Responding to detractors who point out that the report warns its raw data cannot be used to estimate vaccine effectiveness, Wolt points out that his graphs are not meant to illustrate vaccine effectiveness per se. They merely show rate trends between “vaccinated” and unvaccinated, and these trends clearly invalidate any perceived need for vaccine mandates. Data from Scotland show more of the same. As reported by The Herald, January 13, 2022:4

“Double-jabbed Scots are now more likely to be admitted to hospital with COVID than the unvaccinated amid an increase in elderly people falling ill due to waning immunity.

It comes amid ‘weird’ data showing that case rates have been lower in unvaccinated individuals than the single, double, or even triple-jabbed since Omicron became the dominant variant in Scotland.”

Omicron Forces Media to Rethink What They Report

The COVID pandemic has been all about social engineering, which of course cannot be done without the full complicity of the mainstream media. In a roundabout way, a January 12, 2022, AP News article5 admits this role:

“For two years, coronavirus case counts and hospitalizations have been widely used barometers of the pandemic’s march across the world. But the omicron wave is making a mess of the usual statistics, forcing news organizations to rethink the way they report such figures.

‘It’s just a data disaster,’ said Katherine Wu, staff writer who covers COVID-19 for The Atlantic magazine. The number of case counts soared over the holidays, an expected development given the emergence of a variant more transmissible than its predecessors.

Yet these counts only reflect what is reported by health authorities. They do not include most people who test themselves at home, or are infected without even knowing about it. Holidays and weekends also lead to lags in reported cases.

If you could add all those numbers up — and you can’t — case counts would likely be substantially higher. For that reason, The Associated Press recently told its editors and reporters to avoid emphasizing case counts ... Many news organizations are debating how best to use statistics now during the Omicron surge ...

Hospitalizations and death rates are considered by some to be a more reliable picture of COVID-19’s current impact on society. Yet even the usefulness of those numbers has been called into question in recent days. In many cases, hospitalizations are incidental: there are people being admitted for other reasons and are surprised to find they test positive for COVID.”

Narrative Switch Aimed at Hiding Failures

For those who have been “awake” to the censorship and misleading reporting over the past two years, this attempt at steering the narrative in a new direction is just laughable.

How could the AP possibly have missed the fact that it’s been a data disaster from the start? And intentionally so? Case counts were always unreliable, considering the PCR test cannot diagnose an active infection, and excessive cycle thresholds guaranteed ridiculous amounts of false positives.

COVID hospitalization data were always unreliable, because anyone who tested positive for COVID was counted as a COVID hospitalization whether they were symptomatic or not. Nothing has changed in that regard.

The only thing that has changed is that now media are admitting it — pretending that this is a brand-new development, of course. The same goes for COVID death counts. They were vastly overcounted from the start, again, because of the reliance on faulty PCR testing.

Media now claim to be moving away from “unreliable” data such as case counts, hospitalizations and even deaths, and for all the reasons we’ve been highlighting for the past two years. For those who have paid attention all along, this is clearly an attempt to change the narrative without losing all credibility (which I think is near-impossible at this point).

The fact is that Omicron is making the holes in the narrative so much bigger, it’s all falling apart. They’re completely losing the rationale for vaccine passports and mandates for work, school and social events, as the higher the vaccination rate, the higher the infection rate.

To that end, U.K. Prime Minister Boris Johnson announced January 19, 2022, that he was ending all remaining COVID restrictions in England,6 including mask mandates on public transportation and in schools, as well as vaccine passport requirements for public events.

This is the complete opposite of what the technocrats need in order to justify passports and mandates. To hide, as best as possible, this narrative-killing trend, media are now “explaining” why they won’t be discussing case counts or even hospitalizations or death rates anymore.

If they were, they’d have to admit that the pandemic response is resulting in an ever-growing disaster. So, don’t be surprised if fact checkers start debunking statistics proving what a disastrous failure the shots are by saying the data on cases, hospitalizations and deaths are simply too unreliable to use anymore.

New Narrative Doesn’t Make Sense Either

The new narrative, according to AP News, will highlight things like hospitals running over capacity and general staff shortages.

The problem is, those don’t paint a true picture of COVID’s impact either, because hospitals have furloughed staff due to lack of patients (many have forgone routine medical treatments for fear of COVID), they’ve fired staff for not getting the jab, other staff have simply quit their jobs in the face of vaccine mandates and hospitals have shut down entire wings due to these staff cuts.

Of course, if patients start returning, they might rapidly find themselves with more patients than they can currently handle. What else can you expect when hospitals intentionally make these kinds of cuts?

General staff shortages in other industries are an equally flawed barometer of COVID’s impact. Many are still getting federal assistance and therefore don’t want to reenter the work force. Others are forced out due to vaccine mandates.

Others are too sick to work thanks to COVID jab injuries. As recently reported by OneAmerica,7 a national mutual life insurance company based in Indianapolis, in addition to a 40% increase in deaths among working age Americans (and they’re not dying from COVID), there’s also been a noticeable uptick in short-term and long-term disability claims in the third quarter of 2021 compared to prepandemic levels.

Working age Americans are getting too sick to work, and are dying at unprecedented levels, and it’s not because of COVID infection.

‘We Failed,’ Danish Media Admit

The same attempt at switching the narrative can be seen in other countries. Danish media recently admitted they’ve failed the public by being “almost hypnotically preoccupied with the daily corona counts.”8 “We, the press, must ... take count of our own efforts,” Danish journalist Brian Weichardt writes, “And we’ve failed.”

Weichardt admits that journalists failed to ask authorities for clear answers as to “what it meant in concrete terms that people are hospitalized with corona and not because of corona.” He also admits that this “makes a difference.” This, again, is precisely what many of us have been saying for the past two years, and all we got for the effort was a domestic terrorist label.

Weichardt, in this piece, tries to shift the blame from journalists to the authorities themselves. They’re to blame, he thinks. “The messages of the authorities and politicians to the people of this historic crisis leave much to be desired,” he writes, ignoring the fact that a journalist’s No. 1 duty is to actually investigate, to double-check and to question, and not simply act as a two-legged parrot.

For two years straight, any dissenting opinion has been labeled as dangerous misinformation, even when completely accurate, because that’s how propaganda works. The fact that press members are now starting to backtrack in order to save what little credibility they have left does not change the fact that they have, nearly universally, acted as promoters of propaganda and nothing else.

Now that a majority of people are onto their spiel, they’re trying to pretend as though it were all a genuine mistake. Nice try. Let’s see how these pharma-backed propaganda jockeys fare when it comes to reporting the truth about COVID jab injuries. That will be where the rubber meets the road in terms of regaining credibility, as it will force them to bite the hand that feeds them — the drug industry.

The sad truth is, we’re likely facing an avalanche of serious chronic ailments going forward, among them, neurodegenerative diseases, as detailed by Stephanie Seneff, Ph.D., in her article “SARS-CoV-2 Vaccines and Neurodegenerative Disease.”9 A short summation of this article reads as follows:

“There are many reasons to be wary of the COVID-19 vaccines, which have been rushed to market with grossly inadequate evaluation and aggressively promoted to an uninformed public, with the potential for huge, irreversible, negative consequences.

One potential consequence is to exhaust the finite supply of progenitor B cells in the bone marrow early in life, causing an inability to mount new antibodies to infectious agents. An even more worrisome possibility is that these vaccines, both the mRNA vaccines and the DNA vector vaccines, may be a pathway to crippling disease sometime in the future.

Through the prion-like action of the spike protein, we will likely see an alarming increase in several major neurodegenerative diseases, including Parkinson’s disease, CKD, ALS and Alzheimer’s, and these diseases will show up with increasing prevalence among younger and younger populations, in years to come.

Unfortunately, we won’t know whether the vaccines caused this increase, because there will usually be a long time separation between the vaccination event and the disease diagnosis.

Very convenient for the vaccine manufacturers, who stand to make huge profits off of our misfortunes — both from the sale of the vaccines themselves and from the large medical cost of treating all these debilitating diseases.”

Sources and References

America’s food systems are on the brink of collapse due to labor shortages caused by Irrational COVID Injection Mandates and other unresolved supply chain issues

From [HERE] America’s food systems are on the brink of collapse due to the strain caused by the post-vaccine omicron variant of the Wuhan coronavirus (COVID-19), labor shortages caused by vaccine mandates and other unresolved supply chain issues.

Economic analysts and food industry executives believe that supply challenges are currently at their worst since the pandemic began nearly two years ago. Now, these shortages are being caused by a combination of unresolved supply chain problems and vaccinated workers calling in sick.

At least part of this problem comes from COVID-19 vaccine mandates.

Natural Products Association President and CEO Daniel Fabricant said: “Vaccine and testing mandates will only slow delivery times and drive up costs for consumers, retailers and manufacturers and damage the ability to keep products on store shelves that consumers have relied on to stay healthy for the past 20 months. We don’t need the vaccine mandate when the country is already plagued by concerns of rising inflation and product availability.”

Experts warn that the situation could persist for weeks or even months, and the eventual waning of the current COVID-19 wave won’t be enough to resolve the slowdown of food production. (Related: Omicron cripples labor force of highly vaccinated New York City.)

Eddie Quezada, a produce manager at a Stop & Shop in Northport, New York, said the post-vaccine omicron wave has caused more staffing shortages in his department than any previous wave of the pandemic. Around one in every five members of his staff contracted COVID-19 this January.

Quezada said his store is also having trouble procuring goods due to delivery drivers being laid off due to the mandate or vaccinated drivers contracting COVID-19. Earlier this month, he received less than half of the strawberries he ordered. “There is a domino effect in operations,” he said.

Keith Milligan, the owner of several Piggly Wiggly franchises in Georgia and Alabama, said about one-third of his employees who organize and load products into trucks at the grocery chain’s distribution centers were out sick with COVID-19 during the first week of January.

Milligan said his stores are still struggling to keep food stocks due to staffing issues. Frozen vegetables and canned biscuits are running dangerously low, he said.

Vivek Sankaran, CEO of grocery chain Albertsons, said his company was expecting supply issues to be resolved by now. “Omicron has put a bit of a dent on that,” he said. He expects more supply challenges to pop up over the next month or so.

In-stock levels of food products at American retailers are down to just 86 percent of what is normal, according to data from market research experts. This is lower than last summer when stocks were at around 90 percent of normal.

Restaurants not faring any better

The supply chain disruptions are affecting the restaurant industry as well. Some of the country’s largest employers in the industry, like McDonald’s, Starbucks and Chipotle, are being forced to reduce their working hours in response to the labor shortage and the ongoing coronavirus surge, which are wreaking havoc on their fully vaccinated workforces.

According to CEO Chris Kempczinski, operating hours of McDonald’s locations across the country are now around 10 percent shorter on average than before the pandemic.

Starbucks recently announced that nearly 9,000 of its more than 15,000 stores in the U.S. will be modifying their store hours due to the number of workers currently out sick due to COVID-19 and other “concerns over customer and worker safety.”

“We will always make proactive decisions that prioritize the health and well-being of our customers and our partners,” said Starbucks in an email. The company warned that customers may experience a lack of specific products, a slowdown in mobile ordering and reduced payment options due to staffing shortages.

“We saw about an average of one-hour reduction in operating hours at Popeyes during this quarter relative to pre-pandemic levels, said Jose Cil, CEO of Restaurant Brands International, which manages several fast-food chains like Popeyes and Burger King.

NY Mask Mandate Voided as an Abuse of Power, Violated the Separation of Powers. NY Heath Agency is an Unelected Body of Public Officials, Has No Authority to Enact Laws. Laws are Made by Legislature

From [HERE] Enacting any laws to end COVID "is entrusted solely to the State Legislature," Nassau County Judge Thomas Rademaker wrote in the opinion.

  • "Should the State Legislature, representative of and voted into office by the citizens of New York, after publicly informed debate, decide to enact laws requiring face coverings in schools and other place places then the Commissioner would likely be well grounded in properly promulgated and enacted rules to supplement such laws."

  • The opinion also explained that there must always be a factual basis for emergency rulemaking by agencies. Such a basis cannot be cut and pasted to each request to renew an emergency. Here, the regulation contained no factual basis as to how the masks are necessary to the emergency (necessary to stop the spread)

A Long Island judge struck down New York state’s indoor mask mandate Monday, saying health officials needed approval from the legislature for a December rule requiring face coverings in schools, transit hubs and other indoor settings.

State Supreme Court Justice Thomas Rademaker ruled in Nassau County that Health Commissioner Mary Bassett didn’t have the authority to issue an emergency regulation last year requiring masks in indoor settings. Dr. Bassett’s masking rules were issued after Gov. Kathy Hochul declared a state of emergency amid rising Covid-19 infections on Nov. 26.

Judge Rademaker wrote that the regulations needed to be “tailored, necessarily related, and attached to a law that the State Legislature has passed.” He struck down the regulations and barred the state from enforcing them.

In a statement, Ms. Hochul, a Democrat, said the mask requirements helped curb the spread of Covid-19. “We strongly disagree with this ruling, and we are pursuing every option to reverse this immediately,” she said.

The ruling was the latest setback dealt by the judicial branch to government-imposed Covid-19 restrictions. The U.S. Supreme Court earlier this month blocked federal vaccine-or-testing rules for large employers, but federal courts have allowed state and federal vaccine mandates for healthcare workers.

Judge Blocks Biden's Irrational, Harmful Injection Mandate for Federal Workers

From [HERE] Trump-appointed federal judge issued a nationwide injunction Friday blocking the requirement for federal employees to get inoculated against Covid-19.

Feds for Medical Freedom, a Nevada nonprofit comprised of thousands of employees of federal agencies, formed to oppose the Biden administration’s Covid-19 vaccine mandates, and dozens of its members sued President Joe Biden, all members of his Cabinet and other federal officials on Dec. 21 in Galveston federal court.

The lawsuit took aim at the White House’s directives for federal agencies to require Covid vaccines of all their employees and for federal contractors to do the same with their workforces or face losing their contracts with the government.

“I have determined that ensuring the health and safety of the federal workforce and the efficiency of the civil service requires immediate action to protect the federal workforce and individuals interacting with the federal workforce,” Biden said in a Sept. 9 statement unveiling the directive.

 With the federal contractor mandate already blocked by a nationwide injunction, Feds for Medical Freedom’s attorney Trent McCotter of the Washington firm Boyden Gray & Associates acknowledged in a Jan. 13 preliminary injunction hearing he does believe Biden has the power to force members of the military to get the jab under Article II of the Constitution, but argued that authority doesn't extend to civilians.

“I don’t think there’s any inherent Article II power over civil employees being vaccinated," McCotter said. "And I don’t think there’s any statutory provision that has actually given the executive this power. … Maybe it’s a separate question whether Congress could do so. I just don’t believe they have done so.”

Justice Department attorney James Gillingham disputed that claim. He said Article II gives a president authority to oversee the federal workforce, and said Congress recognized that authority with passage of Section 7301 of the U.S. Code, which states, “The president may prescribe regulations for the conduct of employees in the executive branch.”

“I think that the act of getting vaccinated is definitely something that would be conduct and falls within even the congressional recognition of this power," Gillignham said.

He argued that “given we’re in a unique situation” of a pandemic in which Covid-19 has killed more than 800,000 Americans, hospitalized 3.5 million and hundreds of thousands are testing positive every day, the president taking steps to ensure the safety of the federal workforce is “something that is right in the middle of what [Biden] is charged to do.”

U.S. District Judge Jeffrey Brown asked Gillingham how far the president could extend that power.

“I think we’re not close to the edges of the power,” Gillingham replied. “There would be a limit. We’re just not near that limit.”

Brown, a Donald Trump appointee, also probed the attorneys on how soon a federal employee could face discipline for not complying.

While they agreed they did not know any government worker who had been suspended or fired yet, McCotter said plaintiff Keri Divilbiss, a Houston-area employee of the Agriculture Department, had received a notice of suspension that could be enforced as soon as Friday.

Apparently timing his order to prevent the agency from suspending Divilbiss, Brown issued a nationwide injunction early Friday against the mandate, citing the U.S. Supreme Court’s recent decision to stay another one from the Occupational Safety and Health Administration requiring large businesses to get their staff inoculated against Covid-19 or force them to undergo weekly tests for the virus.

“The court notes at the outset that this case is not about whether folks should get vaccinated against Covid-19—the court believes they should,” Brown wrote. “It is not even about the federal government’s power, exercised properly, to mandate vaccination of its employees. It is instead about whether the president can, with the stroke of a pen and without the input of Congress, require millions of federal employees to undergo a medical procedure as a condition of their employment. That, under the current state of the law as just recently expressed by the Supreme Court, is a bridge too far.”

Noting the government has provided no examples of a previous president invoking Article II power to impose medical procedures on civilian federal employees, Brown found Biden had overstepped his authority.

“Congress appears in § 7301 to have limited the president’s authority in this field to workplace conduct. But if the court is wrong and the president indeed has authority over the conduct of civilian federal employees in general—in or out of the workplace—'what is the logical stopping point of that power?’” the judge wrote, citing the Sixth Circuit’s Jan. 5 order in a case challenging the federal contractor vaccine mandate.

“Is it a ‘de facto police power?’" Brown added. “The government has offered no answer—no limiting principle to the reach of the power they insist the president enjoys. For its part, this court will say only this: however extensive that power is, the federal-worker mandate exceeds it.”

The Justice Department urged Brown not to issue a nationwide injunction because most of the around 50 individual plaintiffs have applied for an exemption on religious or medical grounds from the vaccine mandate. It said he could tailor the injunction to the dozen who have stated in affidavits they don’t plan on asking for exemptions.

But the judge determined tailoring would not be practical and would be unwieldy given the large number of federal employees who oppose the mandate.

“The lead plaintiff, Feds for Medical Freedom, has more than 6,000 members spread across every state and in nearly every federal agency, and is actively adding new members,” he wrote.

Despite the thousands of holdouts, most federal employees have hitched up their sleeves and received the shots.

The White House set a Nov. 22 deadline for federal employees to comply but noted in an update in early December it was not a hard deadline.

“For those employees not yet in compliance, agencies are undertaking a period of education and counseling, to be followed by additional enforcement steps," it said. "These efforts have already resulted in increased levels of vaccination and compliance. As of Dec. 8, 2021, the federal government has achieved 97.2% compliance with 92.5% of employees having received at least one Covid-19 vaccination dose.” 

The Justice Department said it will appeal Brown's order.

Mandating a vaccine to stop the spread of a disease requires evidence that it prevents infection or transmission. There's NO EVIDENCE the Fake-Vax Does that, so It's irrational, legally indefensible

From [WSJ] Federal courts considering the Biden administration’s vaccination mandates—including the Supreme Court at Friday’s oral argument—have focused on administrative-law issues. The decrees raise constitutional issues as well. But there’s a simpler reason the justices should stay these mandates: the rise of the Omicron variant.

It would be irrational, legally indefensible and contrary to the public interest for government to mandate vaccines absent any evidence that the vaccines are effective in stopping the spread of the pathogen they target. Yet that’s exactly what’s happening here.

oth mandates—from the Health and Human Services Department for healthcare workers and the Occupational Safety and Health Administration for large employers in many other industries—were issued Nov. 5. At that time, the Delta variant represented almost all U.S. Covid-19 cases, and both agencies appropriately considered Delta at length and in detail, finding that the vaccines remained effective against it. 

Those findings are now obsolete. As of Jan. 1, Omicron represented more than 95% of U.S. Covid cases, according to estimates from the Centers for Disease Control and Prevention. Because some of Omicron’s 50 mutations are known to evade antibody protection, because more than 30 of those mutations are to the spike protein used as an immunogen by the existing vaccines, and because there have been mass Omicron outbreaks in heavily vaccinated populations, scientists are highly uncertain the existing vaccines can stop it from spreading. As the CDC put it on Dec. 20, “we don’t yet know . . . how well available vaccines and medications work against it.”

The Supreme Court held in Jacobson v. Massachusetts (1905) that the right to refuse medical treatment could be overcome when society needs to curb the spread of a contagious epidemic. At Friday’s oral argument, all the justices acknowledged that the federal mandates rest on this rationale. But mandating a vaccine to stop the spread of a disease requires evidence that the vaccines will prevent infection or transmission (rather than efficacy against severe outcomes like hospitalization or death). As the World Health Organization putsit, “if mandatory vaccination is considered necessary to interrupt transmission chains and prevent harm to others, there should be sufficient evidence that the vaccine is efficacious in preventing serious infection and/or transmission.” For Omicron, there is as yet no such evidence.

The little data we have suggest the opposite. One preprint study found that after 30 days the Moderna and Pfizer vaccines no longer had any statistically significant positive effect against Omicron infection, and after 90 days, their effect went negative—i.e., vaccinated people were more susceptible to Omicron infection. Confirming this negative efficacy finding, data from Denmark and the Canadian province of Ontario indicate that vaccinated people have higher rates of Omicron infection than unvaccinated people.

Meantime, it has long been known that vaccinated people with breakthrough infections are highly contagious, and preliminary data from all over the world indicate that this is true of Omicron as well. As CDC Director Rochelle Walensky put it last summer, the viral load in the noses and throats of vaccinated people infected with Delta is “indistinguishable” from that of unvaccinated people, and “what [the vaccines] can’t do anymore is prevent transmission.”

There is some early evidence that boosters may reduce Omicron infections, but the effect appears to wane quickly, and we don’t know if repeated boosters would be an effective response to the surge of Omicron. That depends among other things on the severity of disease Omicron causes, another great unknown. According to the CDC, the overwhelming majority of symptomatic U.S. Omicron cases have been mild. The best policy might be to let Omicron run its course while protecting the most vulnerable, naturally immunizing the vast majority against Covid through infection by a relatively benign strain. As Sir Andrew Pollard, head of the U.K.’s Committee on Vaccination and Immunisation, said in a recent interview, “We can’t vaccinate the planet every four or six months. It’s not sustainable or affordable.”

In any event, the vaccine mandates before the court don’t require boosters. They define “fully vaccinated” as two doses of Moderna or Pfizer-BioNTech or one dose of Johnson & Johnson. Even if boosters would help, the mandates would leave tens or hundreds of thousands of unboosted employees on the job, who have zero or negative protection against Omicron infection, and who would be highly contagious if they become infected. In other words, there is no scientific basis for believing these mandates will curb the spread of the disease.

Omicron was mentioned sparsely at Friday’s oral argument, but the justices—particularly those most favorable to the mandates—appeared to labor under drastically false assumptions. Justice Stephen Breyer suggested that if mandatory vaccination went forward, that would prevent all new Covid infections—750,000 new cases every day, he said. This is wildly false. So is Justice Sonia Sotomayor’s assertion that “we have over 100,000 children . . . in serious condition, many on ventilators.” According to Health and Human Services Department data, there are currently fewer than 3,500 confirmed pediatric Covid hospitalizations, and that includes patients who tested positive and were hospitalized for other reasons. 

It is axiomatic in U.S. law that courts don’t uphold agency directives when the agency has entirely failed to consider facts crucial to the problem. In many contexts courts send regulations back to the agency for reconsideration in light of dramatically changed circumstances. If the agency’s action “is not sustainable on the record itself, the proper judicial approach has been to vacate the action and to remand the matter back to the agency for further consideration,” as the U.S. Circuit Court of Appeals for the District of Columbia put it.

Neither HHS nor OSHA ever considered Omicron or said a word about vaccine efficacy against it, for the simple reason that it hadn’t yet been discovered. In these circumstances, longstanding legal principles require the justices to stay the mandates and send them back to the agencies for a fresh look.

Dr. Montagnier was a winner of the 2008 Nobel Prize in Physiology or Medicine for discovering the human immunodeficiency virus. Mr. Rubenfeld is a constitutional scholar.

UK Authorities Admit that ONLY 6,183 of All COVID Deaths had COVID Listed as the Sole Cause of Death on Death Certificates. Contradicting the Govt and Media's Claim that Over 150,000 Died from COVID

From [HERE] The UK Office for National Statistics admits just 6,000 people died of Covid-19 in England and Wales between Feb 2020 and Dec 2021. This is less than the rate of those killed in car accidents. And for that the Government closed down the entire economy with catastrophic bankruptcies, suicides, loss of income and pensions and closed hospitals resulting in untreated cancer and other deadly conditions and the release of hospital patients into care homes where record deaths occurred from covid infections.

In response to a freedom of information that requested the Office for National Statistics (ONS) to supply the number of deaths solely caused Covid-19, where Covid-19 was the only cause of death listed on the death certificate. [MORE]

the Office for National Statistics has admitted that just 6,183 people actually died of Covid-19 in England and Wales between February 1st 2020 and 31st December 2021, exposing the 150,000 death toll as an extraordinary (but long reported on Freenations) lie.…

According to DailyExpose; The ONS responded to the FOI on the 17th Jan 22, proving a breakdown of the number of deaths solely due to Covid-19 by age and sex between 1st Feb 20 and 31st Dec 21.

The response from the ONS revealed that there had been just 3,362 deaths among males between 1st Feb 20 and 31st Dec 21, and 2,821 deaths among females during the same time frame. The vast majority among the elderly population. This is a far cry from the claim of 150,000+ Covid-19 deaths made by the UK Government and its institutions.


The ONS also revealed that just 3 people under the age of 20 died of Covid-19 between 1st Feb 20 and 31st Dec 21, putting further shame on the UK Governments decision to overrule the Joint Committee on Vaccination and Immunisation and administer an experimental Covid-19 injection; that is incapable of preventing infection or transmission, to children.

According to the Coronavirus dashboard on the UK Government site, as of 31st December 2021 the UK Government claimed a total of 149,217 people had died of Covid-19 since the start of the Covid-19 pandemic at the beginning of 2020.


But the ONS have confirmed the true number is just 6,183, and here’s how the actual number of deaths look in comparison to the misleading 150,000 lie perpetuated by the UK Government and mainstream media.

This was not a real pandemic. Even taking the completely flawed definition of a COVID death (both the American CDC and the British Office for National Statistics are now admitting they have been fraudulent), Infection Survival rates have been extremely high. As of 3/12/2021

Disastrous vaccination programme

Deaths following vaccination in the USA, UK and EU have now reached some 50,000 with millions of adverse reactions, half of them serious. In the UK the evidence is surely now incontrovertible – that the rise and fall in UK vaccination levels produces the rise and fall in COVID infections.

Between 10th December and 21st December the booster daily rate rose by 125%. This was followed by a 142% increase in cases between 21st December and 4th January.

The reverse has also proven to be the case for as the booster rate fell by 85% between 21st December and 3rd January so there followed a big fall of 67% in COVID cases between 4th January and 16th January.

There has been a further rise in booster take up between 2nd January (111,000 per day) and 8th January (235,000) which produced a rise in infections between 16th January (74,494 infections) and 19th January (108,069 infections) – another direct linkage!

Nor can the Government claim a saving of lives for since the booster programme started on 1st October daily deaths doubled between 14th October and 8th January.

NHS forced vaccinations

As the deadline for NHS “frontline” staff to be vaccinated looms it is worth recording not only the many conventions, declarations and standards of international medical practise which forbid compulsory or coerced vaccinations but also the recent statement

from the World Health Organisation “if mandatory vaccination is considered necessary to interrupt transmission chains and prevent harm to others, there should be sufficient evidence that the vaccine is efficacious in preventing serious infection and/or transmission.”

But we know that the vaccines prevent neither infection nor infectiousness and recent statistics from the UK Government demonstrate that by weeks 49 to 52 of 2021 all age groups which have been triple vaccinated show an immune system performance far inferior to the unvaccinated (between 7% and 60% according to age group).

Other statistics from the UK Health Security Agency Covid-19 vaccine surveillance report Week 42 Page 13 show covid cases in the vaccinated between 27% and 124% higher than the unvaccinated. COVID cases:

The UK’s Office for National Statistics admit a large increase in deaths among 15-19 year old males since vaccination was rolled out for that age group.

  • May-Dec, 2020: 257 deaths

  • May-Dec, 2021: 402 deaths (of which 2 deaths were due to covid)

There are thousands of immunology experts, researchers and medical practitioners who know these dangers and reject the vaccination programme. In a great embarrassment for the British Government an NHS doctor was filmed telling the Health Secretary why he would not be vaccinated.

In the light of this evidence and the quite clear statements of the Council of Europe, UNESCO, the Geneva Convention and the Nuremberg Code politicians who press ahead with the compulsory vaccinations for health care staff are courting serious legal liability – in addition to the thousands of doctors and nurses who will resign rather than be vaccinated (they have witnessed too many deaths and too much suffering among those who have been vaccinated).

Australian dictatorship proves a disaster

Australian politicians have instituted some the most draconian and anti democratic controls and vaccine mandates on their people – and yet 69% of New South Wales  hospitalisations are of the vaccinated and the post vaccination deaths have reached an historic peak.

Australia’s vaccine fanatics have certainly been proven wrong. Since the rapid increase in the Australian’s vaccination programme in the latter part of 2021 covid infections rose from 31,000 on 15th July to over 2 million on 21st January (a 6,600% increase). A familiar pattern in other countries as readers of Freenations will know from past posts. But a pattern the vaccine fanatics and criminal political and media establishments ignore, deny and censor!