CDC Data Shows that COVID Injections Have Caused at Least 965,843 "Adverse Events," including 20,244 Deaths and 33,675 People have been Permanently Disabled (only 1% of adverse events are reported)
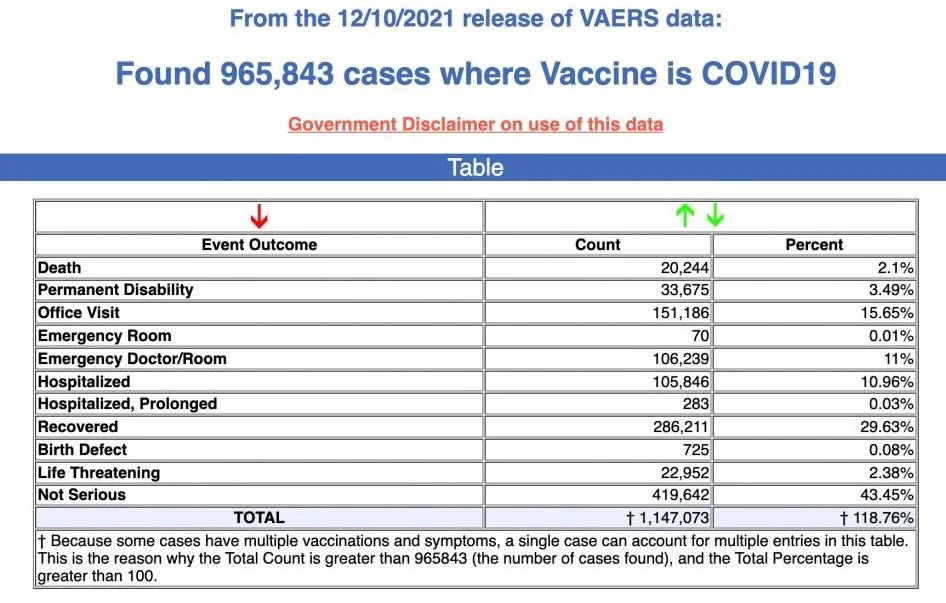
/From [CHD] The Centers for Disease Control and Prevention today released new data showing a total of 965,843 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and Dec. 10, 2021, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 20,244 reports of deaths — an increase of 358 over the previous week — and 155,506 reports of serious injuries, including deaths, during the same time period — up 4,560 compared with the previous week.
Excluding “foreign reports” to VAERS, 691,884 adverse events, including 9,295 deaths and 59,767 serious injuries, were reported in the U.S. between Dec. 14, 2020, and Dec. 10, 2021.
Foreign reports are reports received by U.S. manufacturers from their foreign subsidiaries. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 9,295 U.S. deaths reported as of Dec. 10, 21% occurred within 24 hours of vaccination, 26% occurred within 48 hours of vaccination and 61% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 480 million COVID vaccine doses had been administered as of Dec. 10. This includes279 million doses of Pfizer, 184 million doses of Moderna and 17 million doses of Johnson & Johnson (J&J).
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed. Historically, VAERS has been shown to report only 1% of actual vaccine adverse events. [MORE]
CDC Study at Federal Prison in TX Finds No Vaccine Benefit: Vaccinated and Unvaxed Persons Infected w/COVID Transmitted It at the Same Rate. No Infected Prisoners Died Even Though Over 70% were Obese
/From [GR} CDC Researchers studied a Corona outbreak in a prison in Texas in July 2021. In the following weeks, regular smears and tests were taken from a selected group of inmates. The result: There is no difference whatsoever between the vaccinated and non-vaccinated inmates.
No statistically significant difference was detected in the duration of viral culture positivity between participants who were fully vaccinated (median: 5 days) compared with those who were not fully vaccinated.
It states:
“Conclusions As this field continues to develop, clinicians and public health practitioners should consider vaccinated persons who become infected with SARS-CoV-2 to be no less infectious than unvaccinated persons. These findings are critically important, especially in congregate settings where viral transmission can lead to large outbreaks.”
Not a single one of the infected prisoners died of Covid-19, although over 70 percent were overweight or obese, according to the study. One vaccinated and one unvaccinated were hospitalized. The most common symptoms were a runny nose, impaired sense of taste and cough. Since a prison is a confined space, the results are very revealing for hospitals, nursing homes, office complexes and enclosed spaces in general.
As this study shows, every vaccinated nurse or doctor is infectious for as long and just as severely as an unvaccinated doctor or nurse. This gene therapy does not bring about clinical or sterile immunity.
They warned health practitioners to “consider vaccinated persons who become infected with SARS-CoV-2 to be no less infectious than unvaccinated persons. These findings are critically important, especially in congregate settings where viral transmission can lead to large outbreaks”. [MORE]
Doctor Says Covid Injections Damage the immune system, Impairing the body’s ability to fight infection, viruses and disease. The Injections have Killed More People than Any Other Vaccine in History
/From [HERE] Question– Does the Covid-19 vaccine damage the immune system?
Answer– It does. It impairs the body’s ability to fight infection, viruses and disease.
Question– If that’s true, then why haven’t more people died after getting vaccinated?
Answer– I’m not sure what you mean? The vaccine has killed more people than any vaccine in history. “So far, in the United States, the death toll is three times higher than the total of all vaccines in the last 35 years.” That’s simply astonishing. We’ve also seen a steady rise in all-cause mortality and excess deaths in the countries that launched mass vaccination campaigns earlier in the year. Sometimes the increase is as much as 20 percent over the five-year average. That is a massive spike in fatalities, and it’s largely attributable to the vaccine. So, what do you mean when you say, “Why haven’t more people died”? Did you expect to see people clutching their hearts and dropping dead after getting jabbed? That’s a very naive understanding of how the injection works. (See: “COVID Deaths Before and After Vaccination Programs”, You Tube; 2 minutes)
Question– All I’m saying is that the percentage of people that have died is quite small compared to the tens of millions that have been vaccinated.
Answer– And all I’m saying is that if the vaccine is lab-generated pathogen– and I think it is– then it certainly was not designed to kill people on the spot. It was engineered to produce a delayed reaction that gradually but relentlessly erodes the health of the vaccinee. In other words, the full impact of the blood clots, bleeding, autoimmune issues and other vaccine-generated injuries will only be fully felt at a later date via increasing incidents of heart attacks, strokes, vascular illness and even cancer. (Check out the “latest trend of cardiac attendances by Scottish Ambulance Service – this is *excess* above the 2018/19 norm. Huge spike in summer, 500 ambulance calls per week above normal, mainly age 15-64. Was settling, then spike up again since late October.” Scottish Unity – Edinburgh Group)
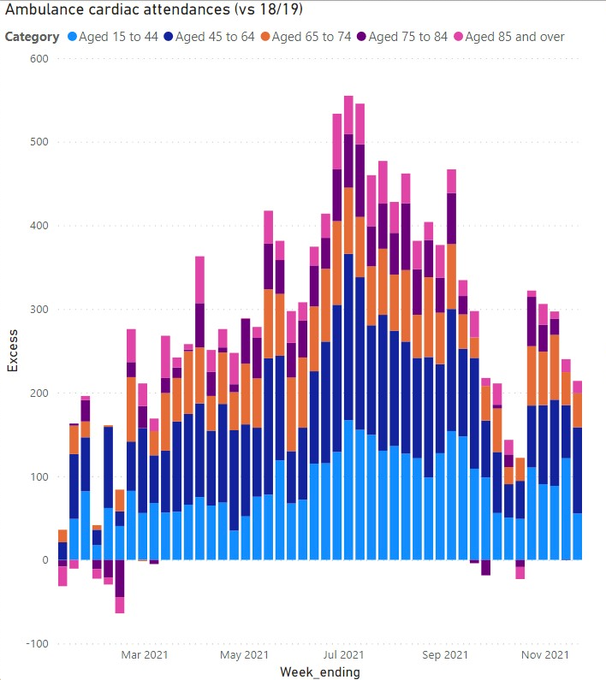
Answer– The chart above shows why cardiac issues have garnered alot of attention lately, but the damage to the immune system is even more concerning.
Question– Can you explain what you mean without getting too technical?
Answer– I can do better than that. I can give you a short clip from an article that covers the latest research. Check it out:
“A Swedish lab study (titled “SARS–CoV–2 Spike Impairs DNA Damage Repair and Inhibits V(D)J Recombination In Vitro“, NIH) released in mid-October found that the spike protein… enters the nucleus of cells and significantly interferes with DNA damage-repair functions compromising a person’s adaptive immunity and perhaps encouraging the formation of cancer cells….
“Mechanistically, we found that the spike protein localizes in the nucleus and inhibits DNA damage repair,” they wrote. “Our findings reveal a potential molecular mechanism by which the spike protein might impede adaptive immunity and underscore the potential side effects of full-length spike-based vaccines.”(“Spike protein in COVID virus and shots weakens immune system, may be linked with cancer: Swedish study“, Lifesite News)
What the researchers found is that the spike protein blocks production of the enzymes that are needed to repair broken DNA which, in turn, prevents the “proliferation” of B and T cells that are needed to fight infection.
Question– Can you explain that in plain English?
Answer– Sure. It means the vaccine short-circuits your immune system which clears the way for infection, disease and an early death. Maybe, you think you can have a long and happy life with a dysfunctional immune system, but I think you’re wrong. The immune system is the shield that protects you from all-manner of potentially-lethal viruses, bacteria and infections. It is not just the first-line of defense, it’s the only line of defense. Absent the full protection of B and T cells to fight-off foreign intruders, the prospects for survival are miniscule at best.
In order to underscore that point, check out this video of British Funeral Director, John O’ Looney, who has provided regular updates on what he is seeing on the ground 10 months following the vaccination rollout. It’s a disturbing account of the catastrophe that is now unfolding before our eyes:
(30 second mark) “So what we’re seeing is an unnaturally large number of deaths due to heart attack, stroke, aneurism; and these are all the result of thrombosis … Embolisms in the lungs the legs, various places that are causing these deaths that are well documented by the local coroners and well-documented across the country. And no one seems to be concerned about the alarming rise of (blood clots) I’ve seen more in this year than in the last 14 years….
That’s one kind of death we’re seeing, the other kind is the people that are getting sick now as their immune systems finally give up. So, they’ve had the jabs maybe 6 or 8 months ago, and it’s been eating away at their immune system, and now they’re struggling to fight off things like the common cold. So, we’re in winter and there are colds and flus around and these people can’t fight them off. The government are very quick to label it “Omicron”…but they are sick with the common cold. Their immune systems are decimated. It’s much like a cancer patient, who goes through chemotherapy and it decimates their immune system. And they have to be very careful because the common cold or flu can kill them. And this is what we’re seeing now…
We’re nearly 12 months since the first jabs began, so their immune systems are falling apart; that is the reality and that’s what I’m seeing... and they can’t cope with a cold anymore. … When I went to the meeting in Westminster in September, the scientist predicted that this is what would happen and, lo-and-behold, that’s what happening. The people are getting sick and dying….. It’s frightening.” (“Omicron is ‘vaccine injury’; it’s nothing more than that.” John Looney, Rumble)
Is he right? Is the uptick in fatalities NOT another wave of Covid but the knock-on effects of a cytotoxic injection that targets the immune system leaving millions of people defenseless against routine infections and disease?
It sounds feasible and it certainly fits with the depopulation agenda which requires a hybrid biologic that doesn’t kill its target outright but basically dismantles the critical defense systems that make human survival possible. By disguising a “killer protein”
as a harmless antigen, our pandemic managers have been able to access the bloodstreams of millions of people allowing them to insert a ticking time-bomb that ravages crucial T and B-cell populations leaving victims vulnerable to whatever bug happens to be circulating in the population. As Looney notes, scientists warned of this very outcome when mass vaccination was first proposed. Naturally, opposing views were ignored and censored. Here’s more from a pre-print research paper on the medRxiv server. It helps to explain the vaccine’s impact on the immune system:
“Researchers in The Netherlands and Germany have warned that Pfizer-BioNTech’s … (COVID-19) vaccine induces complex reprogramming of innate immune responses that should be considered in the development and use of mRNA-based vaccines…. Following vaccination, innate immune cells had a reduced response to toll-like receptor 4 (TLR4), TLR7 and TLR8 – all ligands that play an important role in the immune response to viral infection….
“Multiple studies have shown that long-term innate immune responses can be either increased (trained immunity) or down-regulated (innate immune tolerance) after certain vaccines or infections.”…
These results collectively demonstrate that the effects of the BNT162b2 vaccine go beyond the adaptive immune system.. The BNT162b2 vaccine induces reprogramming of innate immune responses as well, and this needs to be taken into account.”…(“Research suggests Pfizer-BioNTech COVID-19 vaccine reprograms innate immune responses”, New-Medical net)
How many people would have gotten vaccinated if they’d known it would reprogram their immune system?
Probably, no one, which is why our public health officials never broach the topic. Anything that veers even slightly from the “vaccines are good for you” narrative is omitted from mainstream coverage and erased on social media. But aren’t people entitled to know what’s going on, what is being injected into their bodies, and what impact it will have on their lives and health? Isn’t that what is meant by “informed consent” or is that another casualty of the rush to inoculate all 7 people on planet earth? Here’s a clip from a short interview with pathologist, Dr. Ryan Cole:
“When we give these shots, we can see the types of white blood cells in the body… and you have a broad array of immune cells that work together to fight off viruses and keep cancers in check. We’re already seeing the signals in the laboratory of decreases in critically important T-cells you need… in your innate immune system. These are the Marines in your body; fighting off viruses fighting cancer…. But what we’re seeing in the laboratory after people get these shots, we’re seeing a very concerning locked-in, low profile of these important killer T-cells that you want in your body. (CD8 cells) And what they do, is keep all other viruses in check.
What am I seeing in the laboratory? I’m seeing an uptick of Herpes family viruses, I’m seeing Shingles, I’m seeing Mono, I’m seeing a huge uptick in human papilloma virus… We are literally weakening the immune systems of these individuals.
Most concerning of all, is there’s a pattern of these types of immune cells in the body that keep cancer in check. Since, January 1, (in the laboratory) I’ve seen a 20X increase of endometrial cancer over what I see on an annual basis.” (“Pathologist Ryan N Cole of the Mayo Clinic on What We Are Seeing In Lab Results”, Rumble; 2 minutes)
“Herpes, Shingles, Mono, and even cancer!” What the heck is going on? This can’t be true, can it?
Yes, it is true; immuno-suppression leads to all kinds of terrible health outcomes. Some readers might recall how Canadian vaccinologist Dr Byram Bridle made similar claims in an interview just a few weeks ago. Here’s what he said:
“What I’ve seen way too much of is people who had cancers that were in remission, or that were being well controlled; their cancers have gone completely out of control after getting this vaccine. And we know the vaccine causes a drop in T-cell numbers, and those T-cells are part of our immune system and they are part of the critical weapons our immune system has to fight off cancer cells; so there’s a potential mechanism there. All I can say, is I’ve had way too many people contact me with these reports for me to feel comfortable. I would say that is my newest major safety concern, and it’s also the one that’s going to be the most under-reported in the adverse data base, because if someone has had cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine.” (“Dr Byram Bridle speaks”, Bitchute, :55 second-mark)
Once again, how many people would have decided to get vaccinated if they knew that it could trigger a flare-up of dormant viruses or cancers in remission? Who would take that risk?
But they don’t know they’re taking a risk, do they, because they haven’t been told the truth. And the reason they haven’t been told the truth is because they are a target in a war of extermination that is being waged on them. Sometimes it’s very hard for people to admit to what they know to be the truth, but the truth is plain to see. Our pandemic managers and their foot-soldiers in the media, public health and government want to do us harm, want to inject us with a mysterious substance that will wreak havoc on our immune systems and shorten our lives. This isn’t just a struggle for personal freedom or bodily autonomy, it’s a battle for survival. We are defending our right to live. Here’s more from Viral Immunologist Dr. Jessica Rose:
“There are studies coming out now, and there are ample signs in the adverse events data, that these products (Covid vaccines) are not only immuno-modulating the immune system and causing hyper inflammation; there are signs now that they are very negatively effecting CD8 T-cell populations. For those who don’t know, this is extremely bad news. It’s only on a few people so far, but the data does not look good so far. These T-cells are the so-called “killer cells”. Their job…is to kill virally infected cells that are showing foreign markers on their surface. So, if these populations are depleted, then that is very bad news, because we don’t have a population of cells in the acquired immune system to remove virally-infected cells.
There are clear signs that are starting to emerge, that there is an “immunity deficiency syndrome” coming about as a result of these products (vaccines) As a result of hyper-stimulation…T-cells being (diminished), and the ever-presence of repeated injections of a cytotoxic protein… I would never, ever recommend that someone who is immuno-compromised to ever go near these things, because I can almost guarantee you, that your condition is going to get worse. Another thing we’re seeing in VAERS is cancers coming out of remission and alot of doctors are reporting this on the ground. And–by the way– this has never happened before, not on this scale; not even close… So, there’s something going on here that warrants further investigation, and it doesn’t look good.” (“Viral Immunologist Dr. Jessica Rose explains the concerning information emerging about the compromised immunity of the vaccinated“, Odysee)
Can you see the pattern yet? Can you see how they’re all saying the same thing? Why is that, do you think?
It’s because it’s the truth, the pure, unvarnished truth.
The point we’re trying to make cannot be overstated: The vaccine is a man-made, lab-generated bioweapon that disables the body’s critical defense system which increases one’s susceptibility to disease by many orders of magnitude. With each additional injection, one is less capable of mounting a sufficient response to routine infections, flus or viruses. That’s going to lead to a tsunami of sickness that will likely overwhelm our public health system and plunge the country deeper into crisis. Is that the plan? Is that what our globalist overlords have in store for us?
We’ll see. Now check out this last clip from video by vaccinologist, Geert Vanden Bossche:
“The first thing I would like to highlight is that Covid-19 is not a disease of healthy people. People who are in good health have a healthy innate immune system that can deal with a number of respiratory viruses without any problem. These people are not only protected against the disease but can even–in many cases– prevent infection. These are people who can contribute to sterilizing immunity and to herd immunity which is very, very important. So, listen: Never, ever allow anyone or anything to interfere or suppress your innate immune system. You can do a bad job yourself by leading an unhealthy life, that is going to suppress your innate immunity, but even worse, is vaccine-induced antibodies that do suppress your innate immunity. And these vaccinal antibodies cannot substitute for it because they lose their efficacy against the virus, and become less and less effective. In contrast to the innate antibodies, they cannot prevent infection, they cannot sterilize the virus. Therefore, they do contribute to herd immunity….
If we suppress these innate antibodies in children, it could lead to autoimmune diseases. This is an absolute “No go” We cannot vaccinate our children with these vaccines. The suppression of innate immunity is already a problem among vaccinees, and they are, indeed, going to have a difficult time controlling a number of diseases, not just Covid-19, but other diseases too …and it will require a very dramatic change in the strategies to help the vaccinees–and my heart goes out to them–because they will need extensive treatment in many cases...
… Boosting them–which means giving them a third dose– is absolutely insane, because what it will do, is increase the immune pressure of the vaccinal antibodies, on their innate immunity. So boosting is absolute nonsense; it is dangerous and should not be done….
So, what does the science tell us? It tells us that it’s innate immunity that will protect us, not the vaccine.” (“Geert Vanden Bossche on Vaccines and the suppression of innate immunity”, Rumble)
So, we now know that– along with the blood clots, the bleeding, the heart attacks, the strokes, the vascular and neurological diseases– the vaccine is also designed to eviscerate the system that protects us from illness and death, the immune system. How steeped in denial one must be not to see the evil that is now among us.
Report from ICNARC in the UK Shows the Majority of Covid ICU Patients in October and November were Double Vaccinated
/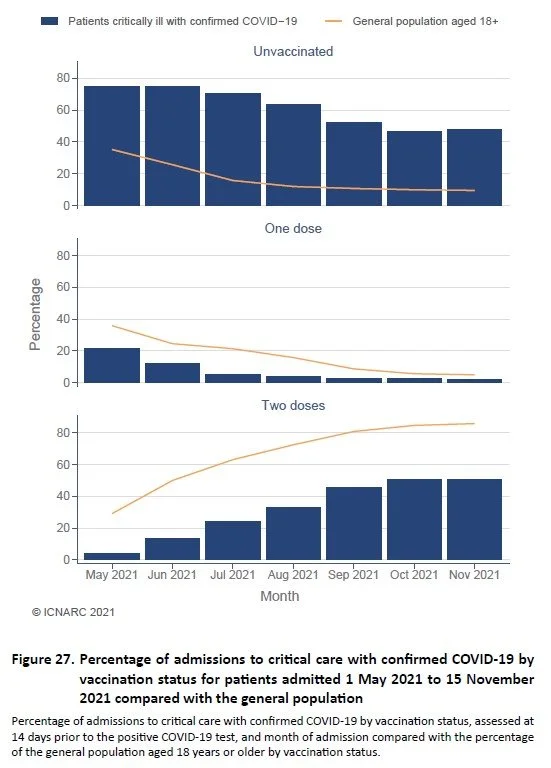
From [HERE] Contrary to the claims made by Dr. Rachel Clarke and Professor Stephen Powis last month and used to blame the unvaccinated for the mounting troubles of the NHS, new data out this week shows that the majority of Covid ICU admissions in October and November were among the vaccinated, not the unvaccinated.
The latest report from ICNARC shows that of Covid ICU patients in England, Wales and Northern Ireland, 50.5% in October and 50.7% in November were double vaccinated. Add to that the 2.8% in October and 1.8% in November who were single-vaccinated and you get overall vaccinated proportions of 53.3% in October and 52.5% in November. That compares to 46.7% unvaccinated in October and 47.5% in November. Note that the unvaccinated here includes people who received a vaccine less than 14 days prior to the positive Covid test, so includes some (an unknown number) who are actually single vaccinated.
This is not what the public has been led to believe by some prominent medics and newspapers.
Two weeks ago, Professor Stephen Powis, the National Medical Director of NHS England, was quoted in the Sunday Times saying: “Data shows that the overwhelming majority of people admitted to intensive care with Covid are not fully vaccinated.” A source was not provided for this claim but the article implied that it meant right now, with an opening paragraph stating: “Hundreds of intensive care beds that could be used for life-saving surgery are instead occupied by unvaccinated Covid patients, one of NHS England’s top officials has said.”
The same day the Sunday Times also printed an article by Dr. Rachel Clarke with the subheading: “Some 75% of those suffocating in intensive care with the coronavirus are unvaccinated.” In it she states: “Of the Covid patients treated in intensive care in recent months, the majority – nearly 75% according to the latest data – have chosen not to be vaccinated.”
The Guardian published a piece in November headlined “ICU is full of the unvaccinated – my patience with them is wearing thin”, written by an anonymous medic who claimed that the ICU patient population “consists of a few vulnerable people with severe underlying health problems and a majority of fit, healthy, younger people unvaccinated by choice”.
Now that the data has been released it’s clear that the claim that ICUs are “full of” the unvaccinated is highly misleading. While the unvaccinated do currently appear to be over-represented (depending how many of them are misclassified), no one now can claim that ICUs are “full of” the unvaccinated or that the unvaccinated constitute the “overwhelming majority” of Covid ICU admissions. If you spot any newspapers still peddling this misinformation, particularly it if is being used to stigmatise and pressure the unvaccinated, you can complain to IPSO here.
Vaccine Acquired Immune Deficiency Syndrome (VAIDS): Covid Injections are causing elevated incidence of myocarditis and other post-vaccine illnesses that may result in Death or Chronic Illness
/
From [HERE] If immune erosion occurs after two doses and just a few months, how can we exclude the possibility that effects of an untested “booster” will not erode more rapidly and to a greater extent?’
A Lancet study comparing vaccinated and unvaccinated people in Sweden was conducted among 1.6 million individuals over nine months. It showed that protection against symptomatic COVID-19 declined with time, such that by six months, some of the more vulnerable vaccinated groups were at greater risk than their unvaccinated peers.
Doctors are calling this phenomena in the repeatedly vaccinated “immune erosion” or “acquired immune deficiency”, accounting for elevated incidence of myocarditis and other post-vaccine illnesses that either affect them more rapidly, resulting in death, or more slowly, resulting in chronic illness.
COVID vaccines are not traditional vaccines. Rather, they cause cells to reproduce one portion of the SARS-CoV-2 virus, the spike protein. The vaccines thus induce the body to create spike proteins. A person only creates antibodies against this one limited portion (the spike protein) of the virus. This has several downstream deleterious effects.
First, these vaccines “mis-train” the immune system to recognize only a small part of the virus (the spike protein). Variants that differ, even slightly, in this protein are able to escape the narrow spectrum of antibodies created by the vaccines.
Second, the vaccines create “vaccine addicts,” meaning persons become dependent upon regular booster shots, because they have been “vaccinated” only against a tiny portion of a mutating virus. Australian Health Minister Dr. Kerry Chant has stated that COVID will be with us foreverand people will “have to get used to” taking endless vaccines. “This will be a regular cycle of vaccination and revaccination.”
Third, the vaccines do not prevent infection in the nose and upper airways, and vaccinated individuals have been shown to have much higher viral loads in these regions. This leads to the vaccinated becoming “super-spreaders” as they carry extremely high viral loads.
In addition, the vaccinated become more clinically ill than the unvaccinated. Scotland reported that the infection fatality rate in the vaccinated is 3.3 times the unvaccinated, and the risk of death if hospitalized is 2.15 times the unvaccinated.
A June report on Israel’s Channel 12 News revealed that in the months since the vaccines were rolled out, 6,765 people who received both shots had contracted coronavirus, while epidemiological tracing revealed an additional 3,133 people contracted COVID-19 from those vaccinatedindividuals.
Meanwhile, New England Journal of Medicine researchers have found that autoimmune response to the coronavirus spike protein may last indefinitely: “Ab2 antibodies binding to the original receptor on normal cells therefore have the potential to mediate profound effects on the cell that could result in pathologic changes, particularly in the long term — long after the original antigen itself has disappeared.” These antibodies produced against the coronavirus spike protein could be responsible for the current unprecedented wave of myocarditis and neurological illnesses, and even more problems in the future.
Indefinite uncontrolled autoimmune response to the coronavirus spike protein may produce a wave of antibodies called anti-idiotype antibodies or Ab2s that continue to damage human bodies long after clearing either Sars-Cov-2 itself or those spike proteins that the shots cause the body’s cells to produce, explained former New York Times reporter Alex Berenson.
Spike protein antibodies may themselves produce a second wave of antibodies, called anti-idiotype antibodies or Ab2s. Those Ab2s may modulate the immune system’s initial response by binding with and destroying the first wave of antibodies.
“Our immune systems produce these antibodies in response to both vaccination and natural infection with COVID,” wrote Berenson. “However – though the researchers do not say so explicitly, possibly because doing so would be politically untenable – spike protein antibody levels are MUCH higher following vaccination than infection. Thus the downstream response to vaccination may be more severe.”
America’s Frontline Doctors (AFLDS) Chief Science Officer former Pfizer Vice President Michael Yeadon responded to the research: “This is unprecedented. What is happening is not understood.
“Commentators on Israeli TV have reported that contacts in the Health Ministry have termed this ‘immune erosion’:
“While some are concerned that blood IgG antibodies fall with time, I am not convinced that this is a relevant measure,” Yeadon continued. “Respiratory virus infection begins in the lungs and nasopharynx. Neither are protected by blood antibodies, which are molecules too large to diffuse into airways tissue. What protects against infection and initial viral replication is secretory IgA antibodies and T-cells in airways, neither of which have been studied in any efficacy trial.
“The empirical data are very worrying. In most countries now, high fractions of the population have been vaccinated. If the Swedish study is a guide, we should anticipate seeing this immune erosion more widely. The most concerning aspect of that study is that those most in need of protection are those in whom immune erosion is most marked: the elderly, males, and those with comorbidities.
“Some have used the results of this study to support the widespread use of so-called ‘booster’ shots. It has to be said: No one has any safety data about such a plan. If immune erosion occurs after two doses and just a few months, how can we exclude the possibility that effects of an untested ‘booster’ will not erode more rapidly and to a greater extent? And what then would be the response? A fourth injection. Madness.
“It’s long past time when known safe and effective drug treatments be used as the leading response to symptomatic infection (antivirals, corticosteroids, anti-inflammatories).
“In this way, we don’t expose entire populations to experimental medical interventions when only a very small fraction of the population are at notable risk from this virus, which, all hype aside, is by no means exceptional in its lethality compared with numerous others such as seasonal influenza.”
Yeadon concluded:
“Europe is all but gone. The lights are going out. Austria and Germany now subject their unvaccinated to house arrest. In Greece, the unvaccinated are subject to escalating fines, non-payment of which is converted into prison time. In Lithuania, the unvaccinated are excluded from society. The booster campaigns are running full-pelt everywhere.
“Someone, somewhere knows what’s going to happen. Will immunity-erosion worsen more speedily and to a greater extent after this untested ‘booster’? The U.K. government has already said that the fourth injection is to take place a mere three months after the third. It’s utter madness. Yet such is the hermetic control of media that nothing much emerges into the public consciousness.”
Massachusetts Covid “breakthrough cases" surge 11,321 last week, smashing record high for the state
/From [HERE] More than 11,000 fully vaccinated people in the Bay State tested positive for coronavirus last week as part of the post-Thanksgiving surge, a daily average of about 1,617 people as breakthrough infections hit a record high in the state.
The count of 11,321 breakthrough cases last week was a 71% spike from the tally of 6,610 breakthrough infections in the prior week.
Breakthrough cases in Massachusetts have been making up about 40% of the state’s overall cases in recent months amid the more highly contagious delta variant.
Overall case counts in the state have been spiking in the last few weeks, and breakthrough infections are following that surging trend as the vaccine’s effectiveness wanes after six months. Officials are urging people to get a booster shot as soon as possible.
Overall, 88,968 fully vaxxed people have tested positive for the virus, according to new data from the state Department of Public Health on Tuesday. That’s 1.8% of the more than 4.9 million fully vaxxed people in Massachusetts.
The 88,968 overall cases is a jump of 11,321 breakthrough infections from last week — or a daily average of 1,617 fully vaccinated people testing positive.
Last Tuesday’s report had showed an increase of 6,610 breakthrough cases, a daily rate of 944 fully vaxxed people testing positive.
The week before that was a rise of 6,917 infections — a daily average of 988.
The previous week’s count was 5,313 cases, a daily rate of 759.
Breakthrough hospitalizations have been accounting for about 35% of current COVID-19 hospitalizations. Those who are unvaccinated are at a much higher risk for a severe case and hospitalization.
There have been 2,716 hospitalizations among fully vaccinated people in Massachusetts, which represents 0.05% of those who are fully vaxxed.
The 2,716 total patients is a one-week increase of 273 fully vaxxed patients. That’s way up from the previous weekly increase of 158 fully vaxxed patients. The week before that was 205 fully vaxxed patients.
The state has reported 647 breakthrough deaths, or 0.01% of those who are fully vaxxed. That’s a one-week increase of 61 deaths — up from the previous weekly increase of 34 deaths. The week before that was 43 deaths.

So-Called New COVID “Variant" was Simulated in Israel Weeks before it was “Discovered" [“in reality there are no variants of COVID. They are all computer simulations of specific gene sequences"]
/
the editor of Health Impact News states, “The flames of “COVID fear” are being stoked again, as the Big Pharma Globalists unleash their new plan to increase profits and exert more tyrannical control over populations by using their corporate media and puppet politicians in an attempt to extend the false “COVID pandemic.”
Within just a couple of days after announcing that a “new variant” has been discovered in Africa, Big Pharma has now promised the world that they are rushing to rescue everyone with new drugs and new vaccines to fight this “deadly new variant.”
What kind of people are still watching this Hollywood-like scripted show and actually believing it is true?? [MORE]
From [HERE] Two weeks before this current new variant suddenly appeared in Africa and started making the news cycle, Israel, which has been Pfizer’s human laboratory to test their COVID shots, ran a “war games” simulation to prepare for a “deadly new variant” which at the time had not yet been named. They called this future variant “Omega,” and the simulation was carried out on November 11, 2021.
Dozens of top officials took part in what Prime Minister Naftali Bennett called a COVID-19 war exercise on Thursday to gauge the country’s preparedness for the next wave of the pandemic.
“We are starting an unprecedented event here,” the prime minister said at the start of the exercise – “not only on an Israeli scale but on a global level. We are conducting a war exercise to prepare for a new variant that does not even exist yet.”
The “Omega Exercise,” as Bennett called it, was held in the format of a “war game,” the Prime Minister’s Office said. Bennett has regularly referred to the “Omega strain,” the next harmful COVID-19 variant that has not yet been discovered. A war game is a game of the mind; no physical exercises took place.
Bennett said that Israel has surfaced from the Delta wave without locking down, proving that “with proper management, the pandemic can be defeated.” (Full article – and thanks to the Robin Monotti, Dr Mike Yeadon & Cory Morningstar Telegram Channel for pointing this out.)
Africa is Chosen to be the Source of the New Variant Scam
Up until now, Africa has been an enigma to the Globalists’ narrative on the COVID-19 plandemic, as the continent has the lowest rates of COVID-19 vaccination, while also having the fewest amounts of “COVID-19 deaths.”
Ryan McMaken of the Mises Institute reported:
Since the very beginning of the covid panic, the narrative has been this: implement severe lockdowns or your population will experience a bloodbath. Morgues will be overwhelmed, the death total toll will be astounding. On the other hand, we were assured those jurisdictions that do lock down would see only a fraction of the death toll.
Then, once vaccines became available, the narrative was modified to “Get shots in arms and then covid will stop spreading. Those countries without vaccines, on the other hand, will continue to face mass casualties.”
The lockdown narrative, of course, has already been thoroughly overturned. Jurisdictions that did not lock down or adopted only weak and short lockdowns ended up with covid death tolls that were either similar to—or even better than—death tolls in countries that adopted draconian lockdowns. Lockdown advocates said locked-down countries would be overwhelmingly better off. These people were clearly wrong.
Undaunted by the increasing implausibility of the lockdown narrative, the global health bureaucrats are nonetheless doubling down on forced vaccines—as we now see in Austria—and we continue to be assured that only countries with high vaccination rates can hope to avoid disastrous covid outcomes.
Yet, the experience in sub-Saharan Africa calls both these narratives into question: Africa’s numbers have been far, far lower than the experts warned would be the case.
For example, the AP reported this week that in spite of low vaccination rates, Africa has fared better than most of the world:
[T]here is something “mysterious” going on in Africa that is puzzling scientists, said Wafaa El-Sadr, chair of global health at Columbia University. “Africa doesn’t have the vaccines and the resources to fight COVID-19 that they have in Europe and the U.S., but somehow they seem to be doing better,” she said….
Fewer than 6% of people in Africa are vaccinated. For months, the WHO has described Africa as “one of the least affected regions in the world” in its weekly pandemic reports.
Yet disaster for Africa has long been predicted for several reasons even beyond the availability of vaccines. For instance, it is known that lockdowns are especially impractical in the poorest parts of the world.
This is because populations in places with undeveloped economies can’t simply sit at home and live off savings or debt. Rather, these people must go out into the world and earn a living on a day-to-day basis. Starvation is the alternative.
Moreover, much of this work is done in the informal economy, so enforcing lockdowns becomes especially difficult.
It was also assumed covid would be especially deadly in Africa due to the fact many large households live in small housing units.
But that “conventional wisdom” flies in the face of the reality of covid in Africa, which is that there have been fewer deaths. (Full article here.)
But this new fake variant has been reportedly found in South Africa, with the supposed first detections coming from Botswana. The variant now has a name, Omicron, and while the corporate media is hyping it up and creating fear over it, the people in Africa themselves are not concerned.
Paul Joseph Watson of Summit News reports:
The new ‘Omicron’ variant of COVID-19 was first detected in four people who were fully vaccinated, according to a public statement by the Botswana government.
The new variant, which some claim is three times more contagious, was initially discovered in Botswana before it spread across South Africa.
The news was met with global alarm, prompting financial markets to plummet and new travel bans to be put in place.
According to a public statement by the Botswana government, the new mutation was first discovered in four people who had received both doses of the COVID-19 vaccine.
Covid Still Has No Clearly Defined Symptoms b/c It is Determined by PCR Tests. Study Concludes common cold and gastrointestinal symptoms are wrongly associated with Covid
/
From [HERE] A diagnosis is a compilation of clinical symptoms and testing adds further information to help doctors decide on the likelihood of a particular diagnosis. Because a covid case has been defined not by symptoms but by a positive test result this logic has been reversed. The consequence of this was an ever growing list of symptoms associated with the disease and even the concept of an ‘asymptomatic case’.
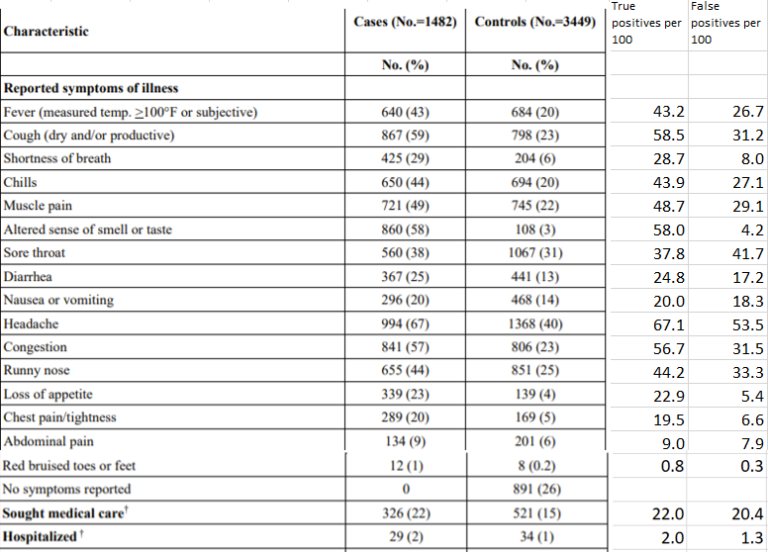
After 20 months of covid it is quite incredible that the symptoms associated with the disease have not been clearly defined. It is possible to figure out which symptoms are associated with a positive test and that has incidentally been reported in a paper in the New England Journal of Medicine studying vaccine efficacy among healthcare workers in the first five months of 2021. Using data from this paper symptoms such as sore throat, runny nose, diarrhoea, nausea, vomiting and abdominal pain can be shown to have no bearing on whether someone will test positive for covid.
The study measured healthcare workers who were tested to see if they had covid, and were asked about vaccination status but also which symptoms they had before testing. The paper then reported the proportion testing positive or negative. For example, they report that 9% of people with abdominal pain tested positive compared to 6% testing negative. Therefore, it might be assumed that abdominal pain is a relevant symptom for covid. However, the authors had included asymptomatic people among the negative control group and not the positives. This meant that the denominator for the percentage was too high in the negative group. Excluding the asymptomatic people from both groups gives a true percentage for comparison.
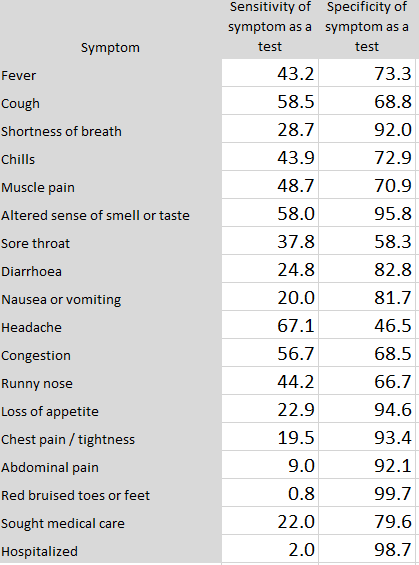
Figure 2 Sensitivity of each symptom as a test (percentage of people with the disease who have that symptom) and specificity of each symptom as a test (percentage of people without the disease who do not have that symptom)
To really understand the implications of each symptom we can treat each one as if whether or not you have it is, itself, a test for covid. In this way, we can calculate the percentage of people with the disease who have that symptom, the sensitivity of the symptom as a test. Likewise we can calculate the chance of someone testing negative if they do not have that symptom, the specificity of the symptom as a test. The latter gives an indication of the types of symptoms that people use to make the decision to seek a test.
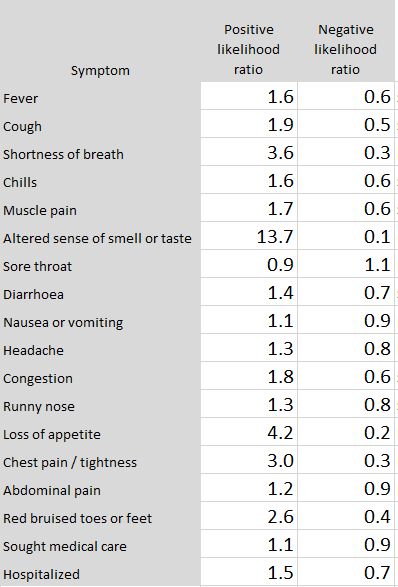
Having broken down the problem this way it is possible to calculate a practical indicator of the meaning of each symptom. The first stage is to calculate the likelihood ratios. This is an intermediate step that leads us to the probability of someone with each symptom testing positive. [MORE]
Analysis Suggests the English Government May be Manipulating Mortality Data to Fabricate the Effectiveness of Deadly COVID Injections
/Latest statistics on England mortality data suggest systematic miscategorisation of vaccine status and uncertain effectiveness of Covid-19 vaccination
By Martin Neil, Norman Fenton Joel Smalley, Clare Craig, Joshua Guetzkow, Scott McLachlan, Jonathan Engler and Jessica Rose
3 December 2021
From [HERE] and [HERE] The risk/benefit of Covid vaccines is arguably most accurately measured by an all-cause mortality rate comparison of vaccinated against unvaccinated, since it not only avoids most confounders relating to case definition but also fulfils the WHO/CDC definition of "vaccine effectiveness" for mortality. We examine the latest UK ONS vaccine mortality surveillance report which provides the necessary information to monitor this crucial comparison over time. At first glance the ONS data suggest that, in each of the older age groups, all-cause mortality is lower in the vaccinated than the unvaccinated. Despite this apparent evidence to support vaccine effectiveness-at least for the older age groups-on closer inspection of this data, this conclusion is cast into doubt because of a range of fundamental inconsistencies and anomalies in the data. Whatever the explanations for the observed data, it is clear that it is both unreliable and misleading. While socio-demographical and behavioural differences between vaccinated and unvaccinated have been proposed as possible explanations, there is no evidence to support any of these. By Occam's razor we believe the most likely explanations are systemic miscategorisation of deaths between the different categories of unvaccinated and vaccinated; delayed or non-reporting of vaccinations; systemic underestimation of the proportion of unvaccinated; and/or incorrect population selection for Covid deaths.
Our recent articles [1, 2] have argued that the simplest and most objective way to assess the overall risk/benefit of Covid-19 vaccines is to compare all-cause mortality rates of the unvaccinated against the vaccinated in each separate age-group. For such an assessment we need accurate periodic data on both age-categorized deaths and the number of vaccinated/unvaccinated people in each age group for that period.
Any systemic errors or biases can lead to conclusions that are inversions of the real situation. For example, simply reporting deaths one week late when a vaccine programme is rolled out will (with statistical certainty) lead to any vaccine, even a placebo, seemingly reducing mortality. The same statistical illusion will happen if any death of a person occurring in the same week as the person is vaccinated is treated as an unvaccinated, rather than vaccinated, death [16].
The UK Government (through its various relevant agencies) has been better than most countries in providing detailed data on Covid cases and deaths indexed by vaccine status. However, in [1] we highlighted the absence of relevant age-categorized mortality data for England, and major inconsistencies in the data provided by different agencies. Of most concern are the very different estimates provided by UKHSA (United Kingdom Health Security Agency) and the ONS (Office for National Statistics) of the number of vaccinated and unvaccinated people. The reports from UKHSA use estimates from the NIMS (National Immunisation Management Service) database [10], while the estimates from the ONS are based on 2011 census respondents and patients registered with a GP in 2019. Hence the ONS England ‘population’ (which therefore includes only people aged at least 10) is only approximately 39 million, compared to the approximately 49 million listed in NIMS. While our focus is on mortality by vaccination status, accurate periodic estimates for the proportion of people vaccinated are also crucial for determining vaccine effectiveness, since this is simply a comparison between the ‘cases’, hospitalisations and deaths per 100K vaccinated and unvaccinated.
An indication of just how critical this is illustrated by the latest UKHSA report [3] which showed that, in each age group above 29, the Covid case rate was higher among the vaccinated than the unvaccinated.
The FDA Now Wants the Public to Wait Until 2096 to Disclose All Information it Relied On to Approve Pfizer’s COVID Injection. The Govt Doubles Down in its 2nd Request to Court to Delay FOIA Response
/
From [AARONSIRI,ESQ] A prior post explained that the FDA has asked a federal judge to make the public wait until the year 2076 to disclose all of the data and information it relied upon to license Pfizer’s COVID-19 vaccine. Literally, a 55-year delay. My firm, on behalf of PHMPT, asked that this information be disclosed in 108 days – the same amount of time it took for the FDA to review and license Pfizer’s vaccine.
The Court ordered the parties to submit briefs in support of their respective positions by December 6, 2021. The FDA’s brief, incredibly, doubles down. It now effectively asks to have until at least 2096 to produce the Pfizer documents. Not a typo. A total of at least 75 years.
Other than producing an initial ~12,000 pages in around two months, the FDA thereafter only wants to commit to producing 500 pages per month. The FDA also disclosed that it actually has approximately at least 451,000 pages to produce.*
Each side gets to file response briefs on December 13, 2021, and then there is oral argument on December 14, 2021 before the Judge. If you want to read the response to the FDA’s position, a copy of the introduction in the brief my firm filed is below. And below that, a downloadable copy of each side’s full briefing is available.
Enjoy. And if you find what you are reading difficult to believe – that is because it is dystopian for the government to give Pfizer billions, mandate Americans to take its product, prohibit Americans from suing for harms, but yet refuse to let Americans see the data underlying its licensure. The lesson yet again is that civil and individual rights should never be contingent upon a medical procedure.
EXCERPT FROM BRIEF DEMANDING TIMELY PRODUCTION
INTRODUCTION
A minimum of 20,010 days (54 years and 10 months). That is how long the FDA proposes to take, at a rate of 500 pages per month, to produce only a portion of the documents in its file for the COVID-19 Pfizer vaccine that PHMPT requested pursuant to the Freedom of Information Act (the “FOIA Request”) and 21 C.F.R. § 601.51(e). But when it came to reviewing those same documents to license this product so that Pfizer could freely sell it to the public, the FDA took just 108 days. It took the FDA’s parent department even less time to grant Pfizer complete immunity to liability for injuries from this product, and it took a stroke of the President’s pen to mandate this product for federal employees, the private sector and military personnel.
The federal government mandating that millions of people be injected with a liability-free vaccine requires complete government transparency – not the government’s suppression of information. PHMPT is comprised of independent scientists working at some of our nation’s premier institutions, and all they are seeking is the data the FDA has already reviewed concerning the Pfizer vaccine in order to provide the necessary peer review. The FDA knows that they, and other independent scientists, cannot properly analyze that data until it is all released. Yet, the FDA wants to wait until most of those scientists are long since dead to fully release the data. News outlets, politicians, and scientists have called the FDA’s position “outrageous.” They are correct.
The entire purpose of FOIA is government transparency. In multiple recent cases, in upholding the FOIA’s requirement to “make the records promptly available,” courts have required agencies, including the FDA, to produce 10,000 or more pages per month, and those cases did not involve a request nearly this important – i.e., the data underlying licensure of a liability-free product that the federal government requires nearly all Americans to receive. As the present pandemic rages on, independent review of these documents by outside scientists is urgently needed to assist with addressing the shortcomings and issues with the response to the pandemic to date. [MORE]
COVID Injections Have Created 9 Billionaires So Far. Would Profiteers Still be Making Billions If They Could Be Held Liable for the Injuries and Death Caused by their Vax Injections?
/
WOULD YOU EAT HERE? HOW MANY HAVE DIED OR BEEN INJURED OR WILL DIE OR BECOME DISEASED DUE TO COVID INJECTIONS? THE SCIENCE FREE MEDICINE PARROTED BY THE DEPENDENT MEDIA IS KILLING PEOPLE.
From [HERE] The federal government has given complete immunity to Pfizer, Moderna, and J&J for any injury caused by their Covid-19 vaccines. That’s right: you cannot sue them if you are injured by their Covid-19 vaccine. (See Note 1 to read the law yourself.) So, while their product may not give you immunity, they are guaranteed immunity.
And it gets even worse. These companies are even immune for – hold your breath – willful misconduct. That may sound crazy, but it is shockingly true. You can only sue them for willful misconduct if the federal government first sues them for such conduct. (See Note 2 to read the law yourself.) And what are the odds the federal government will do so after wildly promoting the vaccine? About as likely as the FDA ever admitting they promoted a vaccine that caused widespread harm.
So, despite Pfizer’s history of willful misconduct, and that this is Moderna’s first product, and that they going to rake in over $100 billion selling a product millions of Americans are mandated to take, you cannot sue them for injuries. That seems fair. After all, we should take pity on these companies since this revenue may not be sufficient to pay for the injuries.
What is most incredible is that we are talking about a product that does not prevent infection and transmission. It, at best, provides personal protection. So, you cannot say “no” to the product without losing your job, cannot sue if you are injured, cannot see the data underlying its licensure, all while it can only potentially protect … you! What?!
From [HERE] At least nine people have become new billionaires since the beginning of the COVID pandemic, thanks to the excessive profits pharmaceutical corporations with monopolies on COVID vaccines are making. Vaccine billionaires are being created as stocks in pharmaceutical firms rise rapidly in expectation of huge profits from the COVID-19 vaccines over which these firms have monopoly control.
The 9 new vaccine billionaires, in order of their net worth are:
Stéphane Bancel, Moderna’s CEO (worth $4.3 billion)
Ugur Sahin, CEO and co-founder of BioNTech (worth $4 billion)
Timothy Springer, an immunologist and founding investor of Moderna (worth $2.2bn)
Noubar Afeyan, Moderna’s Chairman (worth $1.9 billion)
Juan Lopez-Belmonte, Chairman of ROVI, a company with a deal to manufacture and package the Moderna vaccine (worth $1.8 billion)
Robert Langer, a scientist and founding investor in Moderna (worth $1.6 billion)
Zhu Tao, co-founder and chief scientific officer at CanSino Biologics (worth $1.3 billion)
Qiu Dongxu, co-founder and senior vice president at CanSino Biologics (worth $1.2)
Mao Huihua, also co-founder and senior vice president at CanSino Biologics (worth $1 billion)
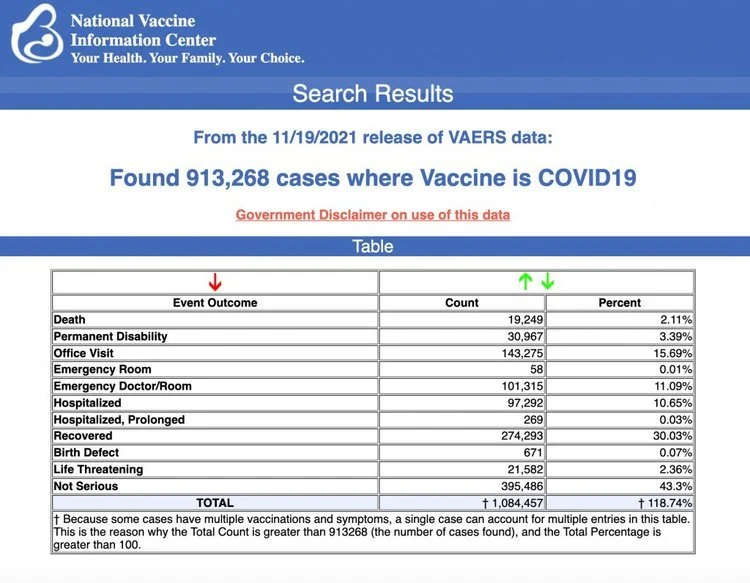
The Centers for Disease Control and Prevention released new data last Monday showing a total of 913,268 adverse events following COVID vaccines were reported between Dec. 14, 2020, and Nov. 19, 2021, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 19,249 reports of deaths — an increase of 396 over the previous week — and 143,395 reports of serious injuries, including deaths, during the same time period — up 4,269 compared with the previous week.
Dr. David Martin Exposes The COVID Profiteers
8 Top Pfizer, Moderna Shareholders $10 Billion Richer After Dependent Media Hypes Omicron Fears
/From [CHD} In the week after news of the Omicron variant hit the headlines, the CEOs and major shareholders of Moderna and Pfizer made a combined $10.31 billion, according to data compiled by the UK-based Global Justice Now.
Shares of Moderna jumped 13.61% — $273.39 to $310.61 — between Nov. 24 and Dec. 1, while Pfizer shares increased 7.41% — $50.91 to $54.68, Common Dreams reported.
Moderna CEO Stéphane Bancel saw his shares increase from $6.1 billion to $6.9 billion, for a gain of $824 million. Albert Bourla, CEO of Pfizer, saw gains of $339,291.
Combined with the CEOs, Moderna’s and Pfizer’s four top shareholders made about $5.16, The Daily Mail reported.
The top Pfizer shareholders include Vanguard Group ($1.72 billion), Blackrock ($1.46 billion), State Street Corp. ($1.1 billion) and Capital World Investors ($909 million).
Moderna’s top shareholders are Baillie Gifford & Co. ($1.59 billion), Vanguard Group ($1 billion), Blackrock ($999.1 million) and Flagship Pioneering ($653.7 million).
As The Defender reported Nov. 30, early news reports on Omicron sent vaccine makers’ stocks soaring, after Moderna and Pfizer said they were rushing to develop vaccines for the new variant.
Moderna’s stock rose 20% on the Friday following Thanksgiving — a short trading day — while Pfizer and its vaccine partner BioNTech saw respective gains of 6% and 14%.
No evidence we need a vaccine for Omicron, but Pfizer makes the case, anyway
Global Justice Now accused Big Pharma of being responsible for the emergence of Omicron by gobbling up profits selling vaccines to wealthy countries, while refusing to share patents and making sure low-income countries get access to COVID vaccines.
Tim Bierley, the organization’s pharma campaigner, said:
“Pharmaceutical companies knew that grotesque levels of vaccine inequality would create prime conditions for new variants to emerge. They let COVID-19 spread unabated in low and middle-income countries. And now the same pharma execs and shareholders are making a killing from a crisis they helped to create. It’s utterly obscene.”
But not everyone agrees that failure to vaccinate causes new variants to emerge, or that Omicron is dangerous.
Dr. Angelique Coetzee, who is credited with discovering the Omicron variant, said she believes the variant may help lead to herd immunity.
Coetzee, who chairs the South African Medical Association and who has been a general practitioner for the last 33 years, said Omicron symptoms so far appear mild.
Coetzee wrote for The Daily Mail:
“No one here in South Africa is known to have been hospitalized with the Omicron variant, nor is anyone here believed to have fallen seriously ill with it … The simple truth is: We don’t know yet anywhere near enough about Omicron to make such judgments or to impose such policies … If, as some evidence suggests, Omicron turns out to be a fast-spreading virus with mostly mild symptoms for the majority of the people who catch it, that would be a useful step on the road to herd immunity.”
Early data support Coetzee’s observation that while Omicron may be highly infectious, it’s not highly dangerous.
According to CNBC, the South African Medical Research Council, in a report released Saturday, said most patients admitted to a hospital in Pretoria who had COVID didn’t need supplemental oxygen.
The report also noted that many patients were admitted for other medical reasons and were then found to have COVID.Pfizer CEO Bourla responded to that news by telling the Wall Street Journal:
“I don’t think it’s good news to have something that spreads fast. Spreads fast means it will be in billions of people and another mutation may come. You don’t want that.”
Though it’s not clear whether there’s a need for a new shot, Pfizer can develop a vaccine that targets omicron by March 2022, Bourla said.
It will take a few weeks to determine whether the current vaccines provide enough protection against the variant, Bourla said.
3 Teens Dead, 120 Hospitalized in Vietnam Following Pfizer Vax Rollout. No One Can be Held Liable. Dependent Media Ignores Story to Avoid a Conflict of Interest w/Vested Interests who Pay Their Bills
/
From [CHD] The Vietnamese province of Thanh Hoa suspended a batch of Pfizer-BioNTech’s COVID vaccineafter more than 120 teens were hospitalized after being vaccinated.
According to the province’s Center for Disease Control (CDC), the teens were hospitalized for symptoms ranging from nausea and high fevers to breathing difficulties — with 17 children exhibiting severe reactions.
Thanh Hoa authorities have yet to confirm Pfizer’s COVID vaccine caused the teens’ symptoms, VN Express International reported.
Vu Van Chinh, director of the Ha Trung District General Hospital, said side-effects following vaccination are normal but are more likely to happen in children than adults.
Luong Ngoc Truong, director of the CDC, said although the province stopped using the current vaccine batch, “We still have other batches, also Pfizer vaccines, so we will continue vaccinating the children.”
The suspended batch was put into storage and could be used later for other groups like adults, Truong added.
Last week, four workers in Thanh Hoa’s Kim Viet Shoe factory died — also due to “overreaction” — after receiving the Vero Cell COVID vaccine, authorized in May by the World Health Organization for emergency use.
Three Vietnamese children die after Pfizer vaccine
Vietnam on Nov. 30 rolled out its COVID vaccination program for children 15 to 17 years old with Pfizer’s vaccine. Since then, three children have died after receiving their first dose. The cause of death was “overreaction to the vaccine.”
One of the three deaths reported in Vietnam includes a 12-year-old boy in the southern province of Binh Phuoc who died one day after his first Pfizer shot.
The boy received his vaccine Monday afternoon and was sent home to rest. After dinner, he experienced dizziness, abdominal pain and diarrhea. He was taken to a local hospital and then transferred to two others, but died Tuesday morning.
The Binh Phuoc Department of Health set up an expert panel to determine the cause of the 12-year-old’s death.
A 16-year-old boy in the northern Bac Giang Province, and a ninth-grade girl in Hanoi, both died Sunday after receiving Pfizer’s COVID vaccine.
The Health Ministry said both deaths were caused by “overreaction to the vaccine,” not by a problem with the quality of the vaccine or the vaccination process.
Drugmakers Pfizer and Merck on Nov. 24 agreed to give licenses to firms in Vietnam to produce COVID treatment pills — paxlovid (Pfizer) and molnupiravir (Merck).
Vietnam is one of 95 low- and middle-income countries allowed to produce the pills through a voluntary licensing agreement with Medicines Patent Pool, an international public health group backed by the United Nations.
According to the latest data from the U.S. Vaccine Adverse Event Reporting System, there have been 18,558 reported adverse events following Pfizer’s COVID vaccine among 12 to 17-year-olds.
Moronic, Outgoing NYC Mayor Announces Mandatory Vaccine Requirement for All Private Employers w/No Testing Option. Businesses Cannot be Held Liable for Medical Harm that Results from a Mandatory Vax
/
From [HERE] Earlier today, NYC Mayor Bill de Blasio announced a first-in-the-nation vaccine mandate covering all private-sector workers in NYC that will take effect on December 27, 2021. According to Mayor de Blasio, the mandate will cover approximately 184,000 businesses.
NYC is set to publish guidelines for employers on December 15, which will provide employers with less than two weeks to implement and enforce the new mandate. Although we do not yet know the full scope of the new requirement, we anticipate that there will be few exceptions. We also anticipate that the mandate will be challenged in the courts. Mayor de Blasio announced that the mandate will apply to all in-person employees, and those employees will not have the option of getting regularly tested in lieu of vaccination. Employees must have at least one dose of the vaccine by December 27.
The mandate is slated to take effect just days before Mayor-elect Eric Adams replaces Mr. de Blasio.
“There’s no clarity around who and how this will be enforced,” Ms. Wylde said.
Evan Thies, a spokesman for Mr. Adams, said the mayor-elect would evaluate the mandate, as well as other Covid-19 strategies, when he takes office. [MORE]
Apparently the mandate will not make businesses liable for any medical harm that results from a mandatory vaccination.
It is undisputed that COVID “vaccines” do not prevent transmission or prevent individuals from getting COVID. A recent Harvard study shows no discernible relationship between the vaccination rate and new cases. Meanwhile, evidence in study after study has demonstrated that so-called COVID “vaccines” are extremely dangerous. Below professor Dr. Julie Ponesse raises several questions relevant to illogical mandates;
Consider these facts:
1) COVID-19 has an infection fatality rate not even 1% that of smallpox (and it poses even less risk to children)
2) a number of safe, highly effective pharmaceuticals exist to treat it (including monoclonal antibodies, Ivermectin, fluvoxamine, Vitamin D and Zinc), AND
3) The vaccines have reported more adverse events (including innumerable deaths) than every other vaccine on the market over the last 30 years.
In light of these facts, I have so many questions:
Why are the vaccinated granted vaccine passports and access to public spaces, when the Director of the CDC has stated that the COVID-19 vaccines cannot prevent transmission?
Why is vaccination the ONLY mitigation strategy when emerging evidence (including a recent Harvard study) shows no discernible relationship between the vaccination rate and new cases?
Why does our government continue to withhold Ivermectin as a recommended treatment when the U-S National Institutes of Health supports it, and when the state of Uttar Pradesh in India distributed it to its 230 million people, reducing its COVID death rate to almost zero? How has India surpassed Canada in Health Care?
Why are we about to vaccinate 5 year olds when COVID poses to them less risk than the potential vaccine reactions AND while there is NO effective monitoring system for the vaccines?
Why are we focused on the narrow benefits of vaccine-induced immunity when real-world studies show natural immunity is more protective, more potent, and more enduring?
Why do we shame the “vaccine hesitant” and not the “vaccine adamant”?
“Why,” as a nurse recently asked, “do the protected need to be protected from the unprotected by forcing the unprotected to use the protection that did not protect the protected in the first place?”
By every measure and from every angle, this is a ‘house of cards’ about to crumble
But the question that interests me is why hasn’t it crumbled already? Why are these questions not the headlines of every major newspaper in Canada every day? [MORE]
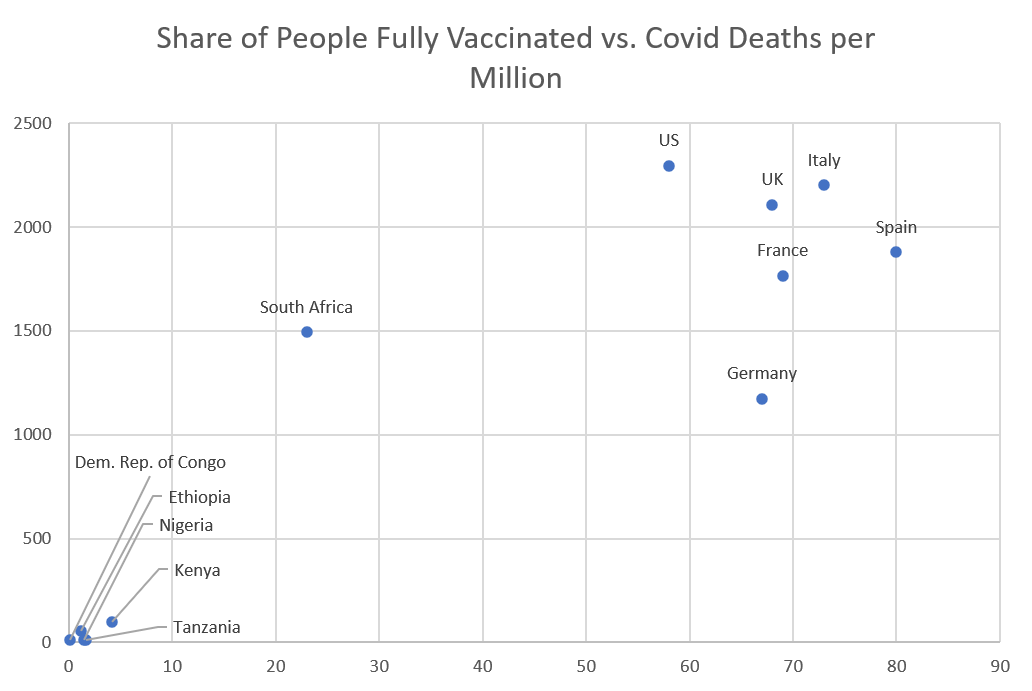
W/Low Vaccination Rates Africa’s Covid Deaths Remain Far Below Europe and US. According to WHO Data Deaths in Africa are Only 2.9% of Covid Deaths Worldwide while Africa is 16% of the World Population
/
From [GR] Since the very beginning of the covid panic, the narrative has been this: implement severe lockdowns or your population will experience a bloodbath. Morgues will be overwhelmed, the death total toll will be astounding. On the other hand, we were assured that those jurisdictions that implement the lockdown would experience only a fraction of the death toll.
Then, once vaccines became available, the narrative was modified to:
“Get shots in arm and then covid will stop spreading. Those countries without vaccines, on the other hand, will continue to face mass casualties.”
The lockdown narrative, of course, has already been thoroughly overturned. Jurisdictions that did not lock down or adopted only weak and short lockdowns ended up with covid death tolls that were either similar to—or lesser than—death tolls in countries that adopted draconian lockdowns. Lockdown advocates said locked-down countries would be overwhelmingly better off. These people were clearly wrong.
Undaunted by the increasing implausibility of the lockdown narrative, the global health bureaucrats are nonetheless doubling down on forced vaccines—as we now see in Austria—and we continue to be assured that only countries with high vaccination rates can hope to avoid disastrous covid outcomes.
Yet, the experience in sub-Saharan Africa calls both these narratives into question: Africa’s numbers have been far, far lower than the experts warned would be the case.
For example, the AP reported mid November 2021 that in spite of low vaccination rates, Africa has fared better than most of the world:
[T]here is something “mysterious” going on in Africa that is puzzling scientists, said Wafaa El-Sadr, chair of global health at Columbia University. “Africa doesn’t have the vaccines and the resources to fight COVID-19 that they have in Europe and the U.S., but somehow they seem to be doing better,” she said….
Fewer than 6% of people in Africa are vaccinated. For months, the WHO has described Africa as “one of the least affected regions in the world” in its weekly pandemic reports.
Yet disaster for Africa has long been predicted for several reasons even beyond the availability of vaccines. For instance, it is known that lockdowns are especially impractical in the poorest parts of the world. This is because populations in places with underdeveloped economies can’t simply sit at home and live off savings or debt. Rather, these people must go out into the world and earn a living on a day-to-day basis. Starvation is the alternative. Moreover, much of this work is done in the informal economy, so enforcing lockdowns becomes especially difficult.
It was also assumed that covid would be especially deadly in Africa due to the fact many large households live in small housing units.
But that “conventional wisdom” flies in the face of the reality of covid in Africa, which is that there have been fewer deaths.
The “experts” have groped around, looking for possible explanations.
Some sources, for example, insist that the low death totals are only an artifact of incomplete reporting on covid infections and that “a lack of good qualitative data was the issue.”
But Richard Wamai at Northeastern University rejects the claim it’s all about case reporting, and says that “local systems for reporting deaths in Africa make it difficult to hide COVID-19 casualties.” In a paper for the International Journal of Environmental Research and Public Health, Wamai and his coauthors conclude,
“[T]here is no evidence that COVID-19 mortality data is less accurately reported in Africa than elsewhere” …
“While the true picture of infections and mortality in the continent has yet to fully emerge, the quality of data for other diseases, such as HIV/AIDS, indicates that Africa has the capacity to collect and report valid disease surveillance data.”
In any case, the World Health Organization reports that covid deaths in Africa make up only 2.9 percent of covid deaths Worldwide, while Africa’s population is 16 percent of the global total.
Africa’s covid total could double or triple, and Africa would still be faring far better than Europe and the Americas.
Wamai et al. also note that at this point
“[i]t is likely that SARS-CoV-2 has already been widely disseminated through Africa…. If so, widespread infection is likely to also result in widespread natural immunity.”
In other words, continued claims by health officials—both in Africa and elsewhere—that mass death is right around the corner with the “next wave” look increasingly implausible.
It looks increasingly likely that the lack of covid mortality in Africa is not due to a data issue nor a situation in which covid has been “contained” up until now. So then why is Africa doing so much better than the wealthy West?
Naturally, the advocates of forced lockdowns and coerced vaccines would prefer to ignore this issue altogether, but the undeniable reality of Africa’s experience has forced mainstream researchers to publicly admit the many ways that many factors can explain covid’s prevalence beyond vaccination rates and mask mandates.
For instance, mentioning that obesity is an important factor in covid mortality has in the past been likely to get one savaged in the media for “fat shaming.” Yet the Africa situation has forced the well informed to admit that yes, obese populations clearly suffer more from covid. In Africa, not surprisingly, we find that obesity rates are far below those found in North America and Europe.
Other possible explanations forwarded as reasons for Africa’s situation include past exposure to other coronaviruses, youthful populations, fewer patients lacking zinc and vitamin D, past use of the Bacillus Calmette-Guérin vaccination, climate, genetic background, and parasite load.
In addressing the African “enigma” one group of researchers in the journal Colombia medica dared even suggest it’s possible—although not conclusively shown at this point—that “a mass public health preventive campaign against COVID-19 may have taken place, inadvertently, in some African countries with massive community ivermectin use.”
In the West, however, the media drumbeat around covid has consistently been “Shut up, stay home, get jabbed, and stop doubting the experts on forced vaccines.” Fortunately, however, the African situation has forced many researchers to ask inconvenient questions.
In fact, it’s amazing Africa has not been overcome by mass death considering that covid lockdowns and covid economic and social “mitigation” measures have contributed to the impoverishment and mass starvation on the continent. Or as Germany’s DW News puts it,
“Measures put in place to slow the spread of the novel coronavirus are pushing millions of people in Africa into severe hunger.”
And as Wamai notes,
“[S]ome of the excess deaths in Africa “can be attributed not to the disease, but to lockdown measures that cut off access to medical care for other illnesses.”
But Africa hasn’t gotten the bloodbath that was promised, and as one Nigerian put it, “They said there will be dead bodies on the streets and all that, but nothing like that happened.”
LeBron James Cleared to Return After Meaningless PCR Covid Tests Say So [never in the history of Respiratory Disease have Healthy People with No Symptoms Spread a Deadly Virus- COVID is a Mind Virus]
/MAKES GOOD SENSE TO SHEEPLE. From [HERE] Two days after LeBron James was sidelined by the league’s health and safety protocols because he registered conflicting Covid-19 results, the NBA’s biggest star is back after the league said that subsequent testing determined that he was not a positive case.
James, who is fully vaccinated, was ruled out indefinitely on Tuesday after he tested positive for Covid in a sample collected on Monday, according to the NBA, which issued a statement outlining his testing results in unusual detail on Thursday night.
The league said that Monday’s positive sample was tested again Tuesday on two different PCR machines and returned one positive result and one negative result, prompting James to miss the Lakers’ game that night and return to Los Angeles amid the uncertainty. He then underwent two more rounds of testing on Tuesday, which only added to the confusion, as he returned one negative and one “clinically inconclusive” result, the league said.
He was cleared to return to the court when James registered negative PCR tests on Wednesday and Thursday, according to a person familiar with the matter.
The league’s vaccinated players who test positive must remain out for at least 10 days or, in James’s case, until they return two negative results at least 24 hours apart. [MORE]

IN REALITY THE VESTED INTERESTS ARE FUCKING WITH YOUR MIND. it is undisputed that the PCR tests don’t work to diagnose active infection with covid19.
We all keep saying that don’t we, but we don’t seem able to grasp what it means, because even though we know PCR tests don’t work to diagnose infection we keep accepting all the statistics that are produced as a result of assuming PCR tests diagnose infection.
We say – “0h wow, covid numbers rising despite the lockdown”. Or “massive spike in people getting covid in THIS care home despite precautions”. Or “look the ‘vax’ doesn’t work because people who get it still catch covid”.
No. Wrong. They’re not “covid numbers”, they’re positive-test numbers. It’s not a spike in people ‘getting Covid’ in the care home, it’s a spike of people testing positive. The people who get the vax don’t “still catch covid”, they still test positive.
And the reason why these ‘anomalies’ happen, the reason why vaxxed people can still test positive, etc etc is the same reason a papaya can test positive – because the PCR tests don’t work.
We know it but keep forgetting it. So let’s say it again.
The PCR tests don’t work.
The PCR tests. Don’t. Work.
We all know the danger of false positives if too many cycles are run. This is admitted even by Fauci.
If you run your tests at 30 cycles or more the results are very likely to be junk and any positives meaningless. And, incredibly, most labs performing these tests have been doing just that – running cycles of 30 or more, even up to 45.
But this well known and important fact hides the even more important fact that even when the tests are done properly they still don’t work – in that they are not designed to do what they are being used for.
They don’t diagnose infection or detect active infection. They aren’t, for the most part, even specific for SARSCOV2. They just look to see if you have some random fragments of RNA in your body that someone has identified as being similar to some types of assumed viral RNA. [MORE]
It is a lie that People with No Symptoms Can Spread a Virus
"So-called asymptomatic cases have never in the history of respiratory disease been the driver for spread of infection. Rather it is symptomatic people who spread respiratory infections - not asymptomatic people" - https://worlddoctorsalliance.com/
This lie states that healthy people with no symptoms can spread a deadly virus, seriously. This lie keeps us all afraid of each other and makes people wear masks. We all have to then assume that every person you see could have the virus unknowingly, without symptoms and be spreading it..
Imagine if you go back to the normal year of 2019 and you explained you couldn’t go for a night out with a friend because you had the flu and you don’t want to give it to your friend your friend asked ‘oh I see, have you got aching muscles and temperature and you feel unwell’ and you said ‘no, I have no symptoms and I feel fine’. Your friend would laugh at you and would think you’re crazy. Hundreds of years of science have just been turned on its head.
So ask yourself if you go back to 2019 and all the decades before would you be scared of catching the flu of someone who has no symptoms of the flu. No you wouldn't. Covid-19 does not spread differently as it has the same symptoms as a coronavirus or the flu. But that is the lie we are being told by adverts on T.V and the radio and governments.
Nearly 10 million people were tested in Wuhan, consisting of 92 percent of all residents aged six years or older. Incredibly, no new symptomatic cases were registered, and only 300 asymptomatic cases were detected. Subsequent tests of 1,174 close contacts of the asymptomatic cases found resulted in no new positives. There is “no evidence that the identified asymptomatic positive cases were infectious,” the study said. [MORE]